



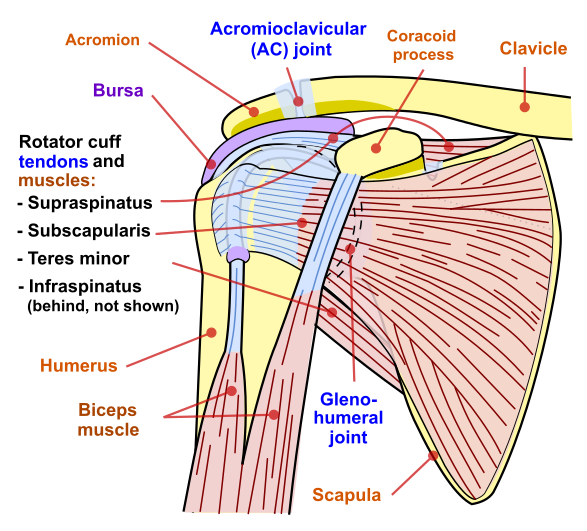
Shoulder soft tissue conditions
Glenohumeral dislocation and instability
- Dislocations of the glenohumeral joint caused by traumatic or atraumatic reasons
- Trauma is due to direct injury, most commonly a fall on an outstretched hand (FOOSH) mechanism of injury
- Atraumatic can be due to repetitive injury, causing hypermobility
- Types of dislocations:
- Anterior-inferior dislocations: Most common type (95%). Mechanism is a combination of motions including: excessive horizontal abduction, abduction, external (lateral) rotation, and extension/hyperextension of the upper extremity.
- If traumatic can lead to: Disruption anterior glenohumeral/capsular ligament, subscapularis, and anterior/inferior glenoid labrum
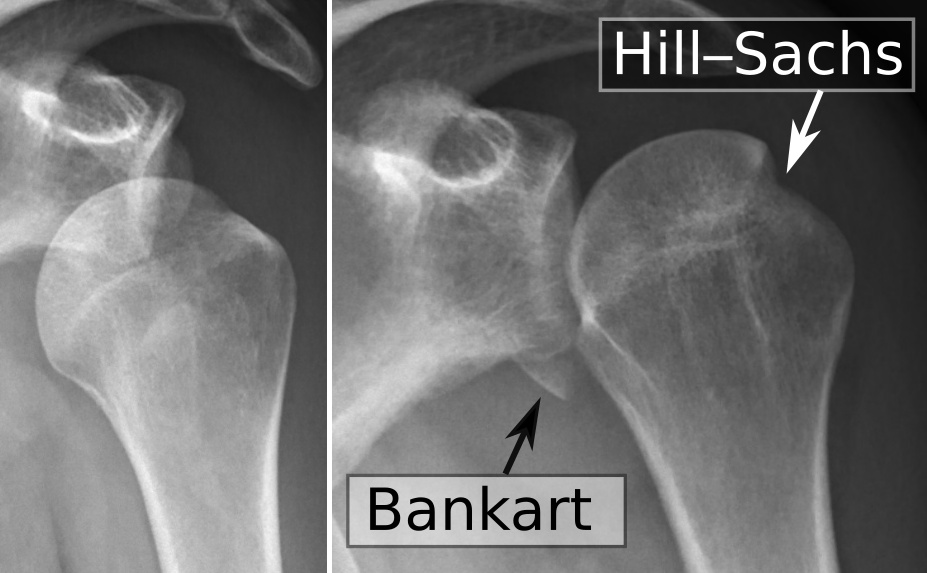
- Hill-Sachs lesion: compression fracture of the posterior humeral head
- Bankart lesion: avulsion of the anterior-inferior glenoid labrum
- Axillary nerve injury: numbness, tingling, and weakness in the deltoid
- If traumatic can lead to: Disruption anterior glenohumeral/capsular ligament, subscapularis, and anterior/inferior glenoid labrum
- Posterior dislocations: rare, caused by horizontal adduction and internal rotation
- Anterior-inferior dislocations: Most common type (95%). Mechanism is a combination of motions including: excessive horizontal abduction, abduction, external (lateral) rotation, and extension/hyperextension of the upper extremity.
- Symptoms
- Popping during movements
- Repeated dislocations or subluxations of the glenohumeral joint
- Diagnosis
- Clinical presentation
- Special tests - apprehension test (highly specific for anterior instability); sulcus sign (positive for inferior instability)
- X-ray
- Physical therapy interventions
- Strengthening the rotator cuff and scapular stabilizers (dynamic stabilizers) to prevent recurrent dislocation
- Functional training
- Avoidance of apprehension position
- Avoid combined abduction/external rotation after an anterior stabilization procedure, per protocol
- Surgical protocols if indicated
- With anticipated return to function in 3-4 months
Labral tears
-
Tear in the cartilage ring that surrounds the shoulder joint; divided into above the middle of the socket and below the middle of the socket
- Above the middle of the socket is called a SLAP (superior labral anterior-posterior) tear; can also involve the biceps tendon
- Below the middle of the socket: Bankart lesion (see glenohumeral dislocation and instability above); may also include a bony Bankart (avulsion fracture of the anterior-inferior glenoid rim)
-
Labral tears are associated with traumatic injury or repetitive shoulder dislocations
-
Symptoms:
- Pain increased with overhead movement or behind the back
- Shoulder weakness
- Shoulder instability/dislocation
- Pain with resisted flexion of the biceps
- Tenderness over the anterior shoulder
-
Diagnosis
- Clinical presentation
- MRI
- Arthroscopic surgery - gold standard for diagnosis
-
Physical therapy interventions
- Focus on return to function without pain
- Correction of muscle imbalances
- Address underlying causes of labral tears
- Surgical protocols if indicated
- With anticipated return to function in 3-4 months
Rotator cuff tendonitis and impingement syndrome
- Caused by mechanical impingement of the distal attachment of the rotator cuff, causing inflammation of the tendons
- Increased risk for development of tendonitis due to poor vascularity at attachment sites
- Inadequate scapular upward rotation and posterior tilt during arm elevation reduce the subacromial space and contribute to impingement
- Symptoms
- Pain in the anterior and superior aspect of the shoulder
- Pain and weakness that worsen with overhead movements, such as reaching, throwing, or lifting objects
- Pain that may radiate down the arm
- Pain that is worse at night
- Diagnosis
- Clinical presentation
- Special tests
- Neer test - forced forward flexion with the scapula stabilized compresses the supraspinatus against the anteroinferior acromion
- Hawkins-Kennedy test - shoulder flexed to 90 degrees with internal rotation compresses the supraspinatus under the coracoacromial ligament
- Painful arc
- Shoulder pain that occurs when abducting an arm between 60 and 120 degrees.
- MRI
- Medical management
- Surgical (subacromial) decompression if indicated
- Physical therapy intervention
- Avoidance of shoulder elevation greater than 90 degrees to avoid subacromial compression - acute phase
- Postural re-education - improve forward head, rounded shoulders, and kyphotic posture (upper cross syndrome)
- Correction of muscle imbalances
- Improve joint mobility, including stretching a tight posterior capsule with the cross-body (horizontal adduction) stretch: stabilize the scapula, keep the arm just below 90 degrees, and move it straight across without letting the humeral head ride up; the sleeper stretch (90 degrees of abduction with internal rotation) can provoke impingement
- Return to previous functional status
- Follow the post-operative protocol after subacromial decompression if indicated
Rotator cuff tear
-
Acute tears are caused by a fall on an outstretched hand (FOOSH), sudden heavy lifting, or loading the shoulder in an awkward position
-
Degenerative or partial tears develop over time from chronic tendonitis and poor blood supply at the tendon insertion
-
Symptoms
- Pain when raising or lowering the arm
- Weakness when lifting or rotating the arm
- Pain when reaching behind the back
- Pain that worsens after lying down on the affected side
- Pain that is worse at night
-
Diagnosis
- Clinical presentation
- Special tests - empty can test, drop arm test, manual muscle testing of infraspinatus and supraspinatus
- MRI
-
Physical therapy intervention
- Conservative management: scapular stabilization and graded rotator cuff strengthening in pain-free range
- Surgical protocols if indicated, avoiding active motion that breaks protocol in the early phase after a repair
- After a rotator cuff repair, the arm is kept in a sling with passive motion only for the first 4 to 6 weeks while the tendon heals back to bone; active exercises follow, and the PT introduces strengthening at about 8 to 12 weeks
Subacromial/subdeltoid bursitis
-
Subacromial and subdeltoid bursae become inflamed (close relationship with rotator cuff tendonitis)
- The bursa becomes trapped (impinged) beneath the acromion arch
-
Symptoms
- Pain may worsen with overhead movements, such as reaching for objects or lifting the arm.
- The shoulder may be tender to the touch, especially around the acromion process.
- The bursa may become inflamed and swollen, causing a visible bulge or lump in the shoulder.
- The shoulder may feel stiff and difficult to move
- When moving the shoulder, there may be clicking or popping sounds as the bursa rubs against the acromion bone.
- Empty end-feel: passive movement stops because of the patient’s pain, not a physical block.
-
Diagnosis:
- Clinical examination - ruling in and out other diagnoses based on symptomatology, as well as assessment of range of motion and muscle strength
-
Physical therapy intervention
- Avoidance of provoking overhead activity in the acute phase, then postural correction and progressive strengthening
Bicipital tendonitis
-
Inflammation of the long head of the biceps
- Cases can involve mechanical impingement of the long head of the biceps under the coracoacromial arch, or irritation as it glides within the bicipital groove
-
Symptoms
- Sharp, throbbing, or dull pain in the front of the shoulder that may radiate down the upper arm - pain worsens with overhead movements, such as reaching, lifting, or throwing.
- Localized tenderness over the biceps tendon, particularly where it passes over the shoulder joint.
- A feeling or sound of snapping or popping in the shoulder when moving the arm.
- Weakness in the biceps muscle, making it difficult to lift or bend the arm.
-
Diagnosis
- Clinical presentation, positive Speed’s and Yergason’s tests.
- MRI
-
Physical therapy intervention
- Avoidance of provoking overhead activity in the acute phase, then postural correction and progressive strengthening
Adhesive capsulitis
-
Restriction in shoulder motion due to inflammation of the joint capsule
- Restrictions are in external rotation (greatest), then abduction, then internal rotation (capsular pattern of the shoulder)
- Progresses through three stages: freezing (painful, progressively restricted motion), frozen (stiff but less painful), and thawing (gradual return of motion)
- Risk factors include diabetes, thyroid disease, cardiovascular disease, and prolonged immobilization (for example, after injury or surgery)
-
Symptoms
- Restriction in external rotation, abduction, and internal rotation, causing functional deficits
-
Diagnosis
- Clinical presentation
- Functional limitations
-
Medical management
- Management of diabetes, cardiovascular, or thyroid disease if applicable
-
Physical therapy management
- Improve joint mobility in the capsular pattern - gentle mobilization in the freezing stage, more aggressive stretching/mobilization in the frozen and thawing stages
- The stretch position sets the part of the capsule stretched: external rotation (with the arm at the side or abducted) for the anterior capsule, full overhead elevation for the inferior capsule, and horizontal adduction or internal rotation for the posterior capsule
- Return to prior functional status
- Improve muscle imbalances
- Improve joint mobility in the capsular pattern - gentle mobilization in the freezing stage, more aggressive stretching/mobilization in the frozen and thawing stages
Use this table to tell apart conditions that present similarly:
| Condition | Key distinguishing finding | Positive tests | PT emphasis |
|---|---|---|---|
| Impingement syndrome | Painful arc, 60-120 degrees of abduction | Neer, Hawkins-Kennedy | Postural correction; avoid elevation above 90 degrees acutely |
| Rotator cuff tear | Weakness with overhead lifting | Drop arm, empty can | Scapular stabilization, graded cuff strengthening |
| Bursitis | Point tenderness over the acromion; empty end-feel | Clinical exam | Relative rest, then postural correction/strengthening |
| Bicipital tendonitis | Tenderness over the bicipital groove | Speed’s, Yergason’s | Relative rest, then postural correction/strengthening |
| Adhesive capsulitis | Capsular pattern: ER most limited, then abduction, then IR | Clinical presentation | Gentle mobility (freezing), more aggressive stretching/mobilization (frozen/thawing) |