


This browser is too old to run Achievable.

Update it, or open this page in a current version of Chrome, Safari, Firefox or Edge. On an iPhone or iPad, update iOS: every browser there runs on the version of Safari that comes with it.

Achievable logoAchievable logo
NPTE-PTA
Sign in
Sign up
Purchase
Textbook
Practice exams
Support
How it works
Resources
Exam catalog
Mountain with a flag at the peak
Textbook
Introduction
1. Cardiovascular system
2. Pulmonary system
3. Neuromuscular system
4. Pediatrics
5. Musculoskeletal system
5.1 Anatomy of musculoskeletal system
5.2 Anatomical terminology and exercise training principles
5.3 Joint mechanics and phases of healing
5.4 Upper extremity anatomy
5.5 Special tests of upper extremity
5.6 Comparing clinical presentation and interventions for upper extremity
5.7 Lower extremity anatomy
5.8 Special tests of lower extremity
5.9 Comparing clinical presentation and interventions for lower extremity
5.10 Spine and pelvis anatomy
5.11 Special tests of the spine, pelvis, and temporomandibular joint
5.11.1 Cervical spine tests
5.11.2 Thoracolumbar, sacroiliac, and TMJ tests
5.12 Comparing clinical presentation and interventions for the spine, pelvis, and temporomandibular joint
5.13 Other musculoskeletal conditions
5.14 Gait
5.15 Prosthetics
5.16 Orthotics
5.17 Medications, imaging, and fractures
5.18 Surgical protocols
6. Other systems
7. Non-systems
Wrapping up
Achievable logoAchievable logo
5.11.1 Cervical spine tests
Achievable NPTE-PTA
5. Musculoskeletal system
5.11. Special tests of the spine, pelvis, and temporomandibular joint
Our NPTE-PTA course is now in "early access" - get 50% off for a limited time.

Cervical spine tests

7 min read
Font
Discuss
Share
Feedback

The PTA performs these cervical special tests as part of data collection within the PT’s plan of care - interpreting findings, diagnosing, and changing the plan of care remain the supervising PT’s responsibility. If a test produces a red-flag sign, stop immediately, keep monitoring the patient, and notify the supervising PT right away.

Safety and stability screens (perform first)

  • Vertebral artery test
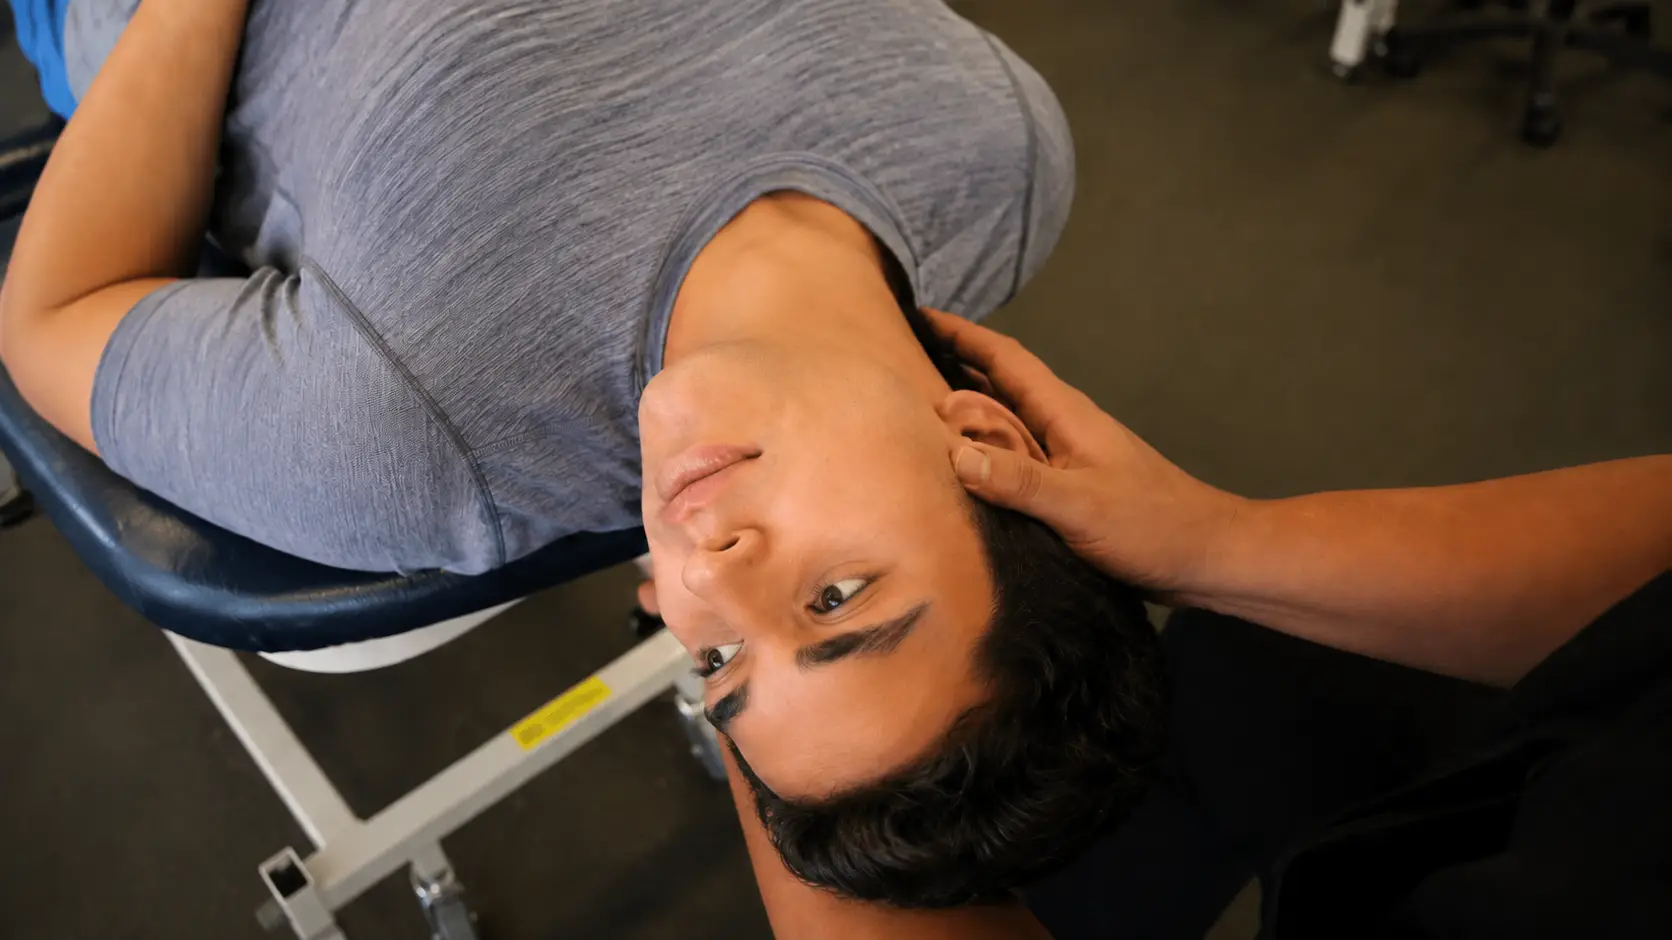
    • The examiner carefully extends the patient’s neck, then rotates the head to one side and holds it there for up to 30 seconds. The patient’s eyes are kept open and monitored, and they are usually asked to count backward or speak to check for changes in their voice.
      • Tests the integrity of the vertebrobasilar vascular system
    • Positive: dizziness, diplopia, dysarthria, dysphagia, drop attacks, nystagmus, nausea, or numbness. This is a red flag - stop the test and any cervical spine intervention immediately, continue monitoring the patient, and notify the supervising PT right away.
      • Current evidence questions the validity and reliability of this positional test on its own. Rather than relying on the positional test alone as the standard of care, current frameworks call for a broader cervical arterial dysfunction screen before cervical spine mobilization or manipulation - including patient history, risk factors, blood pressure, and a cranial nerve exam - to identify patients at risk before proceeding
Patient supine with head extended and rotated off table edge.
Vertebral artery test
Achievable
  • Flexion rotation test
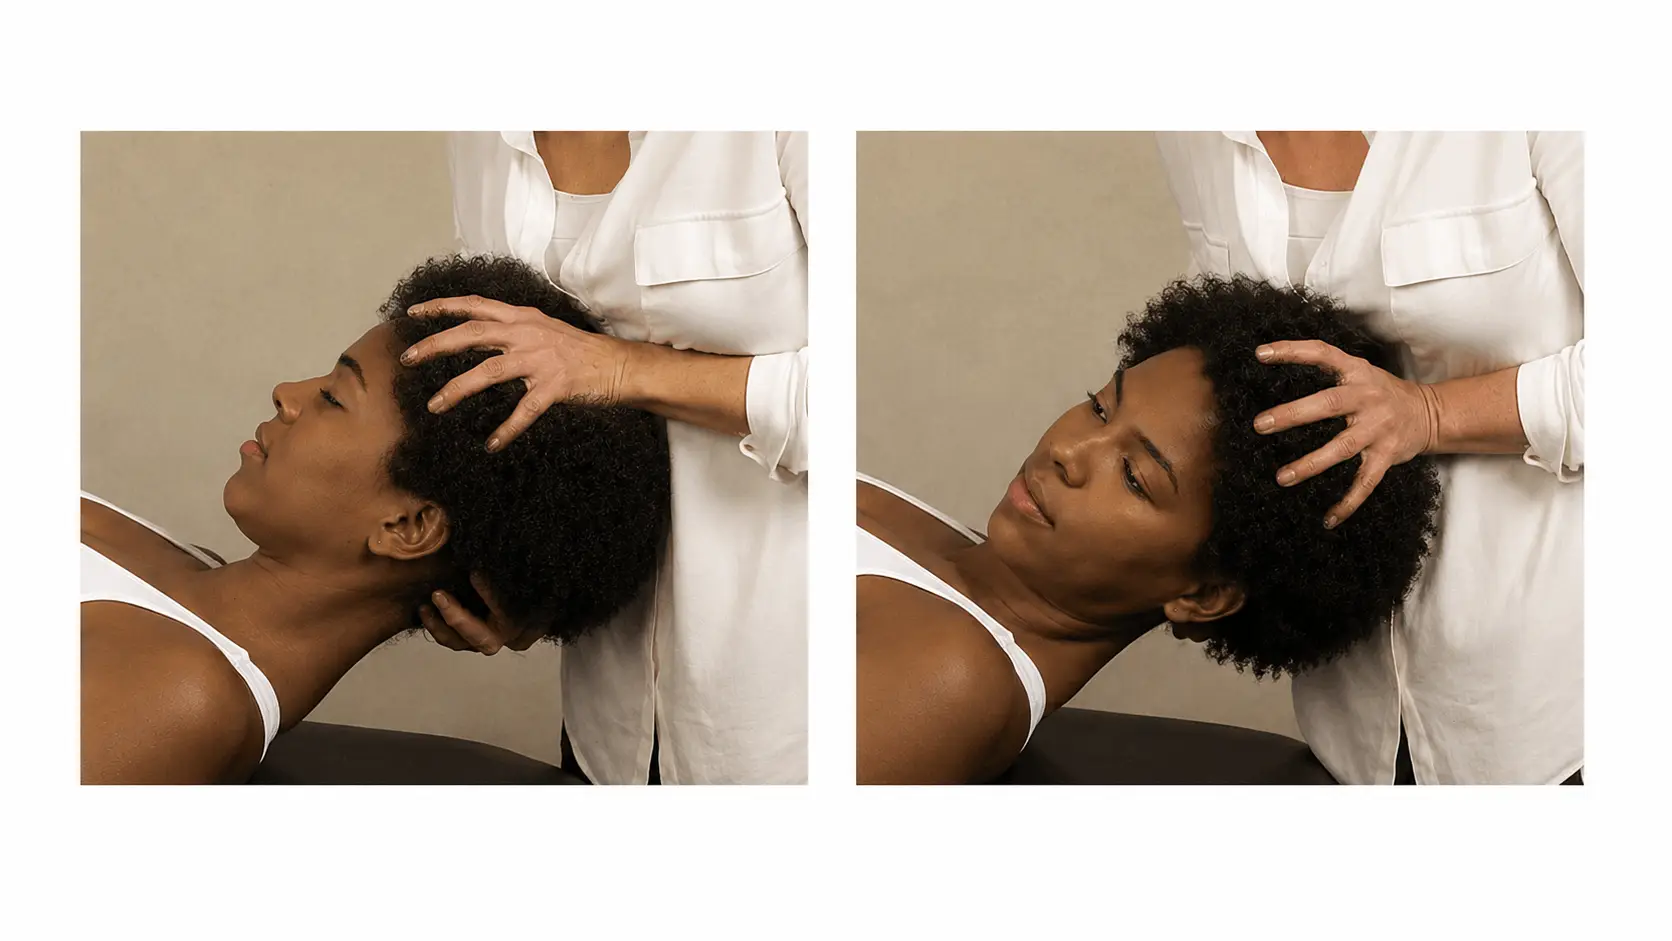
    • Patient in supine with maximal flexion of neck performed with rotation to left and right
      • Provocative test for atlantoaxial dysfunction or cervicogenic headache
      • Positive: headache reproduced, or rotation to one side reduced by more than 10 degrees compared with the other side
Flexion rotation test with therapist-supported head movement.
Flexion-rotation test
Achievable
  • Alar ligament test
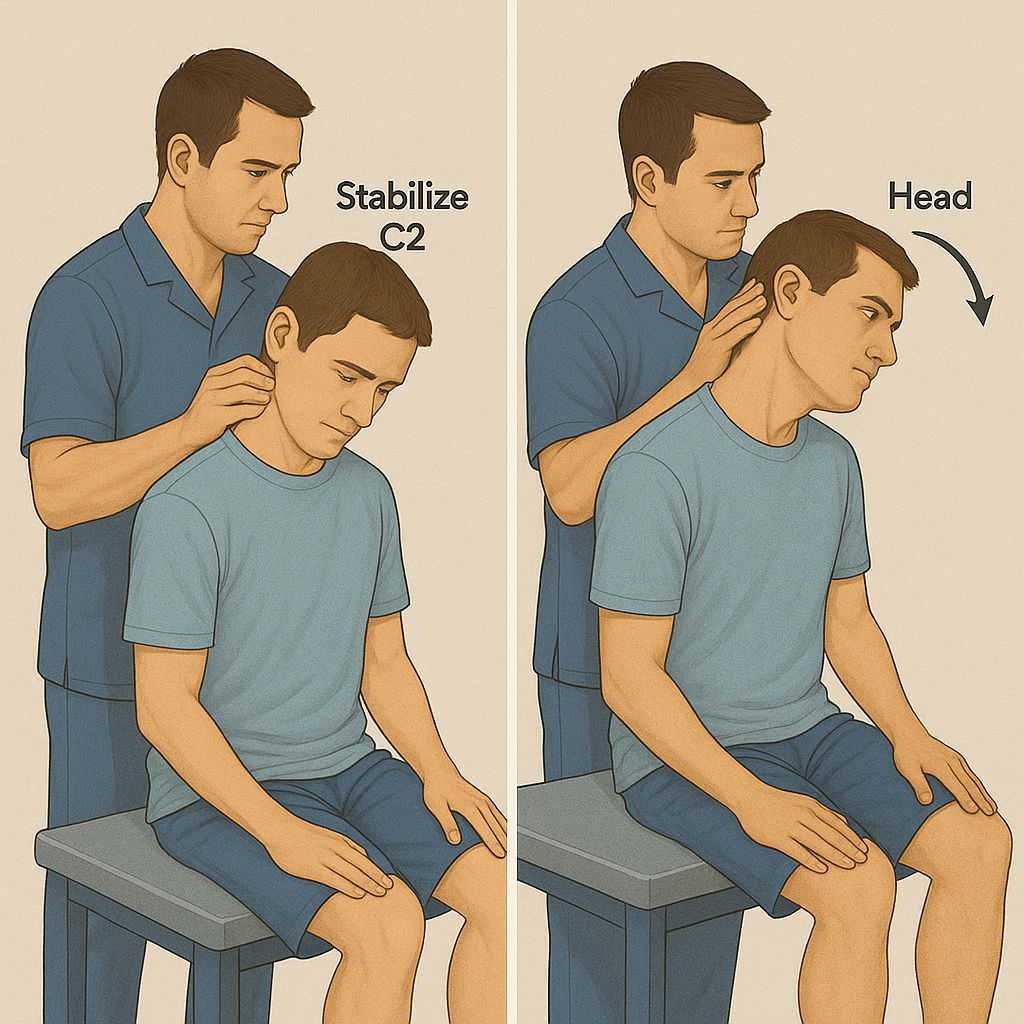
    • Patient seated (or supine) with the neck in slight flexion. The therapist stabilizes the C2 spinous process and passively side-bends the head to each side.
      • Tests the integrity of the alar ligament
    • Positive: excessive side-bending motion compared with the other side, or a soft end-feel (with an intact alar ligament, little to no side-bending occurs and the end-feel is firm). This suggests alar ligament laxity or upper cervical instability - stop and report the finding to the supervising PT.
Seated patient with the clinician palpating C2 while passively side-bending the head.
Alar ligament test
Achievable

Nerve root and cord tests (Spurling’s and compression narrow the foramen to provoke radicular symptoms; distraction opens it to relieve them)

  • Spurling’s test (foraminal compression)
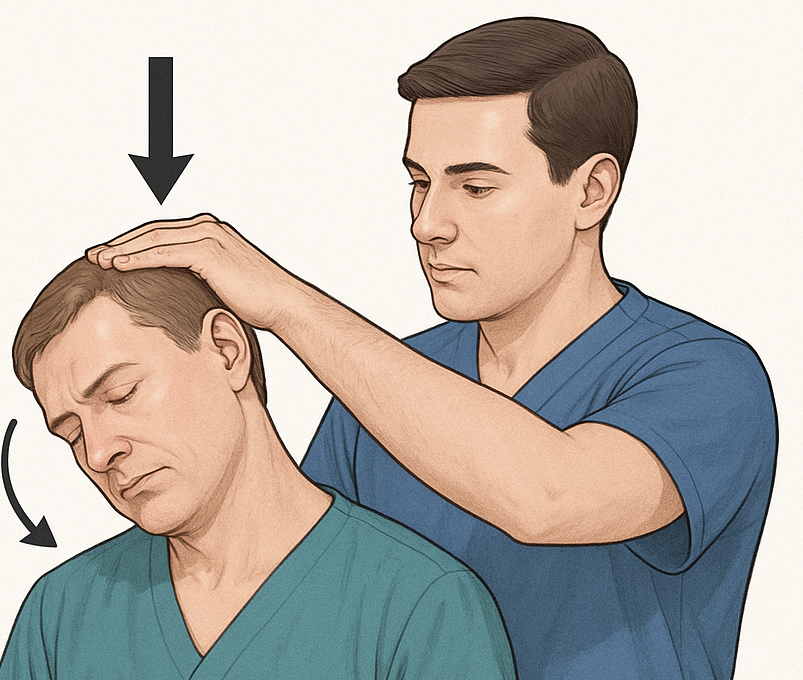
    • Patient sitting with head laterally bending towards the involved side while the therapist applies pressure straight down
      • Provokes/suggests cervical radiculopathy
      • Cervical radiculopathy is compression of a cervical nerve root, and the pain travels down the arm in the area served by that root; extending the neck or turning the head toward the side narrows the foramen and increases symptoms, so extension positions are avoided, while traction in slight flexion opens the foramen
    • Positive: pain and paresthesia in a dermatomal pattern of the cervical root
Seated patient side-bent toward the involved side while the clinician presses down on the head.
Spurling's test
Achievable
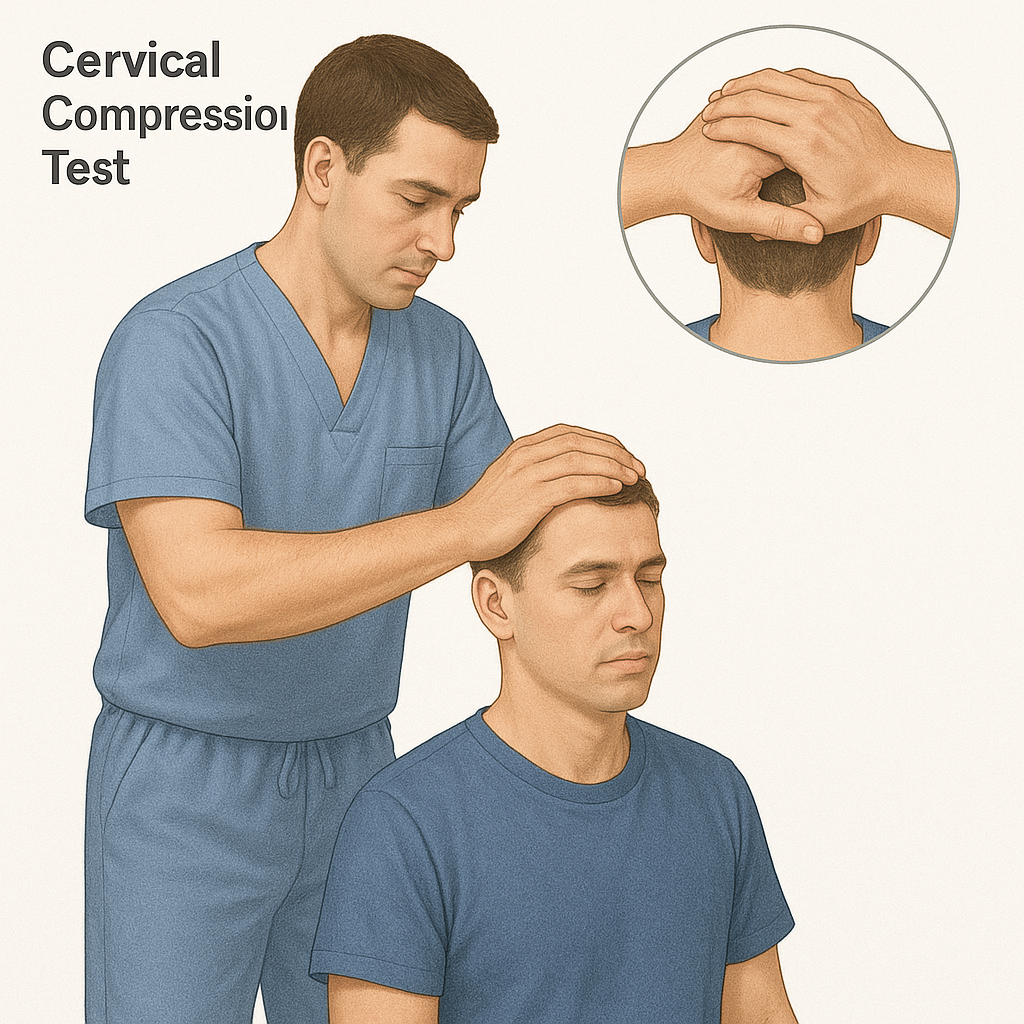
  • Cervical compression test
    • Patient sitting and neck passively moved into lateral flexion and rotation to the non-painful side, followed by extension. Repeat the painful side.
      • Identifies intervertebral foramen and/or facet dysfunction
    • Positive: pain and paresthesia in a dermatomal pattern of cervical root or localized pain in the neck if facet dysfunction
Seated patient while the clinician, standing behind, presses straight down on the top of the head; an inset shows the clinician's interlocked hands on the head.
Cervical compression test
Achievable
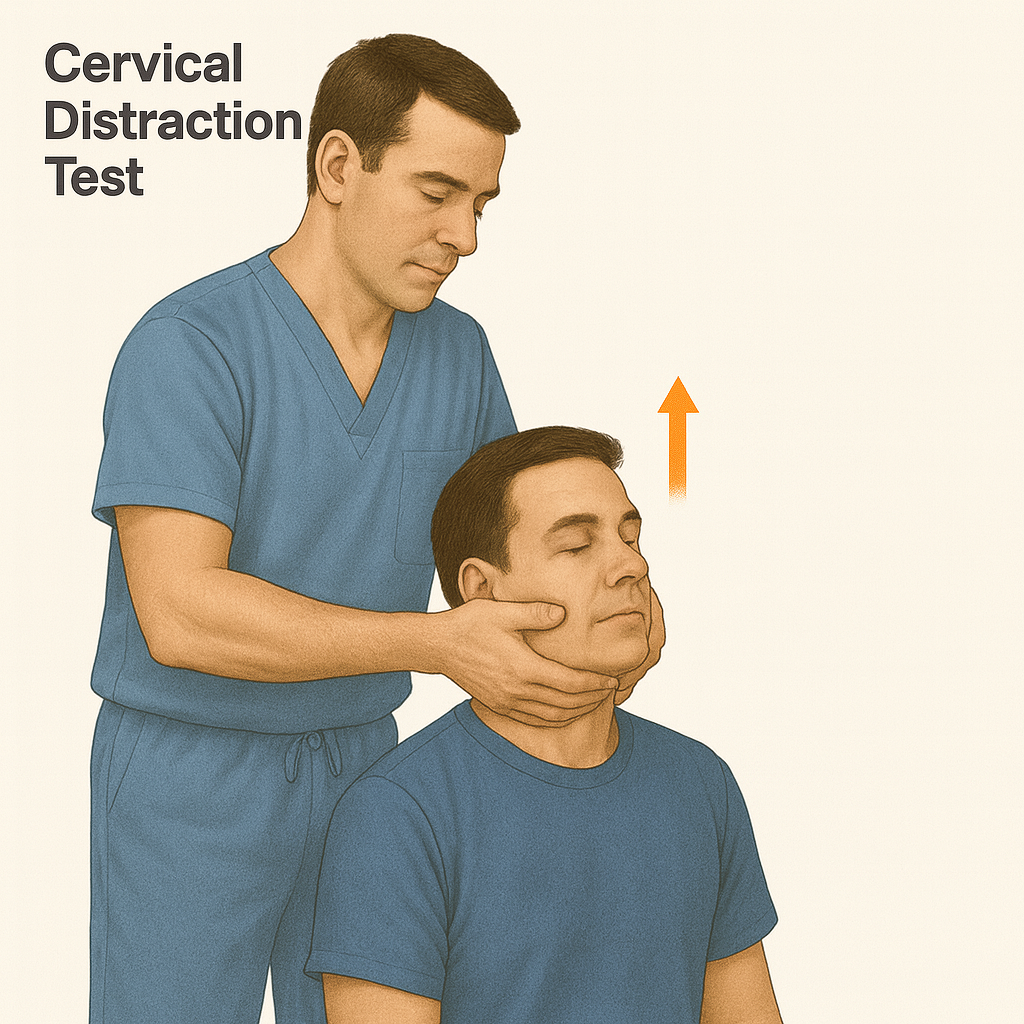
  • Distraction test
    • Patient sitting with head passively distracted
      • Identifies intervertebral foramen and/or facet dysfunction
    • Positive: decrease in symptoms or decrease in upper limb pain
Seated patient while the clinician, standing behind, cradles the jaw in both hands and lifts the head upward.
Distraction test
Achievable
  • Lhermitte’s sign
    • Patient sitting upright; the therapist passively flexes the patient’s neck (chin toward chest), or the patient actively flexes their own neck
      • Identifies upper motor neuron lesions (often associated with multiple sclerosis)
    • Positive: a brief, electric shock-like sensation traveling down the spine and into the upper or lower limbs
Seated patient bending the neck forward while the clinician guides the head from behind; an inset shows an electric sensation running down the spine.
Lhermitte's sign
Achievable

Clearing the cervical spine after trauma

  • Canadian C-Spine Rule
    • A decision tool for clearing the cervical spine without imaging in alert, stable trauma patients
    • Imaging is needed for age 65 or older, a dangerous mechanism or paresthesias. Otherwise, if a low-risk factor allows range of motion to be assessed, a patient who can actively rotate the neck 45 degrees to each side needs no imaging.

Watch out for: Don’t confuse Lhermitte’s sign with Spurling’s test. Lhermitte’s is elicited by cervical flexion alone and produces a brief, electric shock-like sensation traveling down the spine into one or more limbs - pointing to spinal cord or upper motor neuron involvement (as in multiple sclerosis or cervical myelopathy). Spurling’s test instead reproduces pain or paresthesia in a single dermatomal pattern, pointing to nerve root or lower motor neuron involvement, and these symptoms often ease with distraction. The provocation movement and the structure being stressed are different, so keep the two categories separate.

PTA role and safety

  • PTA performs tests as data collection only; interpretation/diagnosis/plan changes stay with supervising PT
  • Any red-flag finding = stop test/intervention immediately, continue monitoring, notify PT right away

Vascular/stability screens (performed first)

  • Vertebral artery test: neck extended + rotated, held ~30 sec, monitor eyes/speech
    • Tests vertebrobasilar vascular integrity
    • Positive (red flag): dizziness, diplopia, dysarthria, dysphagia, drop attacks, nystagmus, nausea, numbness (“5 Ds and 3 Ns”)
    • Current evidence favors broader cervical arterial dysfunction screening (history, risk factors, BP, cranial nerve exam) over positional test alone
  • Flexion rotation test: max neck flexion + rotation L/R, supine
    • Provokes atlantoaxial dysfunction/cervicogenic headache
    • Positive: headache reproduced, or >10° rotation asymmetry side-to-side
  • Alar ligament test: stabilize C2, passively side-bend head each side
    • Tests alar ligament integrity
    • Positive: excessive side-bend motion or soft end-feel (normal = minimal motion, firm end-feel)
    • Suggests upper cervical instability → stop test, report to supervising PT

Nerve root/cord provocation tests

  • Shared logic: compression tests (Spurling’s, cervical compression) narrow foramen to provoke symptoms; distraction opens foramen to relieve symptoms
  • Spurling’s test: seated, lateral bend toward involved side + downward pressure
    • Positive: dermatomal pain/paresthesia → suggests cervical radiculopathy
  • Cervical compression test: lateral flexion/rotation to non-painful side then extension, repeat painful side
    • Positive: dermatomal symptoms (root) or localized neck pain (facet dysfunction)
  • Distraction test: seated, head passively distracted
    • Positive: decreased symptoms/upper limb pain → confirms foraminal/facet involvement
  • Lhermitte’s sign: passive/active neck flexion only
    • Positive: electric shock sensation down spine into limbs → suggests upper motor neuron lesion/cord involvement (e.g., MS, myelopathy)
    • Key distinction: Lhermitte’s = flexion-only, shock-like, cord/UMN sign; Spurling’s = compression + lateral bend, dermatomal pain, nerve root/LMN sign

Sign up for free to take 10 quiz questions on this topic

Previous
Next  | 5.11.2 Thoracolumbar, sacroiliac, and TMJ tests
All rights reserved ©2016 - 2026 Achievable, Inc.

Cervical spine tests

The PTA performs these cervical special tests as part of data collection within the PT’s plan of care - interpreting findings, diagnosing, and changing the plan of care remain the supervising PT’s responsibility. If a test produces a red-flag sign, stop immediately, keep monitoring the patient, and notify the supervising PT right away.

Safety and stability screens (perform first)

  • Vertebral artery test
    • The examiner carefully extends the patient’s neck, then rotates the head to one side and holds it there for up to 30 seconds. The patient’s eyes are kept open and monitored, and they are usually asked to count backward or speak to check for changes in their voice.
      • Tests the integrity of the vertebrobasilar vascular system
    • Positive: dizziness, diplopia, dysarthria, dysphagia, drop attacks, nystagmus, nausea, or numbness. This is a red flag - stop the test and any cervical spine intervention immediately, continue monitoring the patient, and notify the supervising PT right away.
      • Current evidence questions the validity and reliability of this positional test on its own. Rather than relying on the positional test alone as the standard of care, current frameworks call for a broader cervical arterial dysfunction screen before cervical spine mobilization or manipulation - including patient history, risk factors, blood pressure, and a cranial nerve exam - to identify patients at risk before proceeding
  • Flexion rotation test
    • Patient in supine with maximal flexion of neck performed with rotation to left and right
      • Provocative test for atlantoaxial dysfunction or cervicogenic headache
      • Positive: headache reproduced, or rotation to one side reduced by more than 10 degrees compared with the other side
  • Alar ligament test
    • Patient seated (or supine) with the neck in slight flexion. The therapist stabilizes the C2 spinous process and passively side-bends the head to each side.
      • Tests the integrity of the alar ligament
    • Positive: excessive side-bending motion compared with the other side, or a soft end-feel (with an intact alar ligament, little to no side-bending occurs and the end-feel is firm). This suggests alar ligament laxity or upper cervical instability - stop and report the finding to the supervising PT.

Nerve root and cord tests (Spurling’s and compression narrow the foramen to provoke radicular symptoms; distraction opens it to relieve them)

  • Spurling’s test (foraminal compression)
    • Patient sitting with head laterally bending towards the involved side while the therapist applies pressure straight down
      • Provokes/suggests cervical radiculopathy
      • Cervical radiculopathy is compression of a cervical nerve root, and the pain travels down the arm in the area served by that root; extending the neck or turning the head toward the side narrows the foramen and increases symptoms, so extension positions are avoided, while traction in slight flexion opens the foramen
    • Positive: pain and paresthesia in a dermatomal pattern of the cervical root
  • Cervical compression test
    • Patient sitting and neck passively moved into lateral flexion and rotation to the non-painful side, followed by extension. Repeat the painful side.
      • Identifies intervertebral foramen and/or facet dysfunction
    • Positive: pain and paresthesia in a dermatomal pattern of cervical root or localized pain in the neck if facet dysfunction
  • Distraction test
    • Patient sitting with head passively distracted
      • Identifies intervertebral foramen and/or facet dysfunction
    • Positive: decrease in symptoms or decrease in upper limb pain
  • Lhermitte’s sign
    • Patient sitting upright; the therapist passively flexes the patient’s neck (chin toward chest), or the patient actively flexes their own neck
      • Identifies upper motor neuron lesions (often associated with multiple sclerosis)
    • Positive: a brief, electric shock-like sensation traveling down the spine and into the upper or lower limbs

Clearing the cervical spine after trauma

  • Canadian C-Spine Rule
    • A decision tool for clearing the cervical spine without imaging in alert, stable trauma patients
    • Imaging is needed for age 65 or older, a dangerous mechanism or paresthesias. Otherwise, if a low-risk factor allows range of motion to be assessed, a patient who can actively rotate the neck 45 degrees to each side needs no imaging.

Watch out for: Don’t confuse Lhermitte’s sign with Spurling’s test. Lhermitte’s is elicited by cervical flexion alone and produces a brief, electric shock-like sensation traveling down the spine into one or more limbs - pointing to spinal cord or upper motor neuron involvement (as in multiple sclerosis or cervical myelopathy). Spurling’s test instead reproduces pain or paresthesia in a single dermatomal pattern, pointing to nerve root or lower motor neuron involvement, and these symptoms often ease with distraction. The provocation movement and the structure being stressed are different, so keep the two categories separate.

Key points

PTA role and safety

  • PTA performs tests as data collection only; interpretation/diagnosis/plan changes stay with supervising PT
  • Any red-flag finding = stop test/intervention immediately, continue monitoring, notify PT right away

Vascular/stability screens (performed first)

  • Vertebral artery test: neck extended + rotated, held ~30 sec, monitor eyes/speech
    • Tests vertebrobasilar vascular integrity
    • Positive (red flag): dizziness, diplopia, dysarthria, dysphagia, drop attacks, nystagmus, nausea, numbness (“5 Ds and 3 Ns”)
    • Current evidence favors broader cervical arterial dysfunction screening (history, risk factors, BP, cranial nerve exam) over positional test alone
  • Flexion rotation test: max neck flexion + rotation L/R, supine
    • Provokes atlantoaxial dysfunction/cervicogenic headache
    • Positive: headache reproduced, or >10° rotation asymmetry side-to-side
  • Alar ligament test: stabilize C2, passively side-bend head each side
    • Tests alar ligament integrity
    • Positive: excessive side-bend motion or soft end-feel (normal = minimal motion, firm end-feel)
    • Suggests upper cervical instability → stop test, report to supervising PT

Nerve root/cord provocation tests

  • Shared logic: compression tests (Spurling’s, cervical compression) narrow foramen to provoke symptoms; distraction opens foramen to relieve symptoms
  • Spurling’s test: seated, lateral bend toward involved side + downward pressure
    • Positive: dermatomal pain/paresthesia → suggests cervical radiculopathy
  • Cervical compression test: lateral flexion/rotation to non-painful side then extension, repeat painful side
    • Positive: dermatomal symptoms (root) or localized neck pain (facet dysfunction)
  • Distraction test: seated, head passively distracted
    • Positive: decreased symptoms/upper limb pain → confirms foraminal/facet involvement
  • Lhermitte’s sign: passive/active neck flexion only
    • Positive: electric shock sensation down spine into limbs → suggests upper motor neuron lesion/cord involvement (e.g., MS, myelopathy)
    • Key distinction: Lhermitte’s = flexion-only, shock-like, cord/UMN sign; Spurling’s = compression + lateral bend, dermatomal pain, nerve root/LMN sign

More from Special tests of the spine, pelvis, and temporomandibular joint

  • Thoracolumbar, sacroiliac, and TMJ tests