







Shoulder instability and rotator cuff tests
Special tests help identify which anatomical structure is likely contributing to a patient’s symptoms. Each test below follows the same basic pattern: a technique the examiner performs, and a positive finding that points to a specific structure or condition. As you read through each test, focus on three things: how it’s performed, what a positive result looks like, and what structure or condition it implicates.
Shoulder special tests
Instability tests
Below are tests to assess if this condition is present:
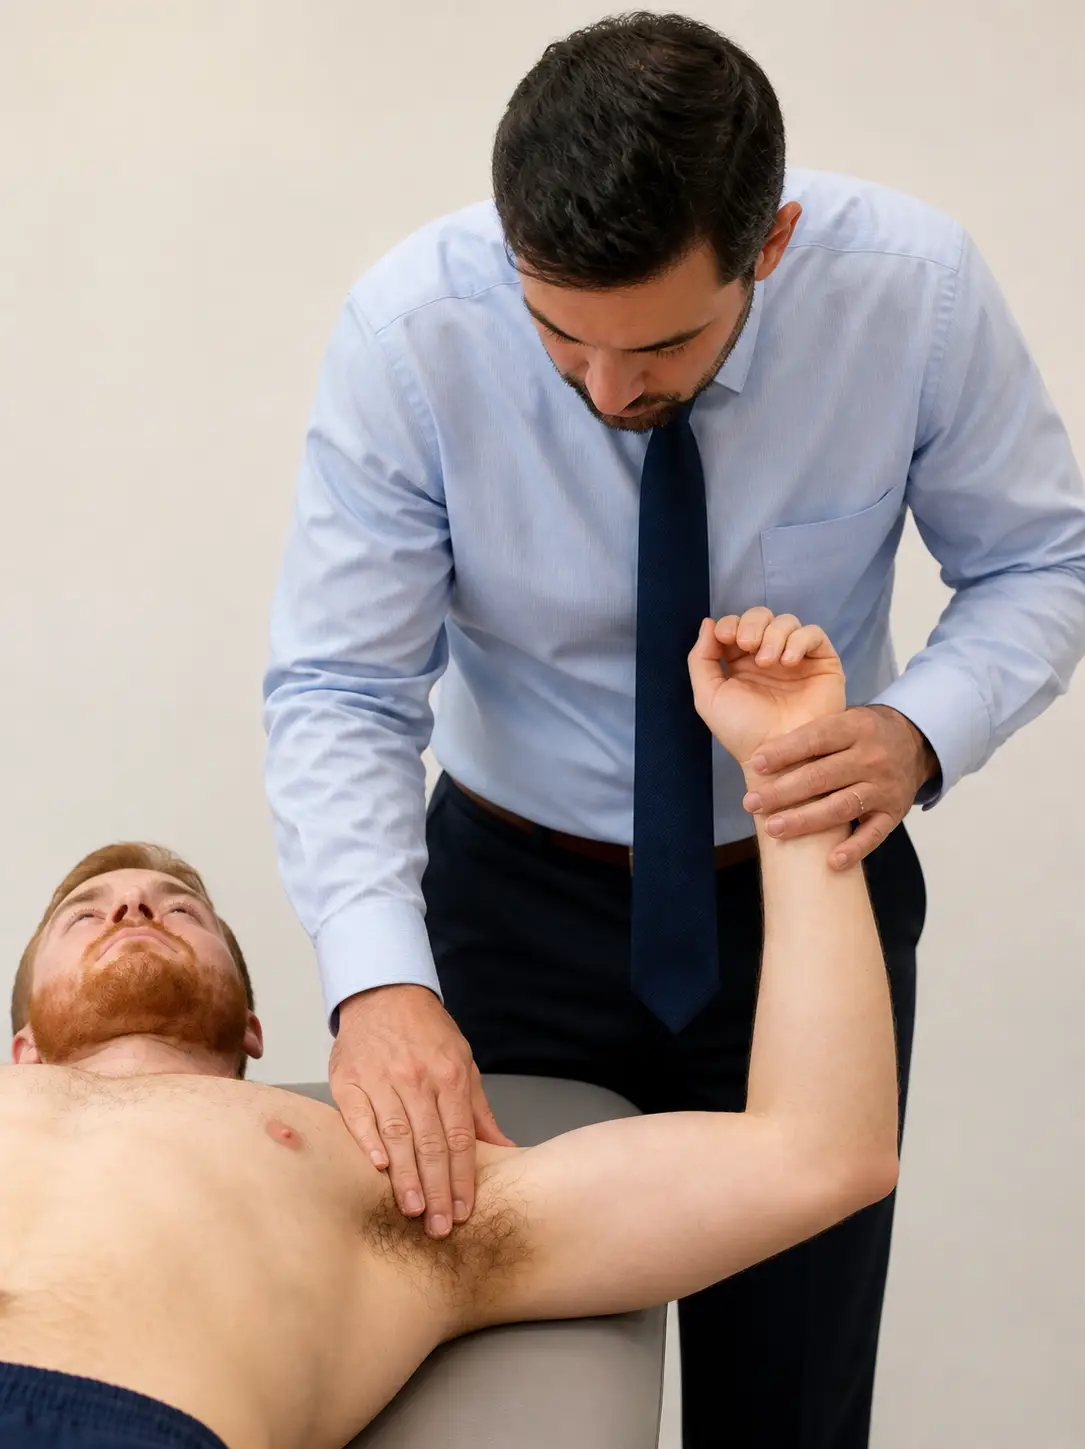
- Apprehension test (tests anterior instability)
- Patient is supine, the shoulder is in 90 degrees of abduction; therapist attempts to externally rotate
- Positive: patient seems apprehensive about performing movement and resists motion
- Patient is supine, the shoulder is in 90 degrees of abduction; therapist attempts to externally rotate
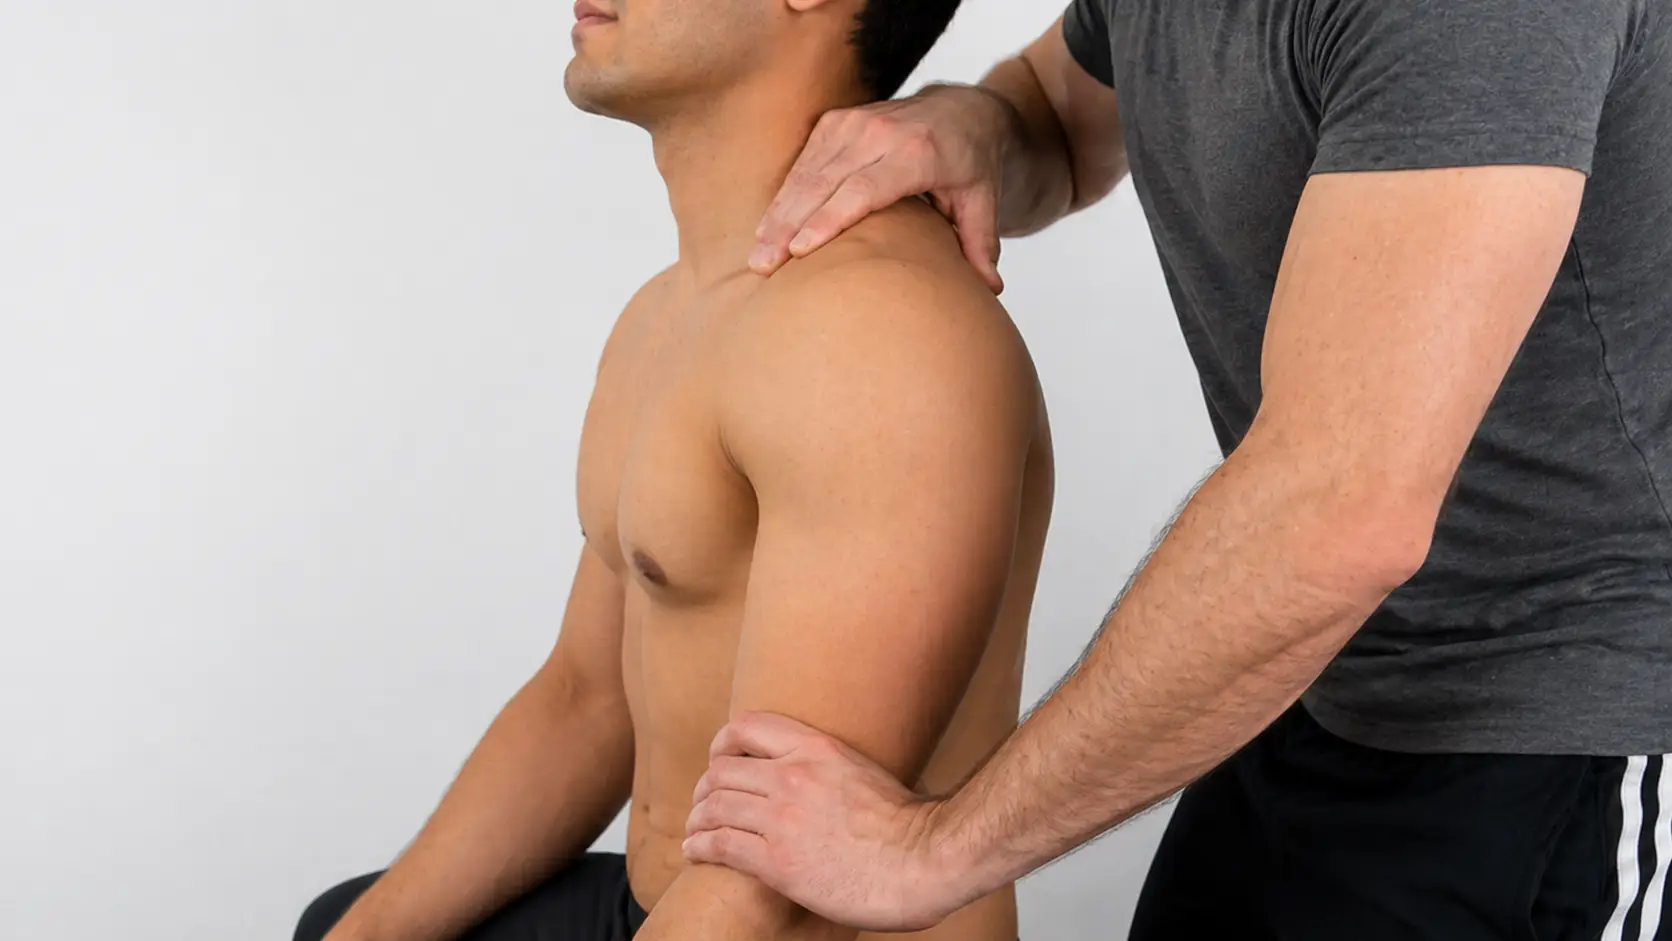
- Sulcus sign (tests inferior instability; often seen with multidirectional instability)
- Patient stands with arm relaxed at the side; therapist pulls the arm distally
- Positive: presence of sulcus inferior to the acromion with symptom reproduction
- Patient stands with arm relaxed at the side; therapist pulls the arm distally
Rotator cuff tests
Below are tests to assess if this condition is present:
- Drop arm test
- Patient seated with the shoulder passively abducted to 90 degrees and externally rotated; patient instructed to slowly lower the arm back to the side
- Positive: patient is unable to lower their arm down slowly and suddenly drops it to the side without control
- Patient seated with the shoulder passively abducted to 90 degrees and externally rotated; patient instructed to slowly lower the arm back to the side
- Infraspinatus/supraspinatus muscle test
- Patient is seated or standing; therapist resists external rotation with the arm in the neutral position and adducted to the trunk
- Positive: patient is unable to sustain external rotation
- Patient is seated or standing; therapist resists external rotation with the arm in the neutral position and adducted to the trunk
- External rotation lag sign
- Patient is seated or standing with the shoulder passively abducted to 90 degrees and externally rotated
- Positive: patient is unable to maintain external rotation
- Patient is seated or standing with the shoulder passively abducted to 90 degrees and externally rotated
- Lift off test (Gerber’s test)
- Patient is standing with the shoulder passively placed in internal rotation and the hand at waist level against the back
- Positive: patient is unable to lift off the back
- Patient is standing with the shoulder passively placed in internal rotation and the hand at waist level against the back
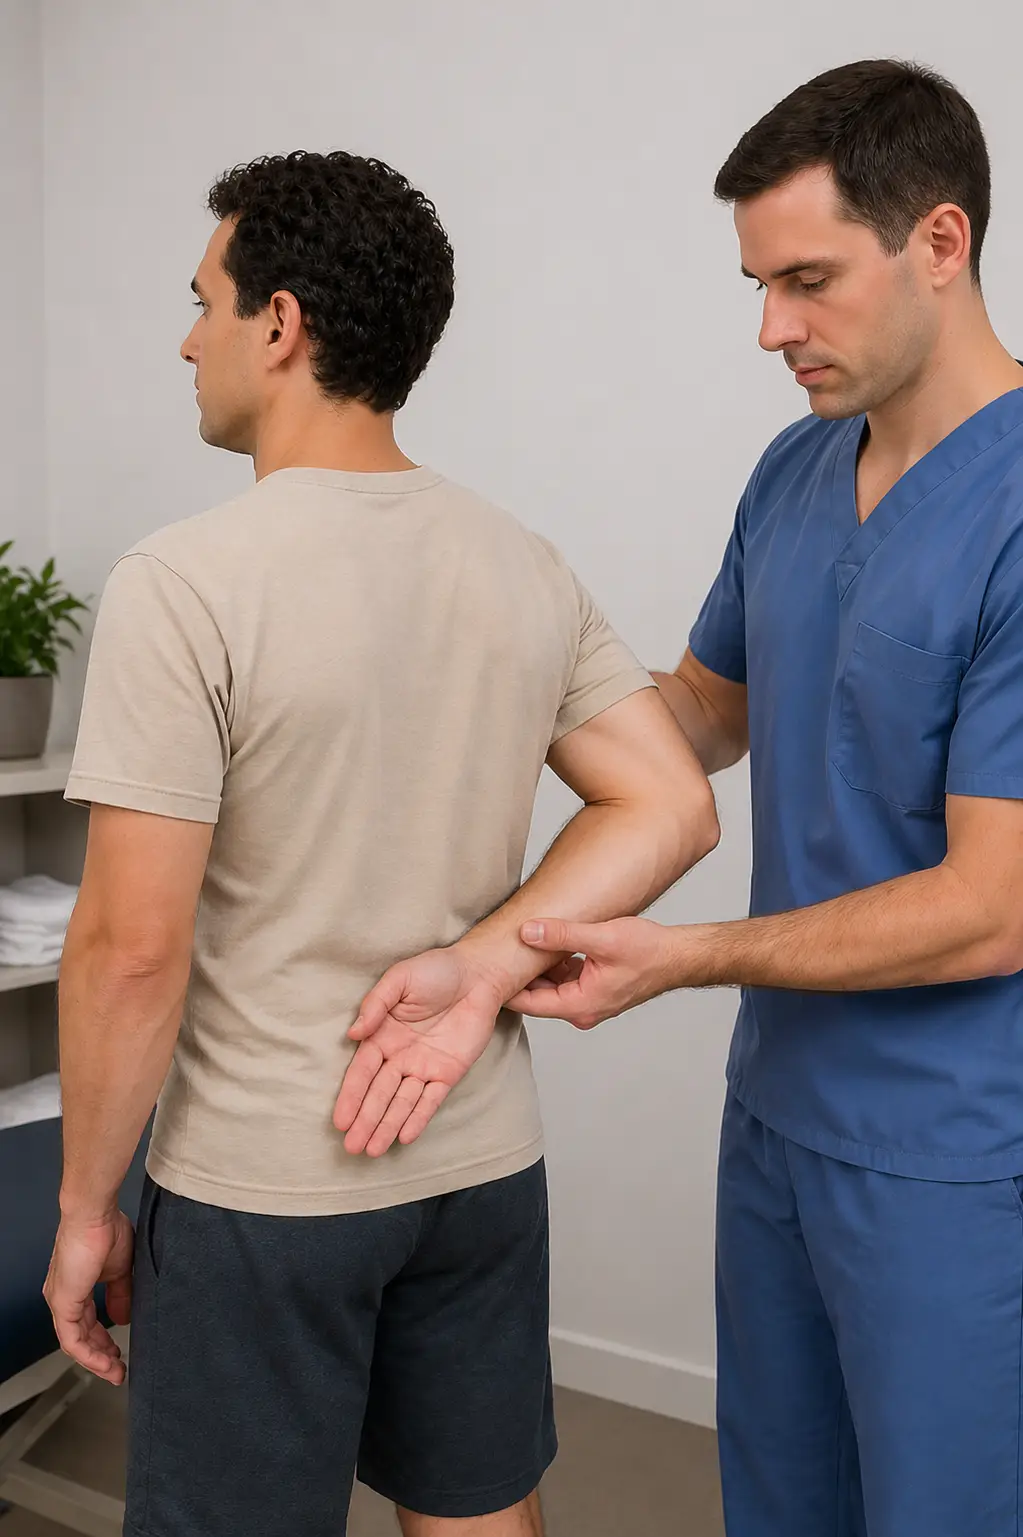
- Internal rotation lag sign
- Patient is seated with arm held behind the back in internal rotation, passively
- Positive: patient is unable to maintain internal rotation
- Patient is seated with arm held behind the back in internal rotation, passively
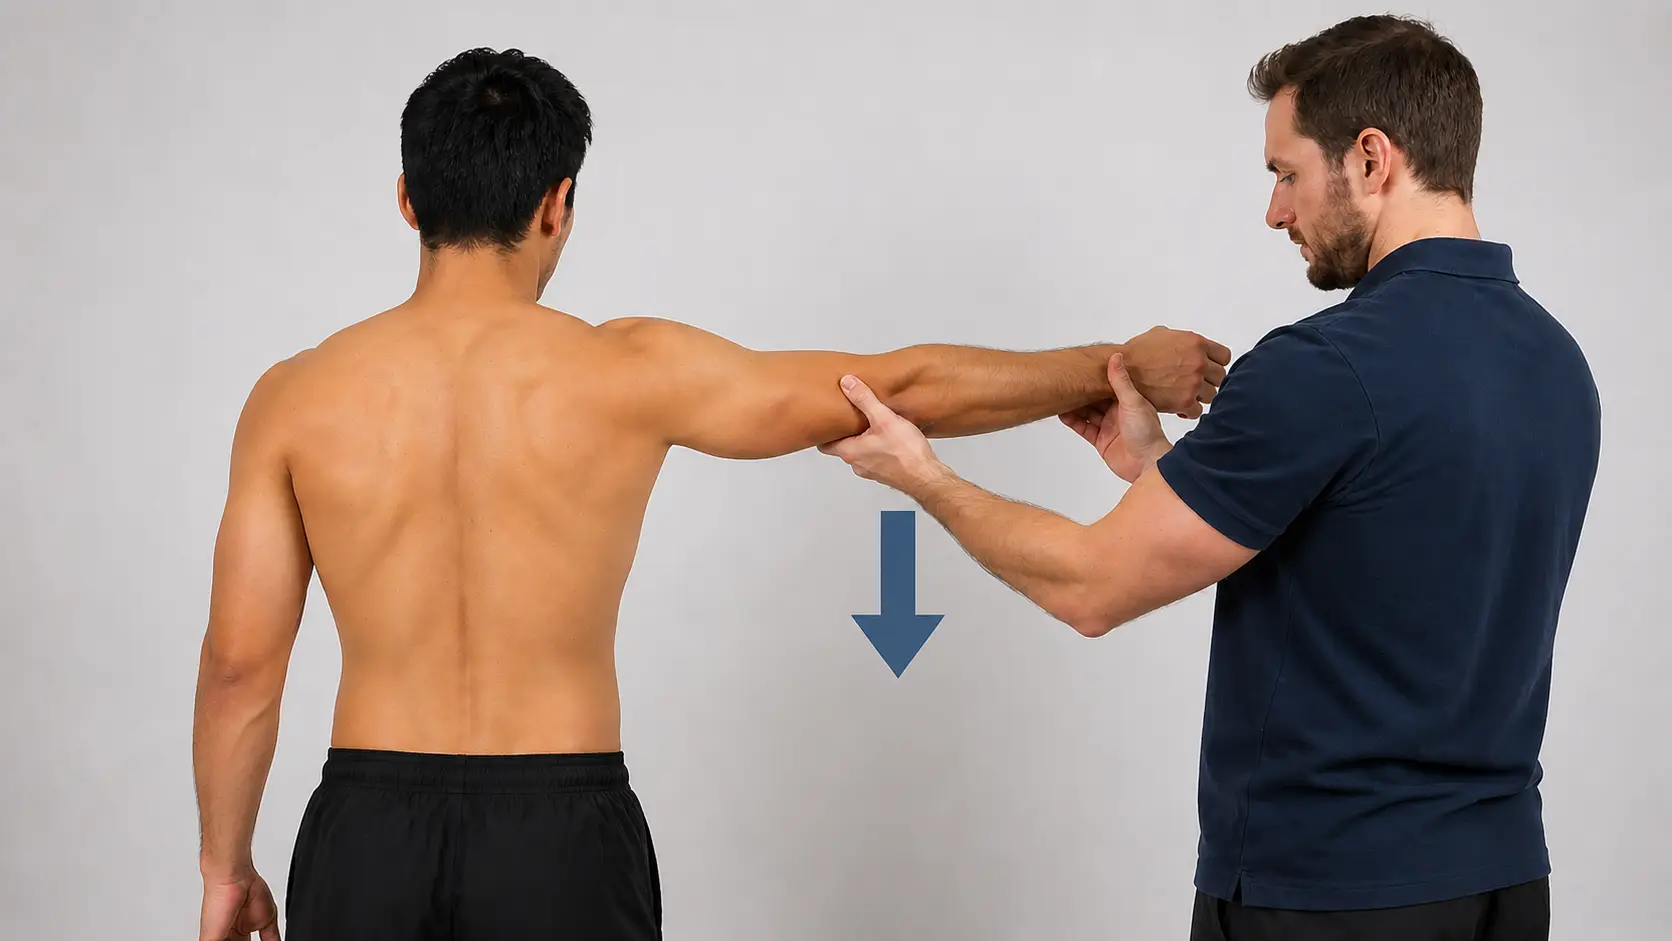
- Empty can test
- The patient stands or sits with their arms at their sides. The patient abducts their arm to 90 degrees, elbow extended, then internally rotates the shoulder so the thumb points toward the floor. The examiner applies downward pressure on the patient’s wrist or forearm.
- Tests the supraspinatus muscle
- Positive: pain in the shoulder, weakness in the arm, and the patient’s arm dropping involuntarily
- The patient stands or sits with their arms at their sides. The patient abducts their arm to 90 degrees, elbow extended, then internally rotates the shoulder so the thumb points toward the floor. The examiner applies downward pressure on the patient’s wrist or forearm.