


Achievable logoAchievable logo
NPTE-PTA
Sign in
Sign up
Purchase
Textbook
Practice exams
Support
How it works
Resources
Exam catalog
Mountain with a flag at the peak
Textbook
Introduction
1. Cardiopulmonary system
2. Pulmonary system
3. Neuromuscular system
4. Pediatrics
5. Musculoskeletal system
5.1 Anatomy of musculoskeletal system
5.2 Anatomical terminology and exercise training principles
5.3 Joint mechanics and phases of healing
5.4 Upper extremity anatomy
5.5 Special tests of upper extremity
5.6 Comparing clinical presentation and interventions for upper extremity
5.7 Lower extremity anatomy
5.8 Special tests of lower extremity
5.9 Comparing clinical presentation and interventions of lower extremity
5.10 Spine and pelvis anatomy
5.11 Special tests of the spine, pelvis, and temporomandibular joint
5.12 Comparing clinical presentation and interventions for the spine, pelvis, and temporomandibular joint
5.13 Other MSK conditions
5.14 Gait
5.15 Prosthetics
5.16 Orthotics
5.17 Medications, imaging, and fractures
5.18 Surgical protocols
6. Other system
7. Non systems
Wrapping up
Achievable logoAchievable logo
5.15 Prosthetics
Achievable NPTE-PTA
5. Musculoskeletal system
Our NPTE-PTA course is now in "early access" - get 50% off for a limited time.

Prosthetics

7 min read
Font
Discuss
Share
Feedback

Levels of amputations

Upper extremity

  • Finger or partial hand: Removal of one or more fingers or part of the hand
  • Wrist disarticulation: Removal of the hand at the wrist joint
  • Transradial (below elbow): Removal of the forearm below the elbow joint
  • Elbow disarticulation: Removal of the arm at the elbow joint
  • Transhumeral (above elbow): Removal of the arm above the elbow joint
  • Shoulder disarticulation: Removal of the arm at the shoulder joint

Lower extremity

  • Toe or partial foot: Removal of one or more toes or part of the foot
  • Ankle disarticulation (Syme’s amputation): Removal of the foot at the ankle joint, keeping the heel pad so the residual limb can bear weight at its end
  • Transtibial (below knee): Removal of the leg below the knee joint
  • Knee disarticulation: Removal of the leg at the knee joint
  • Transfemoral (above knee): Removal of the leg above the knee joint
  • Hip disarticulation: Removal of the leg at the hip joint

Focus of NPTE is on lower extremity prosthesis

Components of prosthesis

Primary components

  • Sockets
    • custom-molded prosthetic that will have total contact with residual limb; goal is equal distribution of tissue load throughout the socket
  • Liners
    • Silicone barrier between residual limb and socket to decrease shear forces
  • Socks
    • Used to aid in changing the size of the residual limb
  • Terminal device
    • Interface between prosthetic limb and external environment
      • Upper limb: the terminal device is a hand or a hook
      • Lower limb: the terminal device is the foot

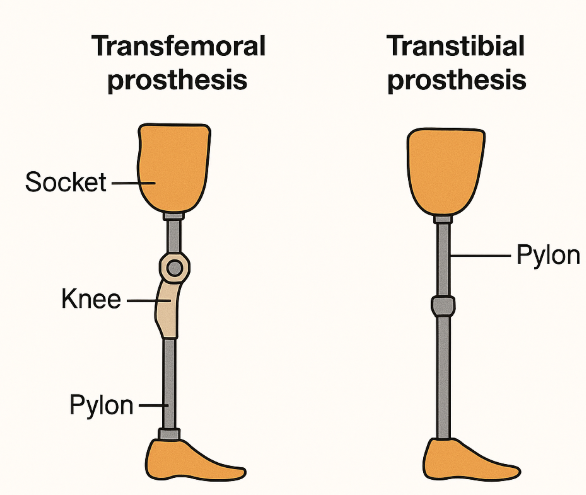
Components of a prosthesis specifically for transtibial amputation

Ankle-foot assembly

  • SACH foot (solid ankle cushioned heel):
    • A simple, durable, and lightweight foot with a solid ankle joint
  • Single-axis foot:
    • Features a hinged ankle joint that allows for up-and-down movement, enhancing knee stability.
  • Multi-axis foot:
    • Similar to a single-axis foot, but also allows for side-to-side movement, making it better suited for uneven terrain
  • Microprocessor-controlled (MPC) feet:
    • These feet use sensors and a computer to adjust the ankle’s position and resistance based on the user’s movements and the environment

Shank

  • Endoskeleton prosthesis:
    • Structure: Features a tubular structure connecting the primary components, like the socket, suspension system, foot, and knee unit
    • Appearance: Often covered with cosmetic foam
    • Advantages: Endoskeletal prostheses are adjustable and lighter than exoskeletal prostheses.
    • Disadvantages: Less durable than exoskeletal prostheses
  • Exoskeleton prosthesis:
    • Structure: Has a hard outer shell that provides structural strength and cosmetic shape
    • Materials: Traditionally constructed from wood or plastic
    • Durability: More durable than endoskeletal prostheses
    • Advantages: May be preferred by people who do physical labor or are in harsh environments
    • Disadvantages: Less customizable than endoskeletal prostheses.

Socket

  • Patellar tendon bearing (PTB) sockets:
    • Focus: PTB sockets, often used for below-knee amputations, focus weight-bearing stress on pressure-tolerant structures like the patellar tendon and medial tibia flare
      • Advantages:
        • Can be a good choice for patients with shorter or bony residual limbs
        • Easier to don/doff for amputees with poor hand dexterity, poor eyesight, or hemiparesis
        • Can be modified to accommodate changes in the residual limb after amputation
      • Disadvantages:
        • May not be ideal for patients with residual limb scar tissue or chronic skin breakdown
  • Total surface bearing (TSB) sockets:
    • Focus: TSB sockets, also used for below-knee amputations, distribute weight evenly across the entire limb surface, reducing pressure points
      • Advantages:
        • Often used with gel liners, which cushion the limb and protect the skin, making them great for amputees with scar tissue or sensitive skin
        • Offer better suspension than PTB designs, often using locking pins or suction systems
      • Disadvantages:
        • Can be more difficult to don/doff than PTB sockets
Prosthesis components
Achievable

Components of prosthesis specifically for transfemoral amputation

Knee unit

  • Single-axis knees:
    • Mechanism: A single pivot point, resembling a simple hinge
    • Stability: Offers good stability during the stance (weight-bearing) phase but may require more effort for the swing (forward movement) phase
    • Suitable for: Individuals with lower activity levels, those who can voluntarily stabilize the knee
    • Types:
      • Manual locking: The knee can be locked in extension for stability, and unlocked manually for sitting
      • Constant friction: Provide a constant resistance to knee flexion during the swing phase, aiding in stability
  • Polycentric (multiaxis) knees:
    • Mechanism: Multiple pivot points, allowing for a more natural and efficient gait, particularly during the swing phase
    • Stability: Shorten the prosthesis during swing, reducing the risk of tripping and improving stability
    • Suitable for: Active individuals, those with longer residual limbs, or those who require a more natural gait
    • Types:
      • Hydraulic/pneumatic: Use fluid or air to control the swing phase, allowing for smoother and more natural movement
  • Microprocessor knees:
    • Mechanism: Use of sensors and electronics to adjust the resistance to knee flexion and extension based on the user’s gait and activity level
    • Benefits: Improve stability, reduce energy expenditure, and allow for a more natural and comfortable gait
    • Suitable for: Highly active individuals, those who require a high level of stability and control, or those who want to maximize their mobility

Socket

  • Ischial containment (IC) sockets
    • These designs feature a narrow medial-lateral dimension with the ischium (part of the pelvic bone) encapsulated within the socket, rather than sitting on the brim
  • Sub-ischial sockets
    • These sockets have a lower proximal trim line than IC sockets, and are often used with vacuum-assisted suspension
  • Quadrilateral (quad) sockets
    • These were historically the most common type, but are less common now, although still used for some patients
  • Direct socket
    • A novel method of fabricating a laminated interface directly onto the residual limb

Keys for transfemoral socket trim lines

  • In a transfemoral socket, the posterior and medial walls are lower than the anterior and lateral walls
  • This allows room for the groin and sacrum

Prosthetic gait deviations

Prosthetic gait deviations refer to any variations from a normal walking pattern that occur in individuals using prosthetic limbs, often due to compensatory strategies or issues with the prosthesis itself.

Vaulting

  • Definition: An attempt to lengthen the stance phase on the intact limb by knee extension and ankle plantar flexion during mid-stance
  • Causes:
    • Limb too long
    • Poorly suspended prosthesis
    • Excessive plantarflexion

Circumduction

  • Definition: The prosthetic limb travels in a lateral arch during swing.
  • Causes:
    • Excessive abduction of the prosthesis
    • Prosthesis too long
    • Inadequate suspension
    • Excessive plantarflexion of the prosthetic foot
    • Excessive knee friction or a locked knee unit

Abducted gait pattern

  • Definition: The prosthetic limb is carried in an abducted position throughout the swing and stance phase
  • Causes:
    • Outset prosthetic foot
    • Prosthesis too long
    • Medially placed intact foot

Knee instability

  • Definition: Excessive knee flexion on the prosthetic side in early stance
  • Causes:
    • Excessive foot dorsiflexion
    • Excessive socket flexion
    • Posterior translation of foot/pylon
    • Excessively hard heel cushion on prosthetic heel
    • Weakness of the knee extensors

Reduced toe clearance

  • Definition: Prosthetic toe drags or catches during the swing phase
  • Causes:
    • Prosthetic limb too long
    • Inadequate suspension
    • Residual limb not getting into prosthetic socket all the way
    • Excessive plantarflexion of the prosthetic foot

Pelvic drop

  • Definition: The pelvis on the prosthetic side drops on initial contact as if “stepping into a hole.”
  • Causes:
    • Prosthetic limb too short
    • Residual limb has shrunk relative to the socket
    • Excessively compliant heel cushion

Lateral trunk lean over prosthesis (Trendelenburg)

  • Definition: Trunk bends laterally over the prosthesis (compensated Trendelenburg) during stance
  • Causes:
    • Inadequate adduction of the socket
    • Prosthesis too short
    • Outset foot
    • Medial wall too high, causing pain
    • Gapping at the lateral wall of the socket

Medial/lateral whip

  • Definition: Abrupt medial or lateral movement of the prosthetic heel during swing
  • Causes:
    • Excessive external or internal rotation of the socket
    • Socket too tight
    • Inadequate suspension
    • Excessive valgus of prosthetic knee

Increased knee flexion

  • Definition: Long prosthetic step (decreased stance time on prosthesis)
  • Causes:
    • Painful socket - residual limb; painful
    • Prosthesis too long
    • Excessive foot dorsiflexion
    • Excessively hard heel cushion on prosthetic heel

Levels of amputations - Upper extremity

  • Progression: finger/partial hand → wrist disarticulation → transradial (below elbow) → elbow disarticulation → transhumeral (above elbow) → shoulder disarticulation

Levels of amputations - Lower extremity

  • Progression: toe/partial foot → ankle disarticulation (Syme’s) → transtibial (below knee) → knee disarticulation → transfemoral (above knee) → hip disarticulation
  • Syme’s amputation preserves heel pad for end-weight bearing
  • NPTE focuses primarily on lower extremity prosthetics

Primary components of prosthesis

  • Socket: custom-molded, total contact, equal tissue load distribution
  • Liner: silicone barrier reducing shear forces
  • Sock: adjusts residual limb size/fit
  • Terminal device: hand/hook (upper limb) or foot (lower limb)

Transtibial prosthesis - Ankle-foot assembly

  • SACH foot: solid ankle, simple/durable/lightweight
  • Single-axis foot: hinged ankle, up-down movement, enhances knee stability
  • Multi-axis foot: adds side-to-side movement, good for uneven terrain
  • Microprocessor-controlled (MPC) feet: sensors adjust ankle position/resistance dynamically

Transtibial prosthesis - Shank

  • Endoskeletal: tubular structure, cosmetic foam cover, adjustable/lighter, less durable
  • Exoskeletal: hard outer shell, wood/plastic, more durable, less customizable, good for labor/harsh environments

Transtibial prosthesis - Socket

  • PTB (patellar tendon bearing): loads pressure-tolerant areas (patellar tendon, medial tibial flare); good for short/bony limbs, easier don/doff; not ideal with scar tissue/skin breakdown
  • TSB (total surface bearing): even weight distribution, used with gel liners; better for scar tissue/sensitive skin; better suspension (pins/suction); harder to don/doff

Transfemoral prosthesis - Knee unit

  • Single-axis knee: simple hinge, stable in stance, more effort in swing; suited for lower activity levels
    • Manual locking: locks in extension, manually unlocked for sitting
    • Constant friction: constant swing-phase resistance
  • Polycentric (multiaxis) knee: multiple pivot points, natural gait, shortens during swing (reduces tripping); suited for active users/longer limbs
    • Hydraulic/pneumatic: fluid/air control for smoother swing
  • Microprocessor knee: sensor-based adjustment, improves stability/reduces energy cost; best for highly active users

Transfemoral prosthesis - Socket

  • Ischial containment (IC): narrow M-L dimension, ischium encapsulated in socket
  • Sub-ischial: lower proximal trim line, often vacuum-assisted suspension
  • Quadrilateral (quad): historically common, now less used
  • Direct socket: laminated interface fabricated directly on residual limb

Transfemoral socket trim lines

  • Posterior and medial walls lower than anterior/lateral walls
  • Allows room for groin and sacrum

Prosthetic gait deviations - overview

  • Deviations from normal gait due to prosthesis fit/alignment issues or compensatory strategies

Vaulting

  • Rising on intact limb (knee extension, ankle plantarflexion) to lengthen stance
  • Causes: limb too long, poor suspension, excessive plantarflexion

Circumduction

  • Prosthetic limb swings in lateral arc during swing phase
  • Causes: excessive abduction, limb too long, poor suspension, excessive plantarflexion, excessive knee friction/locked knee

Abducted gait pattern

  • Limb held abducted throughout gait cycle
  • Causes: outset prosthetic foot, limb too long, medially placed intact foot

Knee instability

  • Excessive knee flexion in early stance
  • Causes: excessive dorsiflexion, excessive socket flexion, posterior foot/pylon translation, hard heel cushion, weak knee extensors

Reduced toe clearance

  • Toe drags/catches during swing
  • Causes: limb too long, poor suspension, incomplete limb insertion into socket, excessive plantarflexion

Pelvic drop

  • Pelvis drops on prosthetic side at initial contact (“stepping into a hole”)
  • Causes: limb too short, residual limb shrinkage, overly compliant heel cushion

Lateral trunk lean (Trendelenburg)

  • Trunk leans laterally over prosthesis during stance
  • Causes: inadequate socket adduction, limb too short, outset foot, high medial wall (pain), lateral wall gapping

Medial/lateral whip

  • Abrupt heel movement during swing
  • Causes: excessive socket rotation (internal/external), tight socket, poor suspension, excessive knee valgus

Increased knee flexion

  • Long prosthetic step, decreased stance time on prosthesis
  • Causes: painful socket/residual limb, limb too long, excessive dorsiflexion, hard heel cushion

Sign up for free to take 9 quiz questions on this topic

Previous
Next  | 5.16 Orthotics
All rights reserved ©2016 - 2026 Achievable, Inc.

Prosthetics

Levels of amputations

Upper extremity

  • Finger or partial hand: Removal of one or more fingers or part of the hand
  • Wrist disarticulation: Removal of the hand at the wrist joint
  • Transradial (below elbow): Removal of the forearm below the elbow joint
  • Elbow disarticulation: Removal of the arm at the elbow joint
  • Transhumeral (above elbow): Removal of the arm above the elbow joint
  • Shoulder disarticulation: Removal of the arm at the shoulder joint

Lower extremity

  • Toe or partial foot: Removal of one or more toes or part of the foot
  • Ankle disarticulation (Syme’s amputation): Removal of the foot at the ankle joint, keeping the heel pad so the residual limb can bear weight at its end
  • Transtibial (below knee): Removal of the leg below the knee joint
  • Knee disarticulation: Removal of the leg at the knee joint
  • Transfemoral (above knee): Removal of the leg above the knee joint
  • Hip disarticulation: Removal of the leg at the hip joint

Focus of NPTE is on lower extremity prosthesis

Components of prosthesis

Primary components

  • Sockets
    • custom-molded prosthetic that will have total contact with residual limb; goal is equal distribution of tissue load throughout the socket
  • Liners
    • Silicone barrier between residual limb and socket to decrease shear forces
  • Socks
    • Used to aid in changing the size of the residual limb
  • Terminal device
    • Interface between prosthetic limb and external environment
      • Upper limb: the terminal device is a hand or a hook
      • Lower limb: the terminal device is the foot

Components of a prosthesis specifically for transtibial amputation

Ankle-foot assembly

  • SACH foot (solid ankle cushioned heel):
    • A simple, durable, and lightweight foot with a solid ankle joint
  • Single-axis foot:
    • Features a hinged ankle joint that allows for up-and-down movement, enhancing knee stability.
  • Multi-axis foot:
    • Similar to a single-axis foot, but also allows for side-to-side movement, making it better suited for uneven terrain
  • Microprocessor-controlled (MPC) feet:
    • These feet use sensors and a computer to adjust the ankle’s position and resistance based on the user’s movements and the environment

Shank

  • Endoskeleton prosthesis:
    • Structure: Features a tubular structure connecting the primary components, like the socket, suspension system, foot, and knee unit
    • Appearance: Often covered with cosmetic foam
    • Advantages: Endoskeletal prostheses are adjustable and lighter than exoskeletal prostheses.
    • Disadvantages: Less durable than exoskeletal prostheses
  • Exoskeleton prosthesis:
    • Structure: Has a hard outer shell that provides structural strength and cosmetic shape
    • Materials: Traditionally constructed from wood or plastic
    • Durability: More durable than endoskeletal prostheses
    • Advantages: May be preferred by people who do physical labor or are in harsh environments
    • Disadvantages: Less customizable than endoskeletal prostheses.

Socket

  • Patellar tendon bearing (PTB) sockets:
    • Focus: PTB sockets, often used for below-knee amputations, focus weight-bearing stress on pressure-tolerant structures like the patellar tendon and medial tibia flare
      • Advantages:
        • Can be a good choice for patients with shorter or bony residual limbs
        • Easier to don/doff for amputees with poor hand dexterity, poor eyesight, or hemiparesis
        • Can be modified to accommodate changes in the residual limb after amputation
      • Disadvantages:
        • May not be ideal for patients with residual limb scar tissue or chronic skin breakdown
  • Total surface bearing (TSB) sockets:
    • Focus: TSB sockets, also used for below-knee amputations, distribute weight evenly across the entire limb surface, reducing pressure points
      • Advantages:
        • Often used with gel liners, which cushion the limb and protect the skin, making them great for amputees with scar tissue or sensitive skin
        • Offer better suspension than PTB designs, often using locking pins or suction systems
      • Disadvantages:
        • Can be more difficult to don/doff than PTB sockets

Components of prosthesis specifically for transfemoral amputation

Knee unit

  • Single-axis knees:
    • Mechanism: A single pivot point, resembling a simple hinge
    • Stability: Offers good stability during the stance (weight-bearing) phase but may require more effort for the swing (forward movement) phase
    • Suitable for: Individuals with lower activity levels, those who can voluntarily stabilize the knee
    • Types:
      • Manual locking: The knee can be locked in extension for stability, and unlocked manually for sitting
      • Constant friction: Provide a constant resistance to knee flexion during the swing phase, aiding in stability
  • Polycentric (multiaxis) knees:
    • Mechanism: Multiple pivot points, allowing for a more natural and efficient gait, particularly during the swing phase
    • Stability: Shorten the prosthesis during swing, reducing the risk of tripping and improving stability
    • Suitable for: Active individuals, those with longer residual limbs, or those who require a more natural gait
    • Types:
      • Hydraulic/pneumatic: Use fluid or air to control the swing phase, allowing for smoother and more natural movement
  • Microprocessor knees:
    • Mechanism: Use of sensors and electronics to adjust the resistance to knee flexion and extension based on the user’s gait and activity level
    • Benefits: Improve stability, reduce energy expenditure, and allow for a more natural and comfortable gait
    • Suitable for: Highly active individuals, those who require a high level of stability and control, or those who want to maximize their mobility

Socket

  • Ischial containment (IC) sockets
    • These designs feature a narrow medial-lateral dimension with the ischium (part of the pelvic bone) encapsulated within the socket, rather than sitting on the brim
  • Sub-ischial sockets
    • These sockets have a lower proximal trim line than IC sockets, and are often used with vacuum-assisted suspension
  • Quadrilateral (quad) sockets
    • These were historically the most common type, but are less common now, although still used for some patients
  • Direct socket
    • A novel method of fabricating a laminated interface directly onto the residual limb

Keys for transfemoral socket trim lines

  • In a transfemoral socket, the posterior and medial walls are lower than the anterior and lateral walls
  • This allows room for the groin and sacrum

Prosthetic gait deviations

Prosthetic gait deviations refer to any variations from a normal walking pattern that occur in individuals using prosthetic limbs, often due to compensatory strategies or issues with the prosthesis itself.

Vaulting

  • Definition: An attempt to lengthen the stance phase on the intact limb by knee extension and ankle plantar flexion during mid-stance
  • Causes:
    • Limb too long
    • Poorly suspended prosthesis
    • Excessive plantarflexion

Circumduction

  • Definition: The prosthetic limb travels in a lateral arch during swing.
  • Causes:
    • Excessive abduction of the prosthesis
    • Prosthesis too long
    • Inadequate suspension
    • Excessive plantarflexion of the prosthetic foot
    • Excessive knee friction or a locked knee unit

Abducted gait pattern

  • Definition: The prosthetic limb is carried in an abducted position throughout the swing and stance phase
  • Causes:
    • Outset prosthetic foot
    • Prosthesis too long
    • Medially placed intact foot

Knee instability

  • Definition: Excessive knee flexion on the prosthetic side in early stance
  • Causes:
    • Excessive foot dorsiflexion
    • Excessive socket flexion
    • Posterior translation of foot/pylon
    • Excessively hard heel cushion on prosthetic heel
    • Weakness of the knee extensors

Reduced toe clearance

  • Definition: Prosthetic toe drags or catches during the swing phase
  • Causes:
    • Prosthetic limb too long
    • Inadequate suspension
    • Residual limb not getting into prosthetic socket all the way
    • Excessive plantarflexion of the prosthetic foot

Pelvic drop

  • Definition: The pelvis on the prosthetic side drops on initial contact as if “stepping into a hole.”
  • Causes:
    • Prosthetic limb too short
    • Residual limb has shrunk relative to the socket
    • Excessively compliant heel cushion

Lateral trunk lean over prosthesis (Trendelenburg)

  • Definition: Trunk bends laterally over the prosthesis (compensated Trendelenburg) during stance
  • Causes:
    • Inadequate adduction of the socket
    • Prosthesis too short
    • Outset foot
    • Medial wall too high, causing pain
    • Gapping at the lateral wall of the socket

Medial/lateral whip

  • Definition: Abrupt medial or lateral movement of the prosthetic heel during swing
  • Causes:
    • Excessive external or internal rotation of the socket
    • Socket too tight
    • Inadequate suspension
    • Excessive valgus of prosthetic knee

Increased knee flexion

  • Definition: Long prosthetic step (decreased stance time on prosthesis)
  • Causes:
    • Painful socket - residual limb; painful
    • Prosthesis too long
    • Excessive foot dorsiflexion
    • Excessively hard heel cushion on prosthetic heel
Key points

Levels of amputations - Upper extremity

  • Progression: finger/partial hand → wrist disarticulation → transradial (below elbow) → elbow disarticulation → transhumeral (above elbow) → shoulder disarticulation

Levels of amputations - Lower extremity

  • Progression: toe/partial foot → ankle disarticulation (Syme’s) → transtibial (below knee) → knee disarticulation → transfemoral (above knee) → hip disarticulation
  • Syme’s amputation preserves heel pad for end-weight bearing
  • NPTE focuses primarily on lower extremity prosthetics

Primary components of prosthesis

  • Socket: custom-molded, total contact, equal tissue load distribution
  • Liner: silicone barrier reducing shear forces
  • Sock: adjusts residual limb size/fit
  • Terminal device: hand/hook (upper limb) or foot (lower limb)

Transtibial prosthesis - Ankle-foot assembly

  • SACH foot: solid ankle, simple/durable/lightweight
  • Single-axis foot: hinged ankle, up-down movement, enhances knee stability
  • Multi-axis foot: adds side-to-side movement, good for uneven terrain
  • Microprocessor-controlled (MPC) feet: sensors adjust ankle position/resistance dynamically

Transtibial prosthesis - Shank

  • Endoskeletal: tubular structure, cosmetic foam cover, adjustable/lighter, less durable
  • Exoskeletal: hard outer shell, wood/plastic, more durable, less customizable, good for labor/harsh environments

Transtibial prosthesis - Socket

  • PTB (patellar tendon bearing): loads pressure-tolerant areas (patellar tendon, medial tibial flare); good for short/bony limbs, easier don/doff; not ideal with scar tissue/skin breakdown
  • TSB (total surface bearing): even weight distribution, used with gel liners; better for scar tissue/sensitive skin; better suspension (pins/suction); harder to don/doff

Transfemoral prosthesis - Knee unit

  • Single-axis knee: simple hinge, stable in stance, more effort in swing; suited for lower activity levels
    • Manual locking: locks in extension, manually unlocked for sitting
    • Constant friction: constant swing-phase resistance
  • Polycentric (multiaxis) knee: multiple pivot points, natural gait, shortens during swing (reduces tripping); suited for active users/longer limbs
    • Hydraulic/pneumatic: fluid/air control for smoother swing
  • Microprocessor knee: sensor-based adjustment, improves stability/reduces energy cost; best for highly active users

Transfemoral prosthesis - Socket

  • Ischial containment (IC): narrow M-L dimension, ischium encapsulated in socket
  • Sub-ischial: lower proximal trim line, often vacuum-assisted suspension
  • Quadrilateral (quad): historically common, now less used
  • Direct socket: laminated interface fabricated directly on residual limb

Transfemoral socket trim lines

  • Posterior and medial walls lower than anterior/lateral walls
  • Allows room for groin and sacrum

Prosthetic gait deviations - overview

  • Deviations from normal gait due to prosthesis fit/alignment issues or compensatory strategies

Vaulting

  • Rising on intact limb (knee extension, ankle plantarflexion) to lengthen stance
  • Causes: limb too long, poor suspension, excessive plantarflexion

Circumduction

  • Prosthetic limb swings in lateral arc during swing phase
  • Causes: excessive abduction, limb too long, poor suspension, excessive plantarflexion, excessive knee friction/locked knee

Abducted gait pattern

  • Limb held abducted throughout gait cycle
  • Causes: outset prosthetic foot, limb too long, medially placed intact foot

Knee instability

  • Excessive knee flexion in early stance
  • Causes: excessive dorsiflexion, excessive socket flexion, posterior foot/pylon translation, hard heel cushion, weak knee extensors

Reduced toe clearance

  • Toe drags/catches during swing
  • Causes: limb too long, poor suspension, incomplete limb insertion into socket, excessive plantarflexion

Pelvic drop

  • Pelvis drops on prosthetic side at initial contact (“stepping into a hole”)
  • Causes: limb too short, residual limb shrinkage, overly compliant heel cushion

Lateral trunk lean (Trendelenburg)

  • Trunk leans laterally over prosthesis during stance
  • Causes: inadequate socket adduction, limb too short, outset foot, high medial wall (pain), lateral wall gapping

Medial/lateral whip

  • Abrupt heel movement during swing
  • Causes: excessive socket rotation (internal/external), tight socket, poor suspension, excessive knee valgus

Increased knee flexion

  • Long prosthetic step, decreased stance time on prosthesis
  • Causes: painful socket/residual limb, limb too long, excessive dorsiflexion, hard heel cushion

More from Musculoskeletal system

  • Anatomy of musculoskeletal system
  • Anatomical terminology and exercise training principles
  • Joint mechanics and phases of healing
  • Upper extremity anatomy
  • Lower extremity anatomy