



Peripheral disorders and intervention strategies
Differential diagnosis of peripheral vestibular dysfunction with intervention strategies
Benign paroxysmal positional vertigo (BPPV)
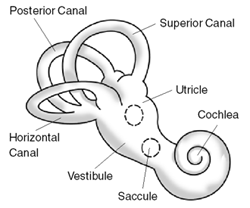
An endolymph disorder causing brief, intense vertigo due to a change in head position - the otoconia within the semicircular canals become dislodged.
Confirmation of BPPV
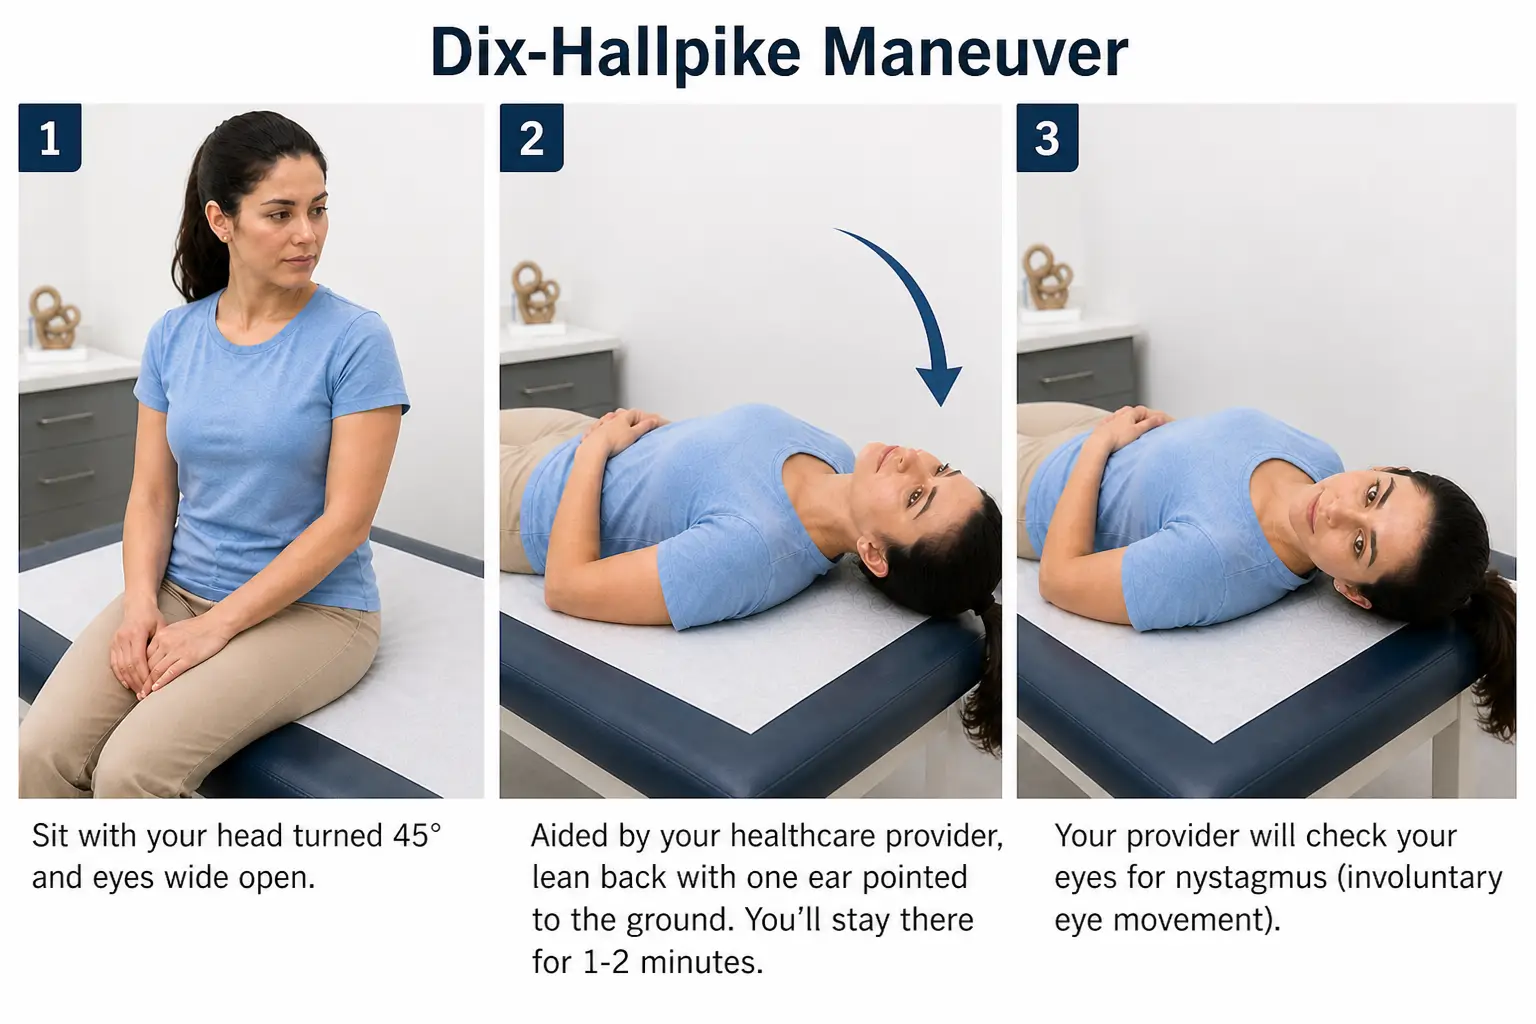
- Confirmed by performing the Dix-Hallpike test - before completing the test, the therapist must perform a vertebral artery test and ensure appropriate cervical range of motion is present
- Patient positioned in long sitting, with the head turned 45 degrees toward the affected side
- Patient is quickly lowered to supine with the head remaining at 45 degrees and hanging over the edge of the mat, while the therapist observes for nystagmus
- Nystagmus will resolve within 30-60 seconds
- A positive test occurs when the patient experiences nystagmus and vertigo with a head position change
- Repeat the test on the contralateral side
Understanding what nystagmus means in relation to BPPV
- Ageotropic (apogeotropic)
- Fast beating phase of the nystagmus is moving away from the ground (towards the upper ear) - this indicates lateral canal BPPV
- Geotropic
- Fast beating phase of nystagmus is moving towards the ground (towards the lower ear) - this also indicates lateral canal BPPV
- Torsional (rotary), upbeating
- Indicates posterior canal BPPV
Differentiation of BPPV and canals impacted
Lateral canal BPPV
- Can manifest as ageotropic or geotropic horizontal nystagmus
- Treatment is with the log roll maneuver or barbeque roll maneuver to move the otoconia into position (performed as a home exercise program)
- Log roll maneuver: the patient rolls sequentially from supine through a head turn toward the affected ear, a head turn away from the affected ear, and a prone position, ending back in supine toward the affected side, guiding the otoconia out of the lateral canal.
- Barbeque roll maneuver: the patient rolls in 90-degree increments from side-lying on the affected side, through supine, to side-lying on the unaffected side, to prone, pausing at each position, and finishes by returning slowly to sitting.
Posterior canal BPPV (most common BPPV)
- Typically presents with torsional (rotary), upbeating nystagmus
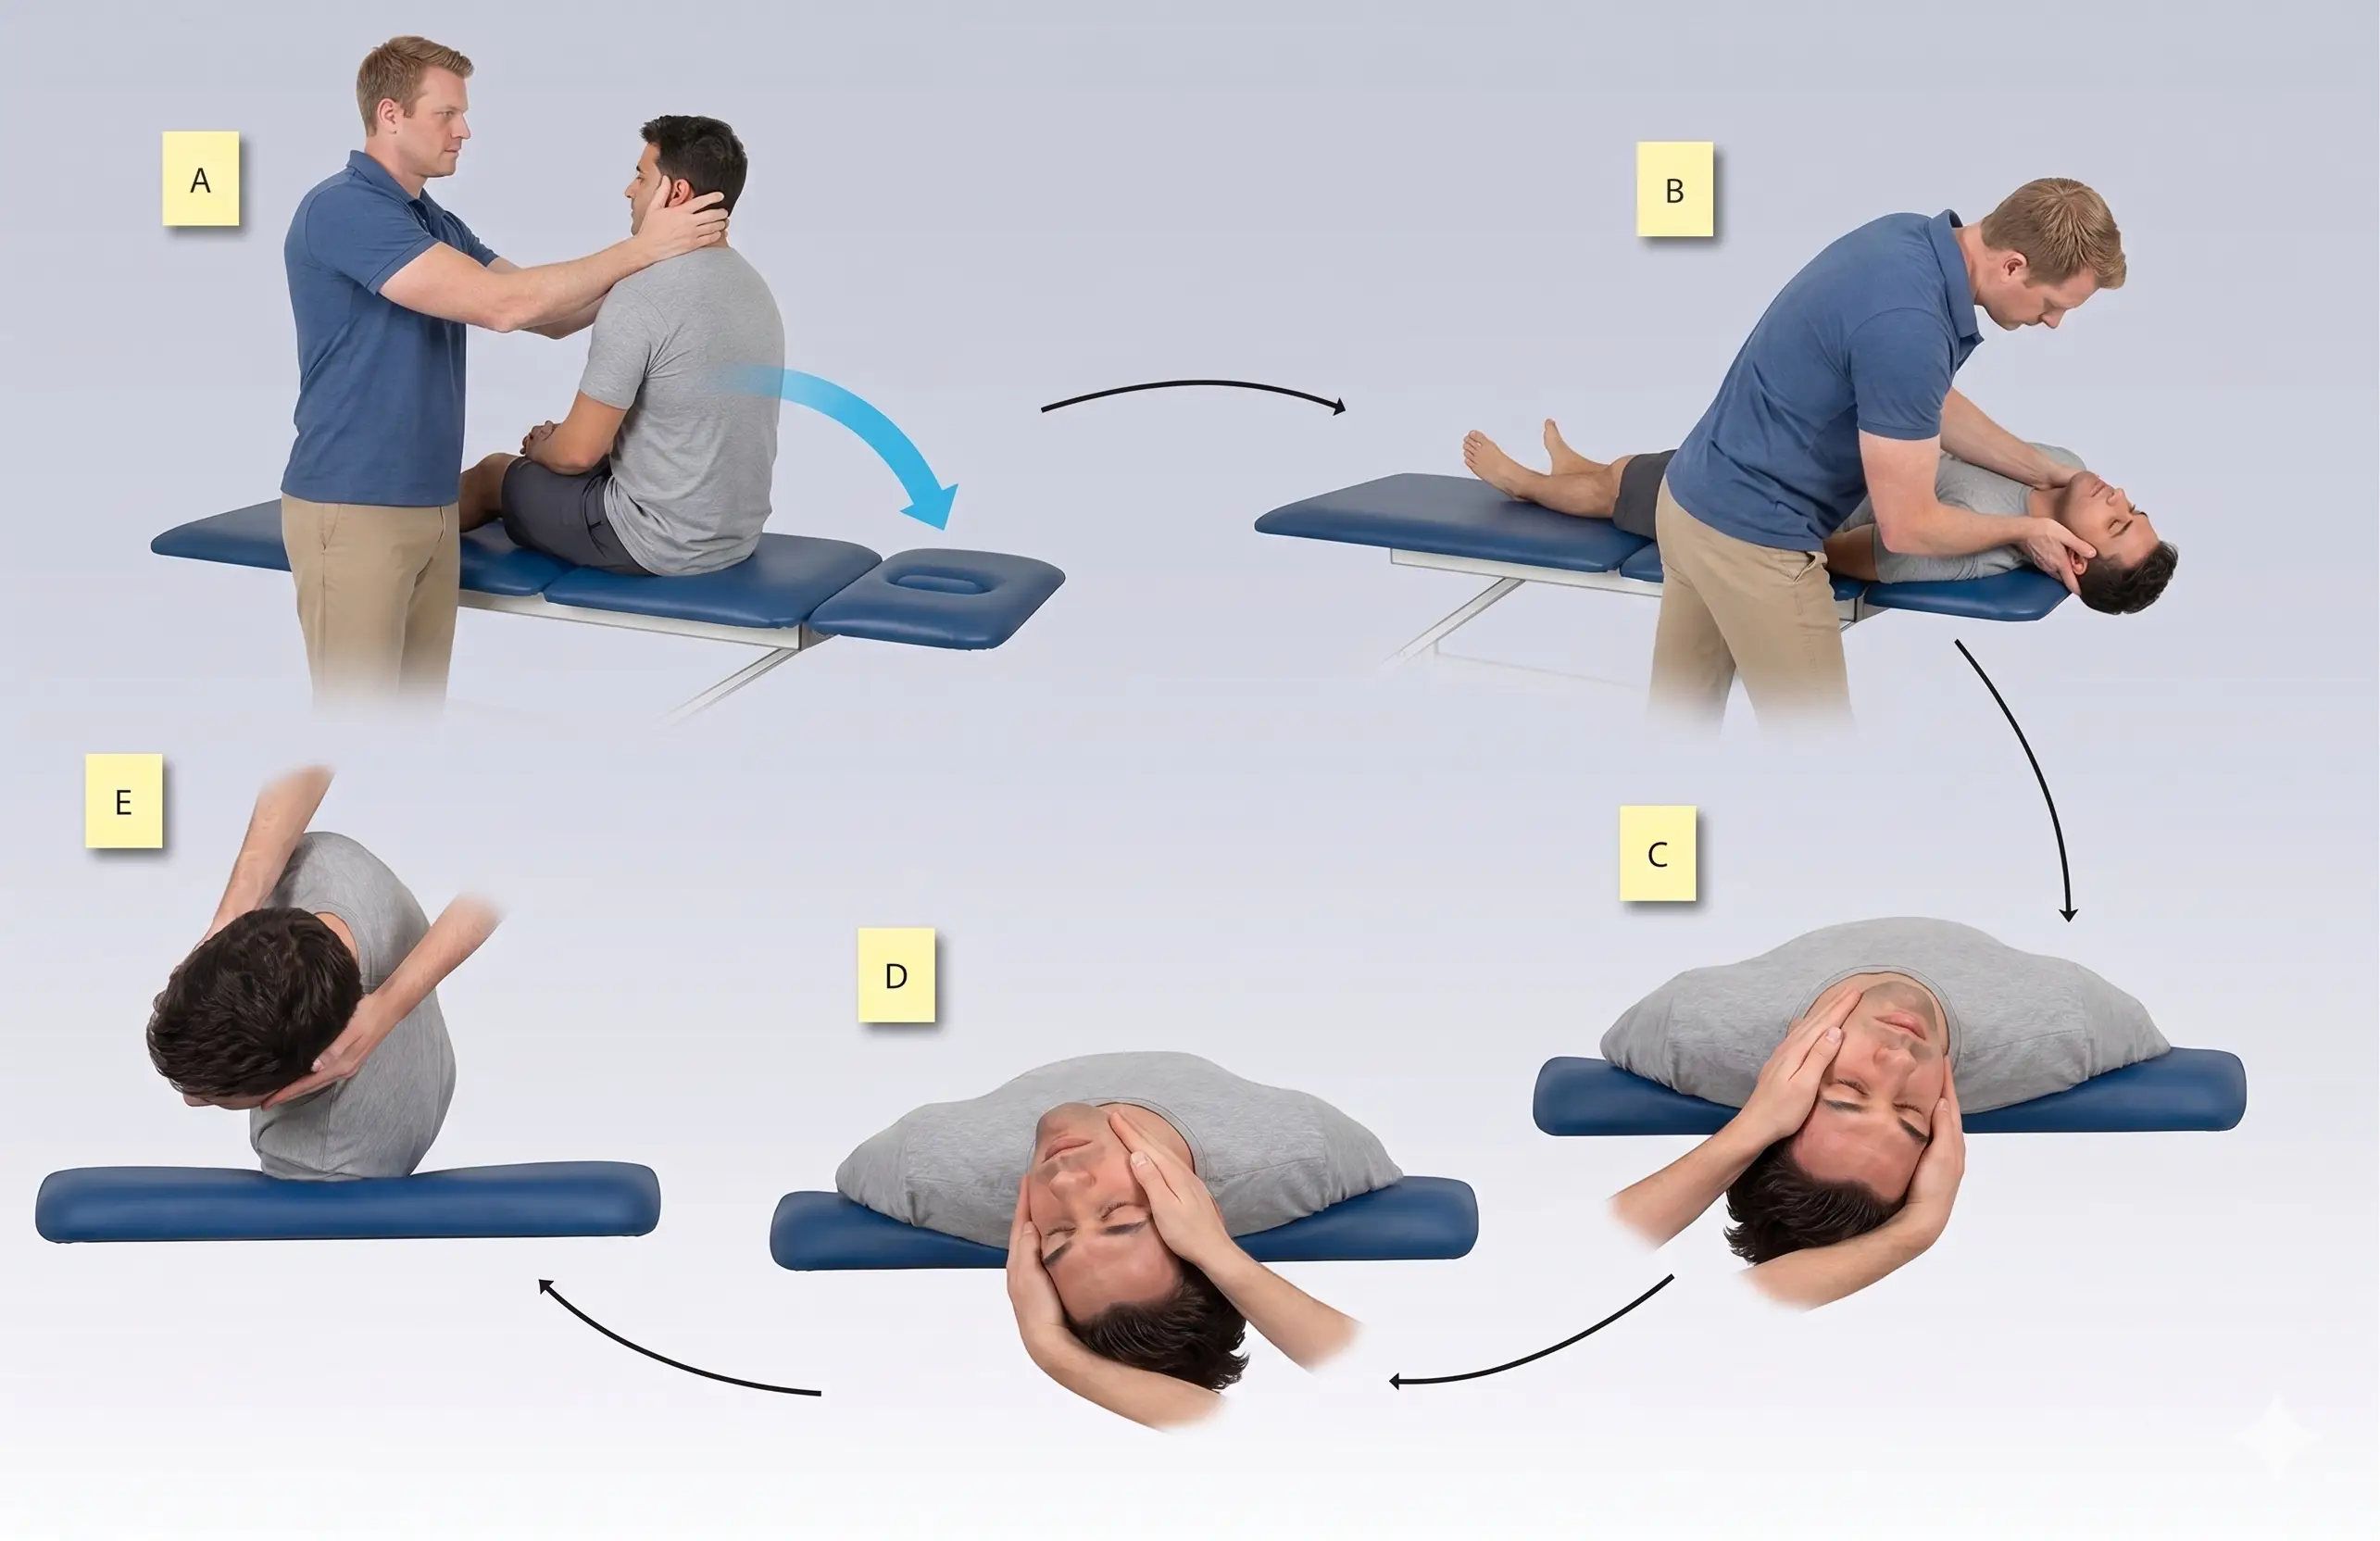
- The Epley maneuver is performed to reposition the otoconia: the patient moves from sitting to supine with the head turned toward the affected side, then rotates the head and body through a series of positions to guide the otoconia out of the posterior canal, finishing in sitting.
Anterior canal BPPV (least common BPPV)
- Typically presents with vertical downbeat nystagmus
- The Yacovino maneuver is performed to reposition the otoconia: the patient moves from sitting to supine with the head extended below horizontal, then to a chin-to-chest position, and back to sitting, guiding the otoconia out of the anterior canal.
Meniere’s disease
Episodes of vertigo can last from minutes to days. Due to the chronicity of the disease, management focuses on reducing the frequency of attacks and managing symptoms.
Management of symptoms
- Low sodium diet - reduces fluid levels
- Regular exercise - improves balance and reduces stress
- Management of stress - stress can exacerbate an episode of vertigo
- Diuretics - reduce fluid within the ear
- Surgery - drains excess fluid or removes the damaged portion of the inner ear
Physical therapy management of individuals with Meniere’s disease is symptom-based, and episodes of care are short. The focus will primarily be to assist with any balance deficits or muscle weakness, provide an individualized home exercise program, and reinforce patient education.
Vestibular neuritis
Symptoms include sudden onset of severe vertigo (spinning sensation), nausea and vomiting, dizziness and lightheadedness, difficulty walking, and nystagmus. Symptoms are typically sudden and improve with medical intervention over a few days.
Treatment options
- Antibiotics for the management of infection
- Corticosteroid medication for the management of inflammation
- Anti-nausea medication for persistent nausea and vomiting
Acute vertigo typically subsides within days, but vestibular rehabilitation (gaze stabilization, habituation, and balance training) is recommended to address the lingering imbalance and dizziness from unilateral vestibular hypofunction. If any balance or coordination deficits continue, then physical therapy interventions will be prescribed at that time.
Labyrinthitis
Symptoms include vertigo, nausea and vomiting, balance problems, hearing loss, tinnitus (ringing in the ears), and ear pain. Most symptoms resolve within a few weeks, but some permanent hearing loss may be present.
Treatment interventions
- Antihistamines - for treatment of vertigo symptoms
- Anti-nausea drugs - for treatment of nausea and vomiting
- Corticosteroids - for treatment of inflammation
- Antibiotics - for treatment of infection