


Achievable logoAchievable logo
NCLEX
Sign in
Sign up
Purchase
Textbook
Practice exams
Support
How it works
Resources
Exam catalog
Mountain with a flag at the peak
Textbook
Introduction
1. Safe and effective care environment
1.1 Management of care
1.2 Safety and infection prevention and control
1.2.1 Standard precautions and transmission-based precautions
1.2.2 Surgical asepsis and sterile technique
1.2.3 Use of safety devices
1.2.4 Hazardous materials and emergency response
1.2.5 Incident reporting and error prevention
1.2.6 Safe handling of equipment and radiation precautions
1.2.7 Isolation and infection prevention
2. Health promotion and maintenance
3. Psychosocial Integrity
4. Physiological Integrity
Wrapping up
Achievable logoAchievable logo
1.2.1 Standard precautions and transmission-based precautions
Achievable NCLEX
1. Safe and effective care environment
1.2. Safety and infection prevention and control
Our NCLEX course is currently in development and is a work-in-progress.

Standard precautions and transmission-based precautions

8 min read
Font
Discuss
Share
Feedback

Introduction

Infection prevention begins with one truth; every client, every fluid, every surface could carry risk. That mindset defines standard precautions, the foundation of all nursing safety. When known or suspected pathogens enter the picture, transmission-based precautions add extra layers of protection. Together, these form the shield between healthcare providers and preventable infection.

Learning objectives

By the end of this section, you should be able to:

  • differentiate between standard and transmission-based precautions
  • identify correct PPE for airborne, droplet, and contact precautions
  • apply safe transport, cleaning, and client-education practices

Precaution classifications

There are two main classifications for precautions. Within these, standard precautions form the universal defense in healthcare, applying to all clients, while transmission-based precautions add specific protective measures when known or suspected pathogens are present, targeting their routes of spread.

Precaution type When it applies
Standard precautions Used for every client, regardless of diagnosis
Airborne precautions For pathogens that remain suspended in the air
Droplet precautions For pathogens spread by large respiratory droplets
Contact precautions For pathogens spread by direct contact or contaminated surfaces
Protective (reverse) isolation For severely immunocompromised clients who need protection from outside pathogens

Key PPE and measures

Standard precautions are the baseline applied to every client, every time. The transmission-based categories layer additional PPE on top of that baseline when a specific route of spread is known or suspected.

  • Standard precautions (always applied): Hand hygiene; gloves when touching blood, body fluids, or contaminated items; mask, eye protection, or gown as indicated

On top of standard precautions, add the route-specific measures:

  • Airborne precautions: N95 respirator; negative-pressure room; limit transport if possible
  • Droplet precautions: Surgical mask for close contact; private room if possible; mask client during transport
  • Contact precautions: Gloves and gown; dedicated equipment when possible; hand hygiene
  • Protective (reverse) isolation: Private/protective environment; strict hand hygiene; PPE as indicated to protect the client

Standard precautions

Standard precautions apply to every client, regardless of diagnosis or perceived infection status.

  • Perform hand hygiene before and after contact with each client
  • Use gloves, gowns, masks, and eye protection when risk of exposure exists
  • Follow respiratory hygiene/cough etiquette
  • Practice safe injection and needle disposal
  • Assume all body fluids (except sweat) are potentially infectious

Clinical vignette: A nurse changes a dressing on a post-op wound. Gloves are required because contact with blood is possible, even if the client has no history of infection. Gloves protect both the client and the nurse.

Transmission-based precautions

When a client has or is suspected of having an infection spread by a specific route, nurses must apply additional protective measures beyond standard precautions. These precautions (airborne, droplet, and contact) target the exact way pathogens travel to prevent transmission.

Airborne precautions: Used for infections that spread through fine particles (<5 microns) that remain suspended in the air for long periods. These pathogens can travel across distances, so clients require a negative-pressure room, and staff must wear an N95 respirator or higher-level protection.

(spoiler)

Examples: Tuberculosis (TB), measles (rubeola), and varicella (chickenpox).

Note: varicella (and disseminated herpes zoster) requires airborne and contact precautions together, maintained until all lesions are dry and crusted, per CDC.

Droplet precautions: Applied when pathogens are spread through respiratory droplets (>5 microns) expelled during coughing, sneezing, or talking. Because droplets fall within about 3 feet, nurses must wear a surgical mask within close proximity and ensure the client wears a mask when transported.

(spoiler)

Examples: Influenza, pertussis, meningococcal meningitis, mumps, and rubella.

Contact precautions: For infections spread by direct touch or contact with contaminated surfaces. Nurses wear gloves and a gown upon room entry and during contact with the client or the client’s environment. Use soap and water hand hygiene, particularly for spore-forming organisms such as C. difficile, because alcohol-based hand sanitizers are less effective against spores.

(spoiler)

Examples: MRSA, VRE, RSV, C. difficile, scabies, draining wounds.

Protective (reverse) isolation: Protective precautions safeguard immunocompromised clients from external pathogens. These clients require a positive-pressure room, meticulous hand hygiene, and restrictions on fresh flowers, raw foods, or sick visitors.

(spoiler)

Examples: Neutropenia, post-transplant or chemotherapy clients.

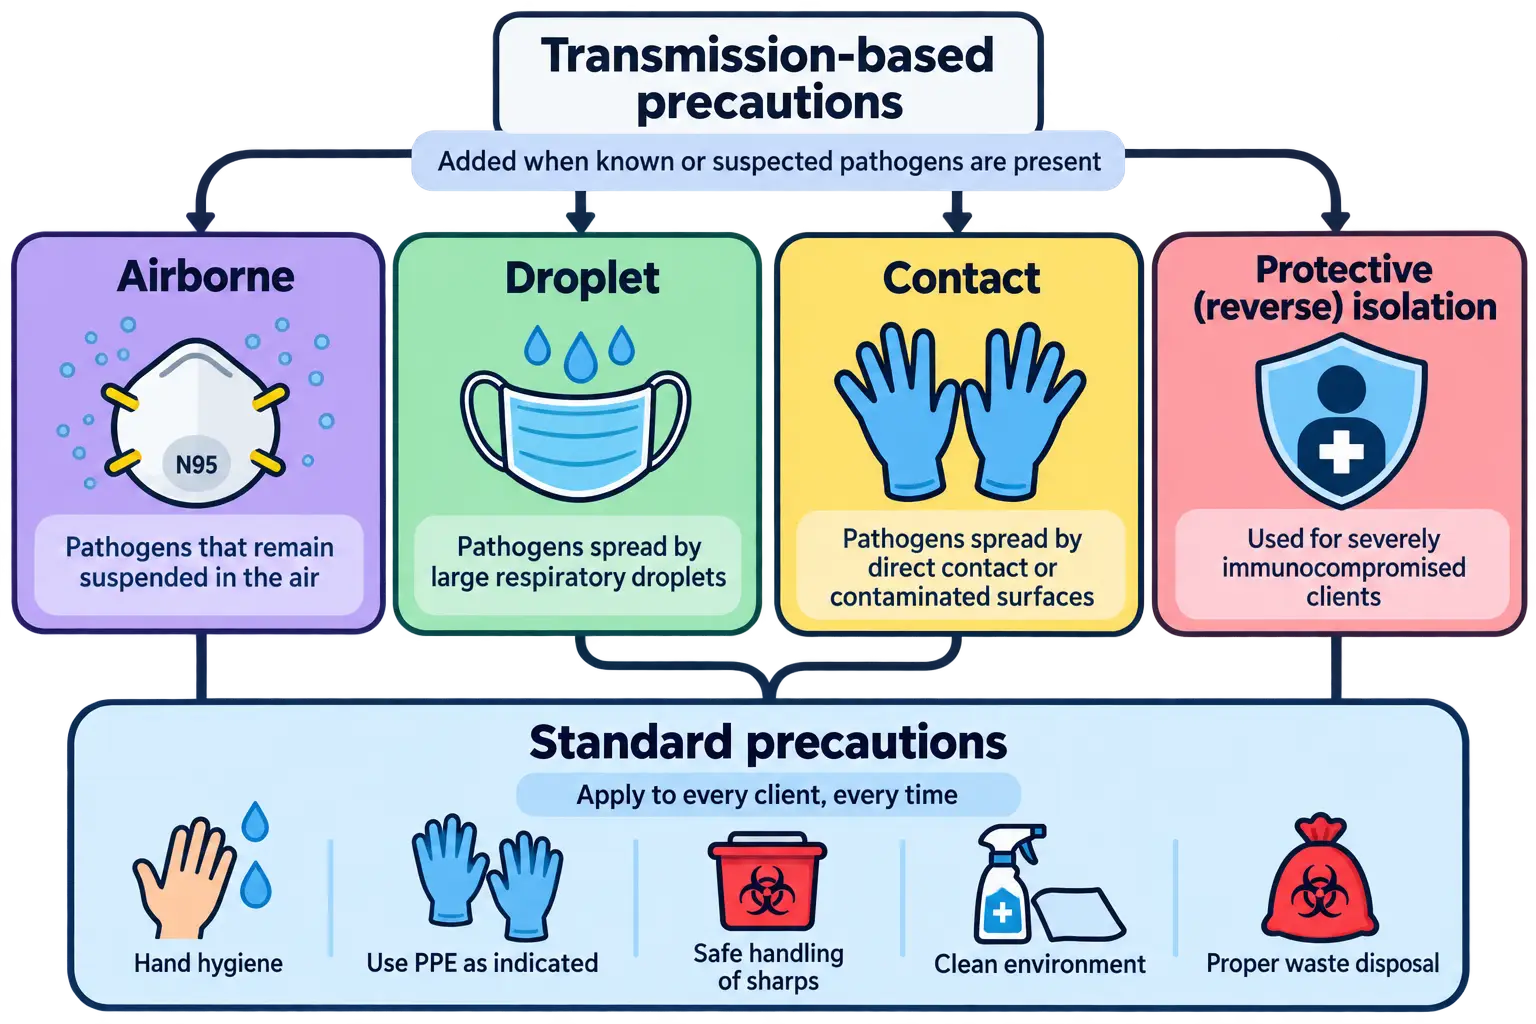
Transmission-based precautions are added when known or suspected pathogens are present, comprising four categories: Airborne (pathogens suspended in air, N95 mask), Droplet (large respiratory droplets, surgical mask), Contact (direct contact or contaminated surfaces, gloves), and Protective reverse isolation (for severely immunocompromised clients, shield icon). All four connect down to Standard precautions, which apply to every client every time: hand hygiene, using PPE as indicated, safe handling of sharps, cleaning the environment, and proper waste disposal.
Transmission-based precautions
Achievable

NGN tip: Remember! Standard precautions are always used. Transmission-based precautions are added when indicated.

Definitions
Negative-pressure room
Air flows into the client’s room but not out, preventing airborne pathogens from escaping into hallways. Used for infections like tuberculosis, measles, and varicella. (think sucking in air)
Positive-pressure room
Air flows out of the client’s room but not in, protecting immunocompromised clients from outside contaminants. Used for neutropenic, transplant, and chemotherapy clients. (think blowing out air)
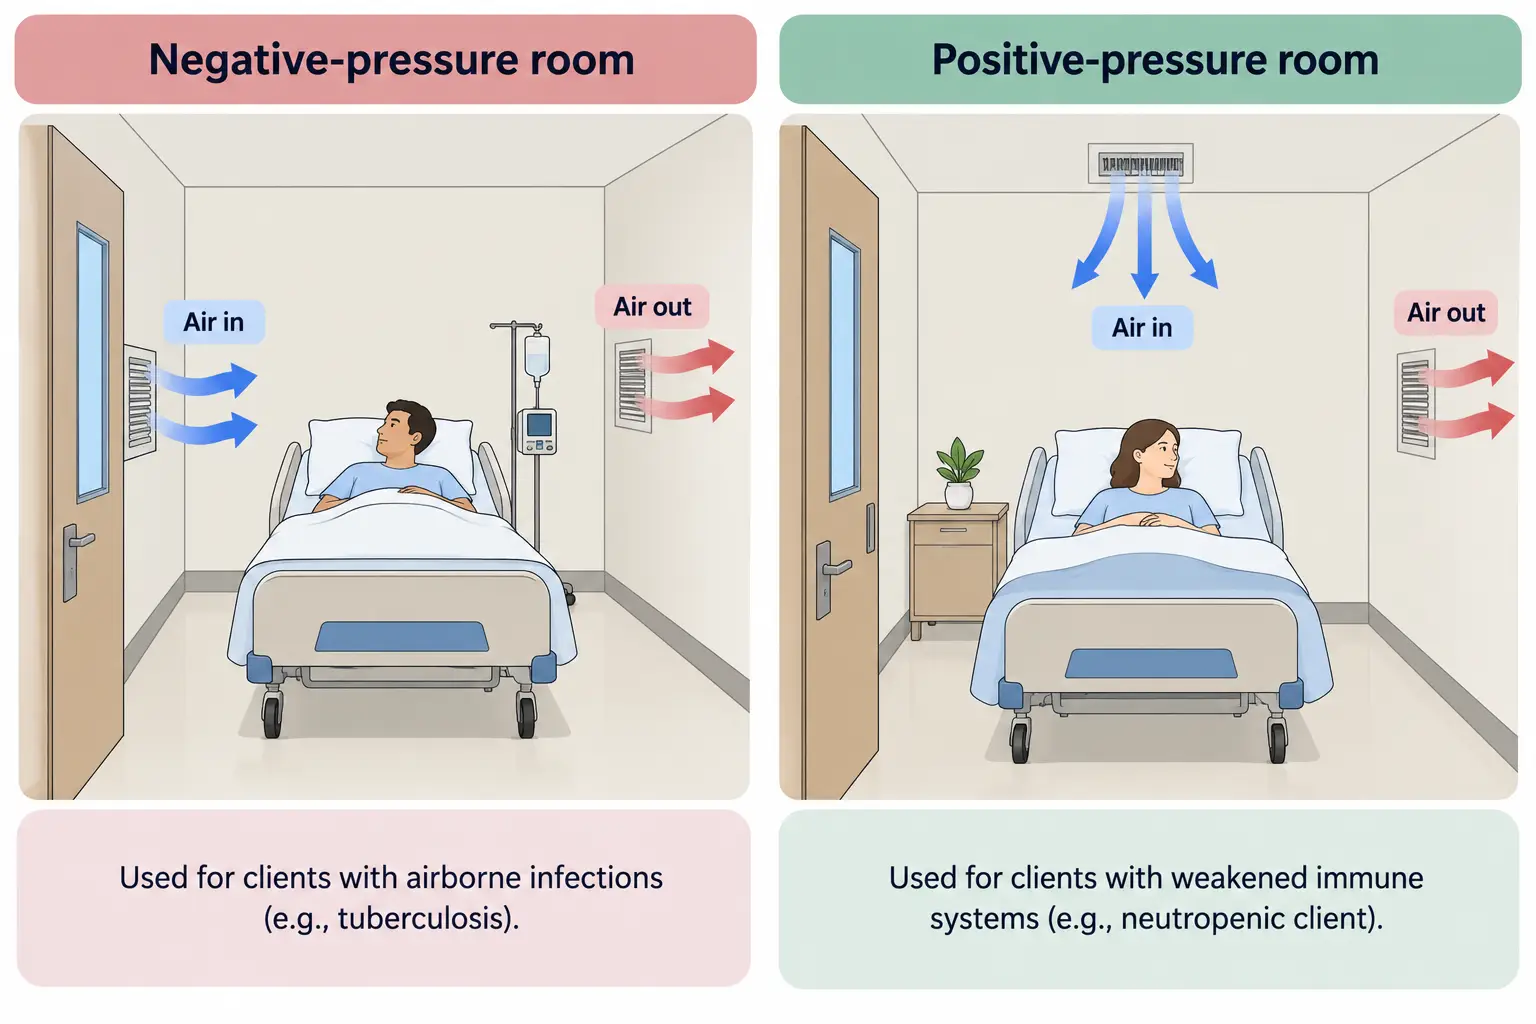
In a negative-pressure room, air flows in through the door vent and out through a wall vent, containing airborne infections like tuberculosis. In a positive-pressure room, filtered air flows in from the ceiling and out through a wall vent, protecting immunocompromised clients, such as neutropenic clients.
Negative-pressure versus positive-pressure rooms
Achievable

Nursing interventions

  • Hand hygiene: Use alcohol-based rubs unless caring for C. difficile (requires soap & water)

  • PPE sequence:

    • Don: Gown → mask/respirator → goggles/face shield → gloves
    • Doff: Gloves → goggles/face shield → gown → mask/respirator
  • Client transport: Limit movement; mask airborne/droplet clients; cover wounds for contact isolation

  • Equipment: Dedicate or disinfect shared items between clients

  • Environmental cleaning: High-touch surfaces and bathrooms need frequent disinfection

  • Specimen handling: Label accurately and place in biohazard bags

NGN tip:

  • Remove gloves first. They’re the dirtiest. Perform hand hygiene between steps if contamination occurs.
  • Remove mask/respirator last outside if applicable.
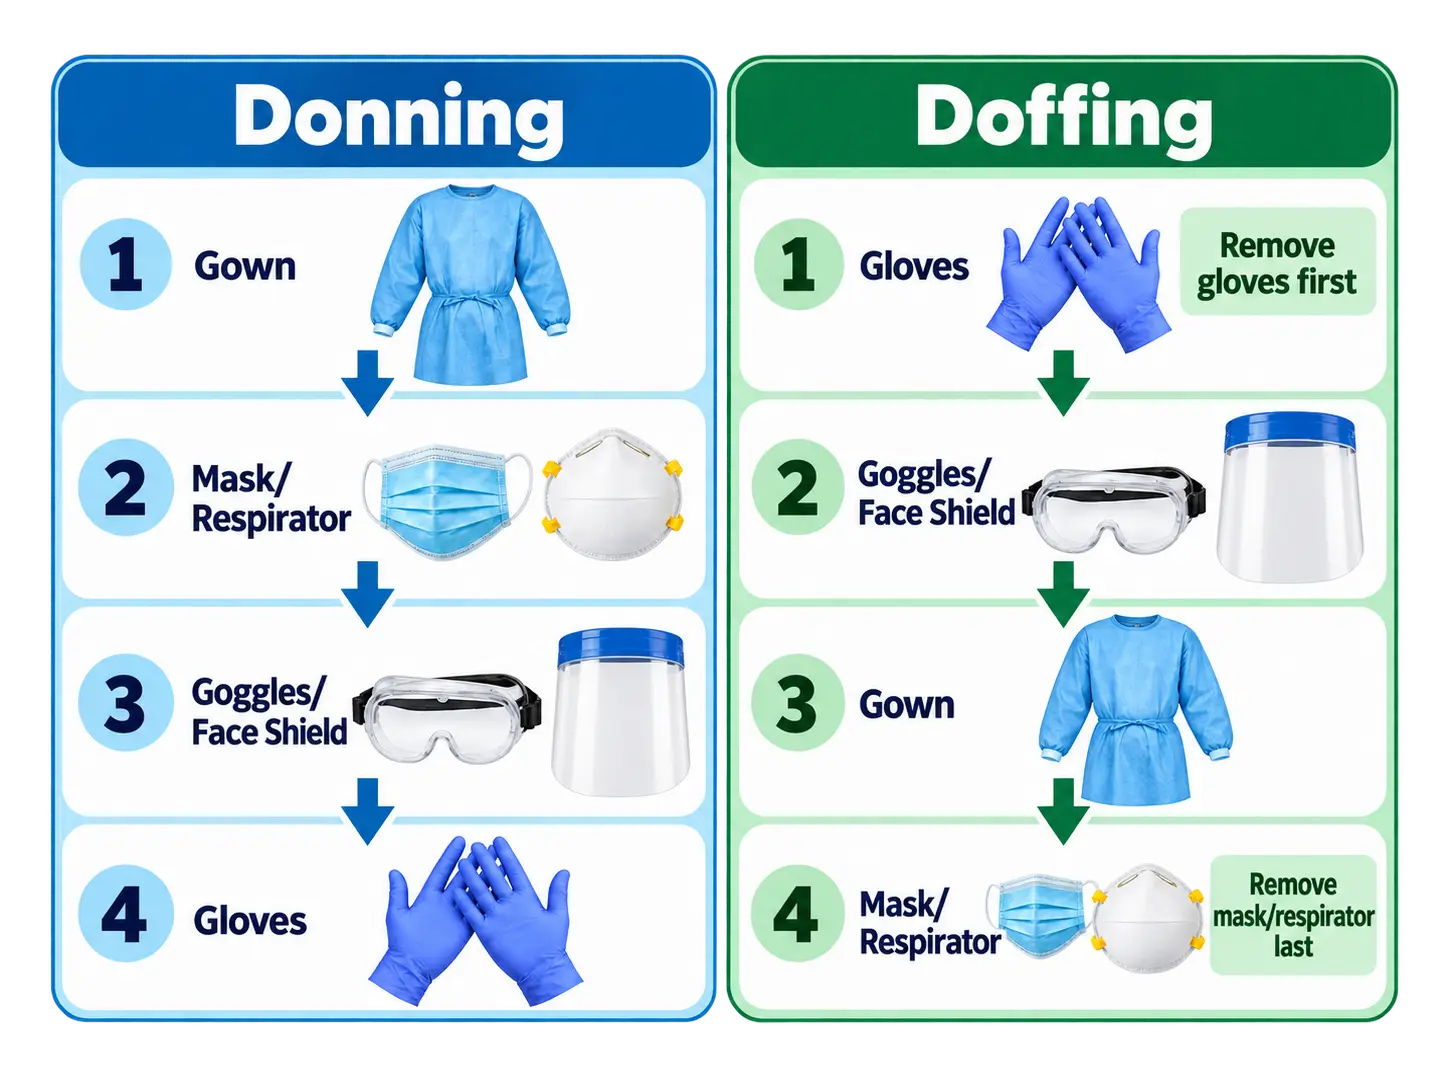
PPE donning order: 1 gown, 2 mask/respirator, 3 goggles/face shield, 4 gloves. PPE doffing order (reverse): 1 gloves (remove gloves first), 2 goggles/face shield, 3 gown, 4 mask/respirator (remove mask/respirator last).
Correct PPE donning and doffing sequence
Achievable

Clinical vignette: A client with MRSA is moved to radiology. The nurse covers draining wounds, notifies receiving staff, and ensures surfaces are disinfected afterward.

Client and family education

  • Explain the reason for isolation calmly; emphasize protection, not punishment
  • Teach proper handwashing and PPE use before entering/leaving the room
  • Encourage compliance to reduce cross-contamination anxiety

Common pitfalls:

  • Using alcohol-based hand rub instead of soap and water during norovirus outbreaks - alcohol-based rubs are less effective against non-enveloped viruses.
  • Assuming standard precautions aren’t needed for “clean”-looking clients.
  • Blurring the two precaution types: standard precautions apply to every client regardless of diagnosis, while transmission-based precautions are added on top only when a specific route of spread is known or suspected.
  • Transporting infected clients without notifying receiving departments.

Standard and transmission-based precautions cover most client contact, but invasive procedures call for an even stricter barrier - sterile technique, covered next in Surgical asepsis and sterile technique.

  • Standard precautions = universal defense for all patient contact.
  • Transmission-based precautions are additional barriers based on the infection route.
  • Airborne: N95 + negative pressure; Droplet: surgical mask; Contact: gloves + gown.
  • Soap and water for spores (C. diff, norovirus).
  • Remove PPE before leaving the patient area; perform hand hygiene immediately after.
  • Educate patients and families—isolation is safety, not stigma.

Sign up for free to take 9 quiz questions on this topic

Previous
Next  | 1.2.2 Surgical asepsis and sterile technique
All rights reserved ©2016 - 2026 Achievable, Inc.

Standard precautions and transmission-based precautions

Introduction

Infection prevention begins with one truth; every client, every fluid, every surface could carry risk. That mindset defines standard precautions, the foundation of all nursing safety. When known or suspected pathogens enter the picture, transmission-based precautions add extra layers of protection. Together, these form the shield between healthcare providers and preventable infection.

Learning objectives

By the end of this section, you should be able to:

  • differentiate between standard and transmission-based precautions
  • identify correct PPE for airborne, droplet, and contact precautions
  • apply safe transport, cleaning, and client-education practices

Precaution classifications

There are two main classifications for precautions. Within these, standard precautions form the universal defense in healthcare, applying to all clients, while transmission-based precautions add specific protective measures when known or suspected pathogens are present, targeting their routes of spread.

Precaution type When it applies
Standard precautions Used for every client, regardless of diagnosis
Airborne precautions For pathogens that remain suspended in the air
Droplet precautions For pathogens spread by large respiratory droplets
Contact precautions For pathogens spread by direct contact or contaminated surfaces
Protective (reverse) isolation For severely immunocompromised clients who need protection from outside pathogens

Key PPE and measures

Standard precautions are the baseline applied to every client, every time. The transmission-based categories layer additional PPE on top of that baseline when a specific route of spread is known or suspected.

  • Standard precautions (always applied): Hand hygiene; gloves when touching blood, body fluids, or contaminated items; mask, eye protection, or gown as indicated

On top of standard precautions, add the route-specific measures:

  • Airborne precautions: N95 respirator; negative-pressure room; limit transport if possible
  • Droplet precautions: Surgical mask for close contact; private room if possible; mask client during transport
  • Contact precautions: Gloves and gown; dedicated equipment when possible; hand hygiene
  • Protective (reverse) isolation: Private/protective environment; strict hand hygiene; PPE as indicated to protect the client

Standard precautions

Standard precautions apply to every client, regardless of diagnosis or perceived infection status.

  • Perform hand hygiene before and after contact with each client
  • Use gloves, gowns, masks, and eye protection when risk of exposure exists
  • Follow respiratory hygiene/cough etiquette
  • Practice safe injection and needle disposal
  • Assume all body fluids (except sweat) are potentially infectious

Clinical vignette: A nurse changes a dressing on a post-op wound. Gloves are required because contact with blood is possible, even if the client has no history of infection. Gloves protect both the client and the nurse.

Transmission-based precautions

When a client has or is suspected of having an infection spread by a specific route, nurses must apply additional protective measures beyond standard precautions. These precautions (airborne, droplet, and contact) target the exact way pathogens travel to prevent transmission.

Airborne precautions: Used for infections that spread through fine particles (<5 microns) that remain suspended in the air for long periods. These pathogens can travel across distances, so clients require a negative-pressure room, and staff must wear an N95 respirator or higher-level protection.

(spoiler)

Examples: Tuberculosis (TB), measles (rubeola), and varicella (chickenpox).

Note: varicella (and disseminated herpes zoster) requires airborne and contact precautions together, maintained until all lesions are dry and crusted, per CDC.

Droplet precautions: Applied when pathogens are spread through respiratory droplets (>5 microns) expelled during coughing, sneezing, or talking. Because droplets fall within about 3 feet, nurses must wear a surgical mask within close proximity and ensure the client wears a mask when transported.

(spoiler)

Examples: Influenza, pertussis, meningococcal meningitis, mumps, and rubella.

Contact precautions: For infections spread by direct touch or contact with contaminated surfaces. Nurses wear gloves and a gown upon room entry and during contact with the client or the client’s environment. Use soap and water hand hygiene, particularly for spore-forming organisms such as C. difficile, because alcohol-based hand sanitizers are less effective against spores.

(spoiler)

Examples: MRSA, VRE, RSV, C. difficile, scabies, draining wounds.

Protective (reverse) isolation: Protective precautions safeguard immunocompromised clients from external pathogens. These clients require a positive-pressure room, meticulous hand hygiene, and restrictions on fresh flowers, raw foods, or sick visitors.

(spoiler)

Examples: Neutropenia, post-transplant or chemotherapy clients.

NGN tip: Remember! Standard precautions are always used. Transmission-based precautions are added when indicated.

Definitions
Negative-pressure room
Air flows into the client’s room but not out, preventing airborne pathogens from escaping into hallways. Used for infections like tuberculosis, measles, and varicella. (think sucking in air)
Positive-pressure room
Air flows out of the client’s room but not in, protecting immunocompromised clients from outside contaminants. Used for neutropenic, transplant, and chemotherapy clients. (think blowing out air)

Nursing interventions

  • Hand hygiene: Use alcohol-based rubs unless caring for C. difficile (requires soap & water)

  • PPE sequence:

    • Don: Gown → mask/respirator → goggles/face shield → gloves
    • Doff: Gloves → goggles/face shield → gown → mask/respirator
  • Client transport: Limit movement; mask airborne/droplet clients; cover wounds for contact isolation

  • Equipment: Dedicate or disinfect shared items between clients

  • Environmental cleaning: High-touch surfaces and bathrooms need frequent disinfection

  • Specimen handling: Label accurately and place in biohazard bags

NGN tip:

  • Remove gloves first. They’re the dirtiest. Perform hand hygiene between steps if contamination occurs.
  • Remove mask/respirator last outside if applicable.

Clinical vignette: A client with MRSA is moved to radiology. The nurse covers draining wounds, notifies receiving staff, and ensures surfaces are disinfected afterward.

Client and family education

  • Explain the reason for isolation calmly; emphasize protection, not punishment
  • Teach proper handwashing and PPE use before entering/leaving the room
  • Encourage compliance to reduce cross-contamination anxiety

Common pitfalls:

  • Using alcohol-based hand rub instead of soap and water during norovirus outbreaks - alcohol-based rubs are less effective against non-enveloped viruses.
  • Assuming standard precautions aren’t needed for “clean”-looking clients.
  • Blurring the two precaution types: standard precautions apply to every client regardless of diagnosis, while transmission-based precautions are added on top only when a specific route of spread is known or suspected.
  • Transporting infected clients without notifying receiving departments.

Standard and transmission-based precautions cover most client contact, but invasive procedures call for an even stricter barrier - sterile technique, covered next in Surgical asepsis and sterile technique.

Key points
  • Standard precautions = universal defense for all patient contact.
  • Transmission-based precautions are additional barriers based on the infection route.
  • Airborne: N95 + negative pressure; Droplet: surgical mask; Contact: gloves + gown.
  • Soap and water for spores (C. diff, norovirus).
  • Remove PPE before leaving the patient area; perform hand hygiene immediately after.
  • Educate patients and families—isolation is safety, not stigma.

More from Safety and infection prevention and control

  • Surgical asepsis and sterile technique
  • Use of safety devices
  • Hazardous materials and emergency response
  • Incident reporting and error prevention
  • Safe handling of equipment and radiation precautions