



Endocrine and metabolic systems
Endocrine system
The endocrine system regulates metabolism, growth, and homeostasis through hormone secretion.
Thyroid disorders
The thyroid gland produces thyroxine (T4) and triiodothyronine (T3), regulating metabolism, heart rate, and temperature.
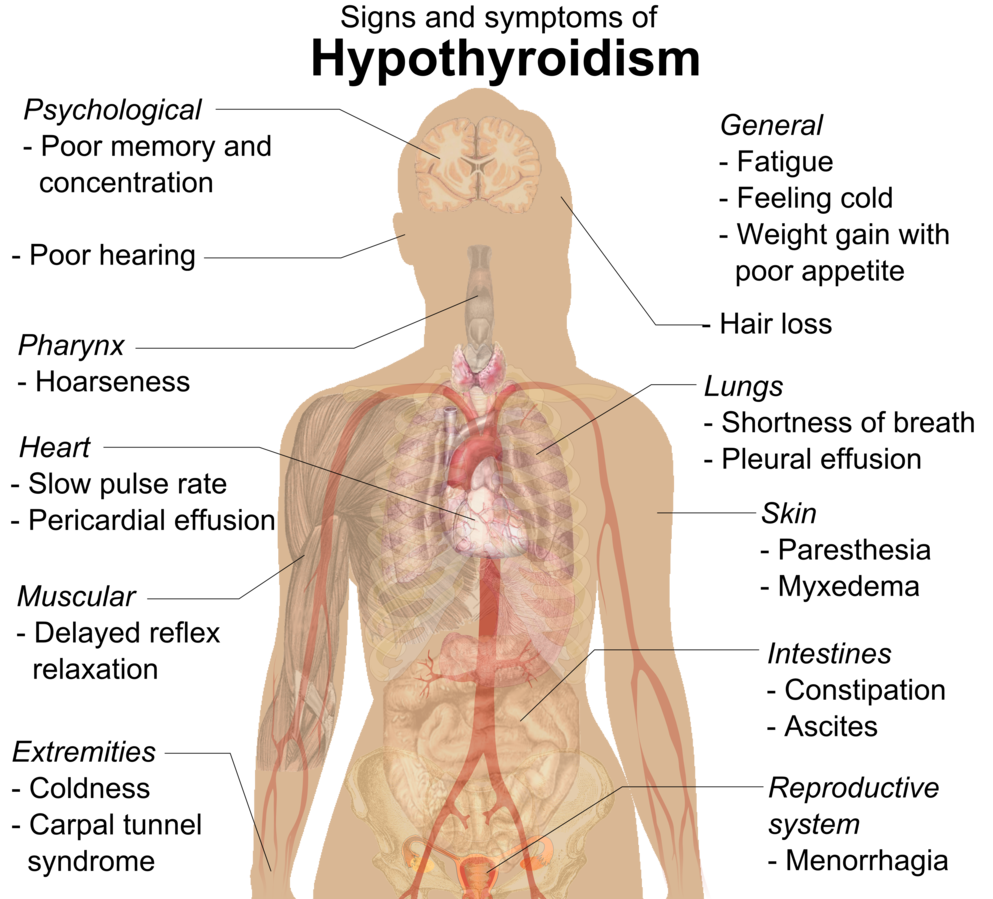
Hypothyroidism and hyperthyroidism present with opposite patterns:
| Hypothyroidism | Hyperthyroidism | |
|---|---|---|
| Weight | Weight gain | Weight loss |
| Temperature tolerance | Cold intolerance | Heat intolerance |
| Heart rate | Bradycardia | Tachycardia |
| Deep tendon reflexes | Slow (hyporeflexia) | Hyperreflexia |
| TSH | High | Low |
Hypothyroidism (underactive thyroid)
- Cause: Autoimmune disease (Hashimoto’s thyroiditis), iodine deficiency, post-thyroidectomy.
- Additional symptoms: Fatigue, constipation, depression, myopathy.
- PT implications:
- Monitor for exercise intolerance, muscle weakness, and risk of rhabdomyolysis.
- Low-intensity exercise with gradual progression.
- Watch for joint stiffness and slowed healing.
Hyperthyroidism (overactive thyroid)
- Cause: Autoimmune disease (Graves’ disease), excess iodine, thyroid tumors.
- In Graves’ disease, an antibody called thyroid-stimulating immunoglobulin attaches to thyroid cells and acts like TSH, making the thyroid produce too much thyroid hormone.
- Additional symptoms: Muscle wasting, tremors, exophthalmos (bulging eyes).
- PT implications:
- Monitor HR and BP due to risk of tachycardia, arrhythmias, and hypertension.
- Heat intolerance → adjust the exercise environment.
- Avoid high-intensity exercise due to risk of fatigue and catabolic muscle loss.
Thyroid storm (medical emergency)
- Acute hyperthyroidism crisis with severe tachycardia, fever, and confusion → requires emergency care.
Adrenal gland disorders
The adrenal glands (on top of the kidneys) produce cortisol, aldosterone, and catecholamines (epinephrine, norepinephrine). Cortisol, sometimes called the stress hormone, helps the body respond to stress and helps regulate blood glucose.
Addison’s disease and Cushing’s syndrome also present with opposite patterns:
| Addison’s disease | Cushing’s syndrome | |
|---|---|---|
| Blood pressure | Hypotension | Hypertension |
| Glucose | Risk of hypoglycemia | Risk of hyperglycemia |
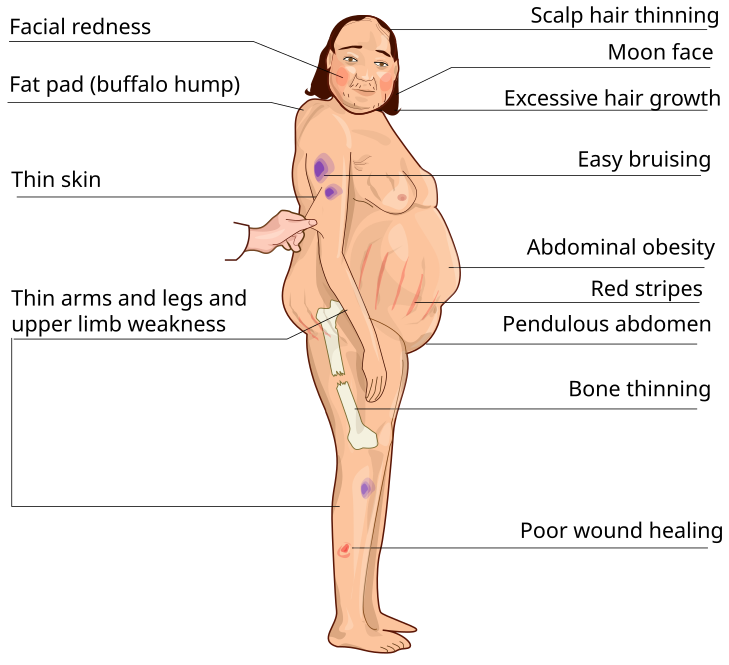
| Weight | Weight loss | Central obesity, moon face, buffalo hump |
| Skin | Hyperpigmentation | Poor wound healing |
Addison’s disease (adrenal insufficiency)
- Cause: Autoimmune destruction of adrenal glands → Decreased cortisol and aldosterone.
- Additional symptoms: Fatigue, salt craving, weakness.
- PT implications:
- Monitor for hypoglycemia, hypotension, and fatigue.
- Avoid overexertion due to limited stress response.
- Risk of adrenal crisis (severe hypotension, dehydration, shock) → medical emergency.
Cushing’s syndrome (hyperfunction of adrenal glands)
- Cause: Excess cortisol from long-term glucocorticoid (steroid) use, or from a tumor: most often a pituitary tumor that makes too much ACTH (Cushing’s disease), less often an adrenal tumor.
- Additional symptoms: Muscle atrophy, osteoporosis.
- PT implications:
- Fall risk due to osteoporosis and muscle weakness.
- Monitor BP and glucose levels (risk of hypertension and diabetes).
- Avoid high-impact exercises to prevent fractures.
Diabetes mellitus (DM)
Type 1 diabetes (insulin-dependent)
- Cause: Autoimmune destruction of pancreatic beta cells → No insulin production.
- Symptoms: Polyuria, polydipsia, polyphagia, weight loss, ketoacidosis (DKA risk).
- PT implications:
- Monitor for hypoglycemia.
- Exercise increases insulin sensitivity, so the patient (per physician guidance) may need to adjust insulin dose or carbohydrate intake; the PTA monitors glucose and reports trends to the supervising PT.
- Avoid exercise during peak insulin activity to prevent hypoglycemia.
Type 2 diabetes (insulin-resistant)
- Cause: Insulin resistance due to obesity, genetics, and a sedentary lifestyle.
- Symptoms: Polyuria, polydipsia, slow wound healing, neuropathy, blurred vision, fatigue.
- PT implications:
- Encourage aerobic and resistance exercise to improve insulin sensitivity.
- Monitor for neuropathy and fall risk.
- Check for foot ulcers and skin integrity.
Associated diabetic conditions
- Hypoglycemia
- Cause: Low blood sugar (<70 mg/dL)
- Insulin, a hormone made by the pancreas that helps glucose get into cells, can cause low blood glucose as a side effect; low blood glucose is treated by eating or drinking 15 to 20 grams of glucose or carbohydrate (the 15 g below is the lower end).
- Symptoms: Sweating, confusion, dizziness, tachycardia
- PT considerations: stop exercise immediately, give 15 g of fast-acting carbohydrate (juice or glucose tablets), and recheck glucose in 15 minutes; repeat until it’s 70 mg/dL or higher, then apply the pre-exercise thresholds below before resuming. If the patient is unresponsive or can’t swallow, activate emergency services and give nothing by mouth. Report the episode to the supervising PT.
- Exercise-induced hypoglycemia can also appear hours after a session, so check the patient’s status before they leave.
- Diabetic ketoacidosis (DKA)
- Cause: No insulin production causes fat breakdown and release of ketones in the bloodstream
- Symptoms: Fruity breath, deep breathing (Kussmaul), nausea, confusion
- PT considerations: medical emergency - stop exercise and notify the supervising PT immediately.
- Peripheral neuropathy
- Cause: Nerve damage from prolonged hyperglycemia
- Symptoms: Numbness, tingling, burning pain in feet/hands
- PT considerations: foot care education, balance training, fall prevention; a patient should not walk barefoot or in just socks, even indoors, because reduced feeling in the feet means an injury may go unnoticed
- Diabetic retinopathy
- Cause: Retinal blood vessel damage due to hyperglycemia
- Symptoms: Vision loss, blurred vision
- PT considerations: avoid head-down exercises, and high-impact exercises that can raise blood pressure increasing pressure on the damaged retinal vessels.
- Nephropathy
- Cause: Kidney damage from diabetes due to hyperglycemia
- Symptoms: Protein in urine, swelling, hypertension
- PT considerations: monitor hydration levels and blood pressure
- Peripheral artery disease (PAD)
- Cause: Poor circulation in legs due to vascular damage from hyperglycemia
- Symptoms: Claudication (leg pain with walking), cold feet
- PT considerations: use graded walking program
Hypoglycemia vs. hyperglycemia/DKA
| Hypoglycemia | Hyperglycemia/DKA | |
|---|---|---|
| Onset | Rapid (minutes) | Gradual (hours to days) |
| Skin | Cool, clammy | Warm, dry |
| Breathing | Normal or rapid | Deep, labored (Kussmaul) |
| Breath odor | None | Fruity |
| Immediate PTA action | Stop exercise, give fast-acting carbohydrate, recheck in 15 minutes | Stop exercise, give no carbohydrate, notify the supervising PT |
If you can’t tell which it is and no glucose reading is available, treat it as hypoglycemia and give fast-acting carbohydrate.
Safe blood sugar levels for physical therapy
Before exercise
- If blood sugar is less than 90 mg/dL: Have a small carbohydrate snack (15-30g) and have patient recheck glucose levels.
- If blood sugar is 90-124 mg/dL: Have a small carbohydrate snack (about 10g) before exercising.
- If blood sugar is 125-250 mg/dL: Safe to exercise.
- If blood sugar is over 250 mg/dL: The patient should check their urine for ketones.
- If ketones are present: Do not exercise, as this can lead to diabetic ketoacidosis.
- If no ketones are present: Exercise cautiously, monitor closely, and stay hydrated.
During and after exercise
- Monitor frequently: Check the patient’s blood sugar every 30 minutes during activity, especially during high-intensity activity or for a patient with type 1 diabetes on insulin.
- Stay hydrated: Drink plenty of fluids before, during, and after exercise.
Endocrine medications and exercise
Contracting muscle takes up glucose without needing insulin, and after a session the muscles stay more sensitive to insulin for a day or longer (up to about 48 hours after prolonged exercise). That is why exercise improves glucose control, and also why it can push glucose too low in a patient whose medication keeps lowering it.
- Insulin and sulfonylureas (insulin secretagogues): the drugs most likely to cause exercise-induced hypoglycemia, during the session or afterward; delayed (often overnight) lows typically come 6-15 hours later and can occur up to 48 hours after. Metformin generally needs no adjustment for exercise. The patient and physician may lower the dose or add carbohydrate on exercise days; the PTA checks glucose and reports episodes to the supervising PT.
- Peak insulin action: rapid-acting insulin peaks within about 90 minutes of injection, when hypoglycemia risk is greatest, so avoid scheduling exercise at that peak.
- Injection site: muscle contraction, massage, and heat all speed insulin absorption and raise hypoglycemia risk. Avoid vigorous exercise of a limb at a recent injection site, and don’t apply hot packs, diathermy, or thermal ultrasound over an injection or insulin-pump infusion site.
- Beta-blockers: can blunt the tachycardia that normally signals hypoglycemia, so watch for sweating and confusion instead, and check glucose before and after exercise.
- Corticosteroids: raise blood glucose, most in the afternoon and evening after a morning dose, and cause bone loss; glucocorticoid-induced osteoporosis is the most common secondary osteoporosis, and vertebral fractures are its hallmark. Monitor glucose in a patient with diabetes and follow the fall and fracture precautions for osteoporosis.
- Thyroid replacement (levothyroxine): a dose that is too high acts like hyperthyroidism, raising heart rate and the risk of atrial fibrillation and bone loss. Check resting heart rate and rhythm, and report new tachycardia, palpitations, or an irregular pulse.
These effects follow the patient into every setting: a patient on insulin in cardiac rehab or after a joint replacement needs the same glucose checks as one referred for diabetes, and a hot pack for back pain shouldn’t sit over an abdominal injection site.
Metabolic disorders
The metabolic system includes chemical processes that maintain life, including energy production and nutrient utilization.
Osteoporosis
- Cause: Decreased bone density (aging, menopause, steroid use, hyperthyroidism).
- Symptoms: Fractures, kyphosis, back pain.
- PT implications:
- Weight-bearing exercise to improve bone density.
- Avoid spinal flexion exercises to prevent vertebral fractures.
- Balance training to prevent falls.
- DEXA (Dual-Energy X-ray Absorptiometry) scans are used to measure bone mineral density and are the most accurate way to assess bone health.
- Determined by T-score:
- Normal: T-score of -1.0 or higher
- Osteopenia: T-score below -1.0 but above -2.5
- Osteoporosis: T-score of -2.5 or lower
- Determined by T-score:
Paget’s disease
- Cause: Excessive bone turnover → Weak, deformed bones.
- Symptoms: Bone pain, deformities, fractures, and hearing loss.
- PT implications:
- Low-impact exercise to maintain mobility.
- Monitor for fractures and joint dysfunction.
Gout (metabolic arthritis)
- Cause: Uric acid crystal buildup in joints (linked to diet, kidney dysfunction).
- Symptoms: Severe joint pain (big toe common), redness, swelling.
- PT implications:
- Avoid excessive weight-bearing during flares.
- Encourage hydration and dietary modifications.
Metabolic syndrome
Metabolic syndrome is a cluster of conditions that increase the risk of cardiovascular disease, type 2 diabetes, and stroke. It is diagnosed when a person has three or more of the following risk factors:
Criteria for metabolic syndrome
- Abdominal obesity
- Waist circumference:
- Men: >40 inches (102 cm)
- Women: >35 inches (88 cm)
- Waist circumference:
- Elevated blood pressure
- ≥130/85 mmHg or taking antihypertensive medication
- Elevated fasting blood glucose
- ≥100 mg/dL or diagnosed diabetes
- High triglycerides
- ≥150 mg/dL or taking medication for high triglycerides
- Low HDL (good cholesterol)
- Men: <40 mg/dL
- Women: <50 mg/dL
PT considerations
- Exercise recommendations:
- Focus on aerobic exercise (brisk walking, cycling, swimming)
- Include resistance training to improve insulin sensitivity
- Gradual progression to prevent fatigue and improve adherence
- Weight management: encourage lifestyle changes like a healthy diet and activity.
- Blood pressure monitoring: check BP before and after exercise; avoid high-intensity exercise if BP or diabetes is uncontrolled.