



Lymphedema
Anatomy and physiology
Lymphatic physiology
The lymphatic system works with the venous system to return fluid to the bloodstream, removes plasma proteins from tissue, and filters antigens, bacteria, and waste products. It also produces lymphocytes, a type of white blood cell that supports immune function; all white blood cells originate in the bone marrow, but organs like the thymus, spleen, and lymph nodes are crucial for lymphocyte development and function.
Lymph nodes
Lymph nodes are a series of sinuses that filter antigens and bacteria out of lymph fluid, which forms when plasma seeps out of blood capillaries into the surrounding tissue. This filtering is key to the body’s immune response.
The body contains roughly 600 lymph nodes, with about 300 of them in the head and neck. The axillary region has the largest concentration in the upper body and filters lymph from the arms and breasts, while the inguinal, or groin, region has the largest concentration in the lower body and filters lymph from the legs and lower abdomen.
Two primary lymphatic ducts of the body
- Right lymphatic duct
- Thoracic duct
Lymph fluid composition
Lymph fluid is a transparent, yellowish fluid containing water, proteins, lipids, minerals, and hormones. The body produces roughly 2-3 L of this fluid daily, which the lymphatic vessels return to the bloodstream.
Pathology
Lymphedema
- Excessive accumulation of lymph fluid due to dysfunction in the lymphatic system, leading to increased edema
- Causes: Surgery, physical trauma, radiation, infection, etc
Effects of lymphedema
- Chronic swelling
- Excessive tissue proteins
- Fibrotic changes
- Chronic inflammation
- Infections - cellulitis
- Skin changes - ‘peau d’orange’- a medical term describing a characteristic appearance of the skin (skin of an orange)
Related impairments
- Functional deficits
- Loss of mobility
- Difficulty wearing normal clothing
- Psychological issues
Stages of lymphedema
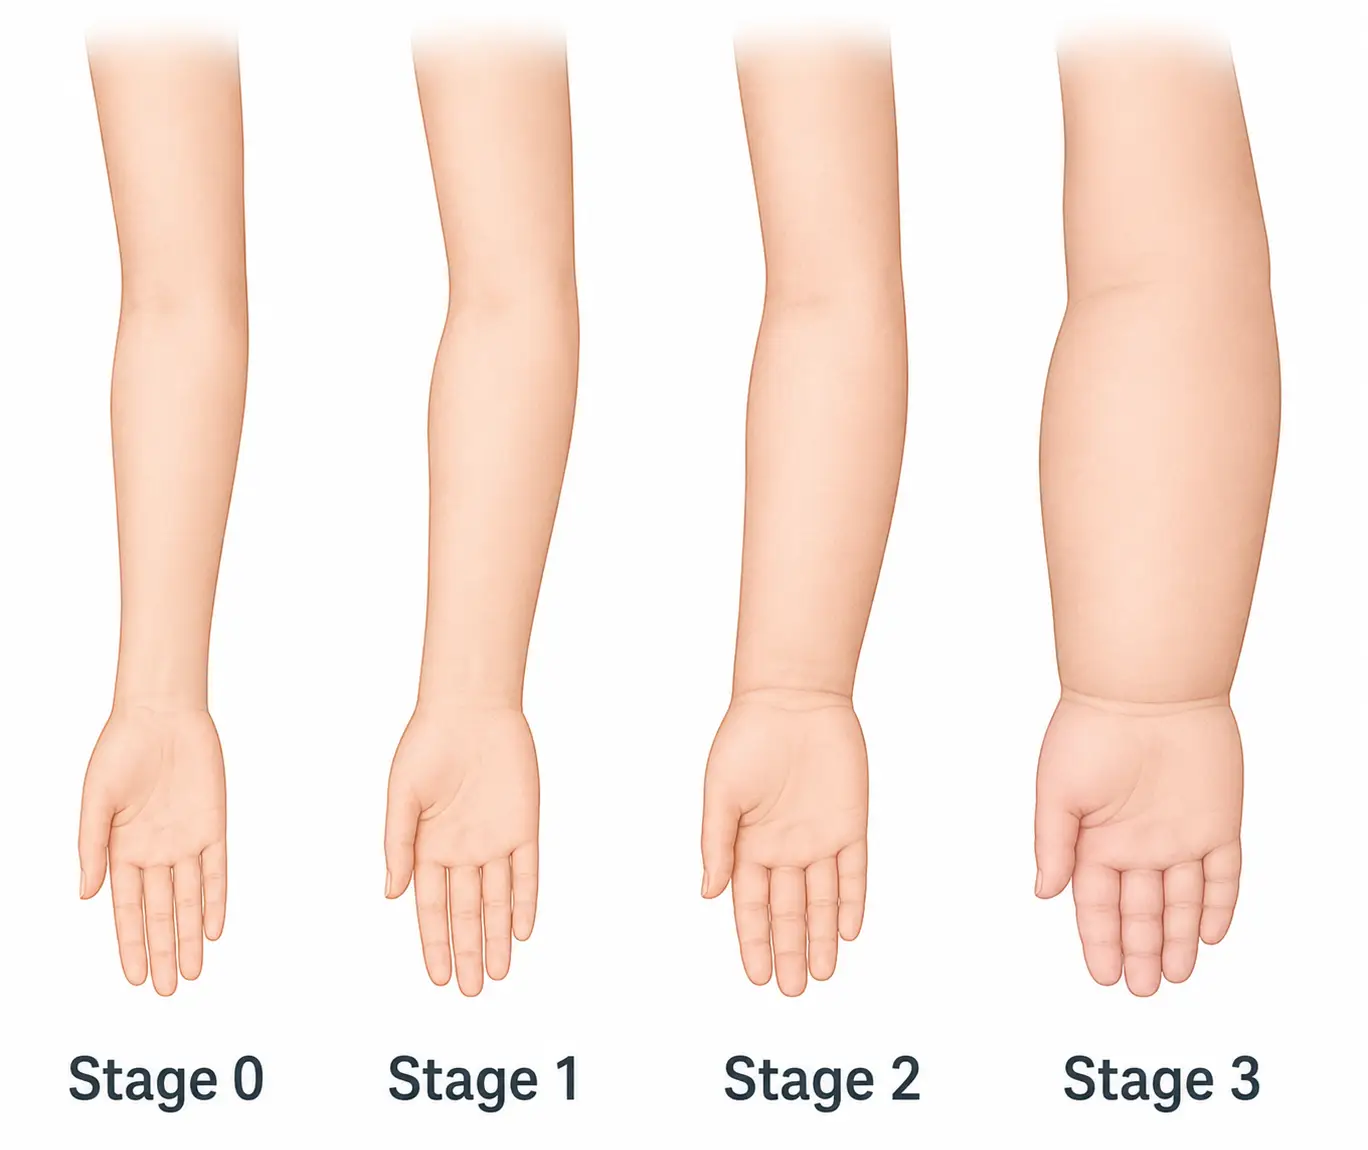
Lymphedema is staged by how reversible the swelling is and how much fibrosis has developed, ranging from stage 0 (no visible swelling) to stage 3 (irreversible hardening).
Stage 0
- Latent, subclinical condition
- Swelling not evident despite impaired lymph system
Stage 1
- Completely and spontaneously reversible
- Soft, pitting edema
- Little to no fibrosis
- Skin easily pinched and moved
- Stemmer sign negative
Stage 2
- Spontaneously irreversible
- Tissues are usually fibrotic
- Pitting requires strong pressure or no pitting
- Can usually be reversed with treatment
- Stemmer sign present
Stage 3 - Elephantiasis
- Irreversible
- No pitting, significant fibrosis
- Hardening of the skin
- Stemmer sign present
The following table compares the four stages of lymphedema on reversibility, pitting, fibrosis, and Stemmer sign.
| Stage | Reversible? | Pitting | Fibrosis | Stemmer sign |
|---|---|---|---|---|
| 0 (latent) | No visible swelling yet | None | None | Negative |
| 1 | Yes, spontaneously (subsides with elevation) | Soft, pitting | Little to none | Negative |
| 2 | Not spontaneously; reduced with treatment | Only with strong pressure, or none | Usually present | Present |
| 3 (elephantiasis) | No | None | Significant, with skin hardening | Present |
Goals of manual lymph drainage
Manual lymph drainage (MLD) is one part of complete decongestive therapy (CDT), the standard treatment approach for lymphedema, which also includes compression, exercise, and skin care. CDT has two phases: an intensive phase of daily treatment to reduce limb volume, and a maintenance phase where the patient self-manages with garments and exercise. The PTA carries out the PT’s plan of care, collects data such as limb girth, and reports changes back to the PT rather than modifying the plan independently.
- Peristalsis of lymph fluid
- Breakdown of fibrotic tissues
- Increase lymph volume in lymph vessels
- Decrease congestion in the interstitium
Basic principles
Decongestion always begins proximally, clearing the nodes closest to the trunk before moving to the affected lymphotome, since clearing proximal nodes first opens a path for fluid to drain. Treatment starts with deep breathing, then AROM exercises in a proximal-to-distal progression. Massage is then directed toward the cleared nodes in a distal-to-proximal direction, using very light pressure so the lymphatic vessels aren’t collapsed.
Contraindications
Contraindications (acute infection, acute congestive heart failure, acute DVT, and acute renal failure are absolute; the others are relative and require PT-directed modification):
- Bacterial infection
- Acute congestive heart failure
- Acute deep vein thrombosis
- Acute renal disease
- Acute pulmonary edema
- Malignancy
- Arterial disease
- Sensation deficits
- Low blood counts
- Areas of inflammation
- Open wounds
Precautions
Precautions require caution, not a treatment stop:
- Perform exercise only with compression in place
- Avoid heat sources, such as saunas and hot tubs, on the affected limb
- Avoid blood pressure readings, injections, and blood draws on the affected limb
- Monitor the affected limb closely and treat any skin breaks promptly to prevent infection
Bandaging techniques
Compression garments
- Maintains the reduction gained during therapy
- Transition to garments when reduction plateaus
- Garments for daytime wear, options for nighttime
- Insurance coverage varies greatly
Therapeutic exercise
- Exercises facilitate muscle pumping
- Should be done with compression
- Progress from proximally to distally
- Resistance starts light and progresses slowly, with the compression garment on; slowly progressive resistance training does not worsen lymphedema and reduced flare-ups in breast cancer-related lymphedema
Patient education
- Home exercise
- Self-massage
- Skin care
- Precautions
- Compression garments