


Achievable logoAchievable logo
NCLEX
Sign in
Sign up
Purchase
Textbook
Practice exams
Support
How it works
Resources
Exam catalog
Mountain with a flag at the peak
Textbook
Introduction
1. Safe and effective care environment
2. Health promotion and maintenance
3. Psychosocial Integrity
4. Physiological Integrity
4.1 Basic care and comfort
4.2 Pharmacological and parenteral therapies
4.3 Reduction of risk potential
4.3.1 Diagnostic tests and lab values
4.3.2 Monitoring for complications of procedures
4.3.3 Changes in vital signs and neurological status
4.3.4 Electrolyte imbalances and fluid status
4.3.5 Medical equipment use and safety
4.3.6 Potential complications of devices and procedures
4.4 Physiological adaptation
Wrapping up
Achievable logoAchievable logo
4.3.2 Monitoring for complications of procedures
Achievable NCLEX
4. Physiological Integrity
4.3. Reduction of risk potential
Our NCLEX course is currently in development and is a work-in-progress.

Monitoring for complications of procedures

9 min read
Font
Discuss
Share
Feedback

Introduction

Monitoring for complications after procedures is a core nursing responsibility and a high-yield area on the Next Generation NCLEX (NGN). The nurse is often the first to detect deterioration, subtle changes, or early warning signs following surgery or invasive procedures. Timely recognition and escalation can prevent progression to life-threatening outcomes such as hemorrhage, sepsis, shock, or respiratory failure.

This section focuses on common postoperative and invasive procedure complications, with emphasis on older adults, hospitalized clients, and lines, drains, tubes, and catheters frequently tested on the NCLEX.

Preoperative teaching - covering incentive spirometer use, pain-control expectations, and early ambulation - helps clients recognize and report warning signs after the procedure, so client education is itself part of complication prevention.

Learning objectives

By the end of this section, the learner should be able to:

  • Identify expected vs. abnormal post-procedure findings
  • Recognize early warning signs of complications
  • Prioritize nursing assessments and interventions
  • Apply NGN-style clinical reasoning to post-operative scenarios

Core principle: Trend, not snapshot

NGN questions emphasize patterns over time, not isolated values. A single abnormal vital sign may be less concerning than progressive change.

Key NGN insight:

The nurse’s role is to recognize progressive changes in vital signs, drainage, mental status, urine output, and laboratory values, not just document them. Trends often indicate deterioration before a single value becomes critically abnormal.

Major categories of post-procedure complications

1. Hemorrhage and bleeding

Common causes

Postoperative hemorrhage typically results from inadequate hemostasis, anticoagulant therapy, coagulopathy, or a dislodged suture or drain.

Key assessment findings

  • Increasing drainage above the expected amount for the procedure
  • Bright red blood soaking dressings
  • Hematoma or swelling at surgical site
  • Tachycardia, hypotension
  • Decreasing hemoglobin/hematocrit
  • Restlessness or anxiety (early hypovolemia sign)

Nursing priorities

  1. Assess and quantify blood loss.
  2. Reinforce dressing (do not remove first layer of the original postoperative dressing unless directed by the primary health care provider).
  3. Monitor vital signs closely.
  4. Maintain IV access.
  5. Notify the primary health care provider immediately.

NGN tip:

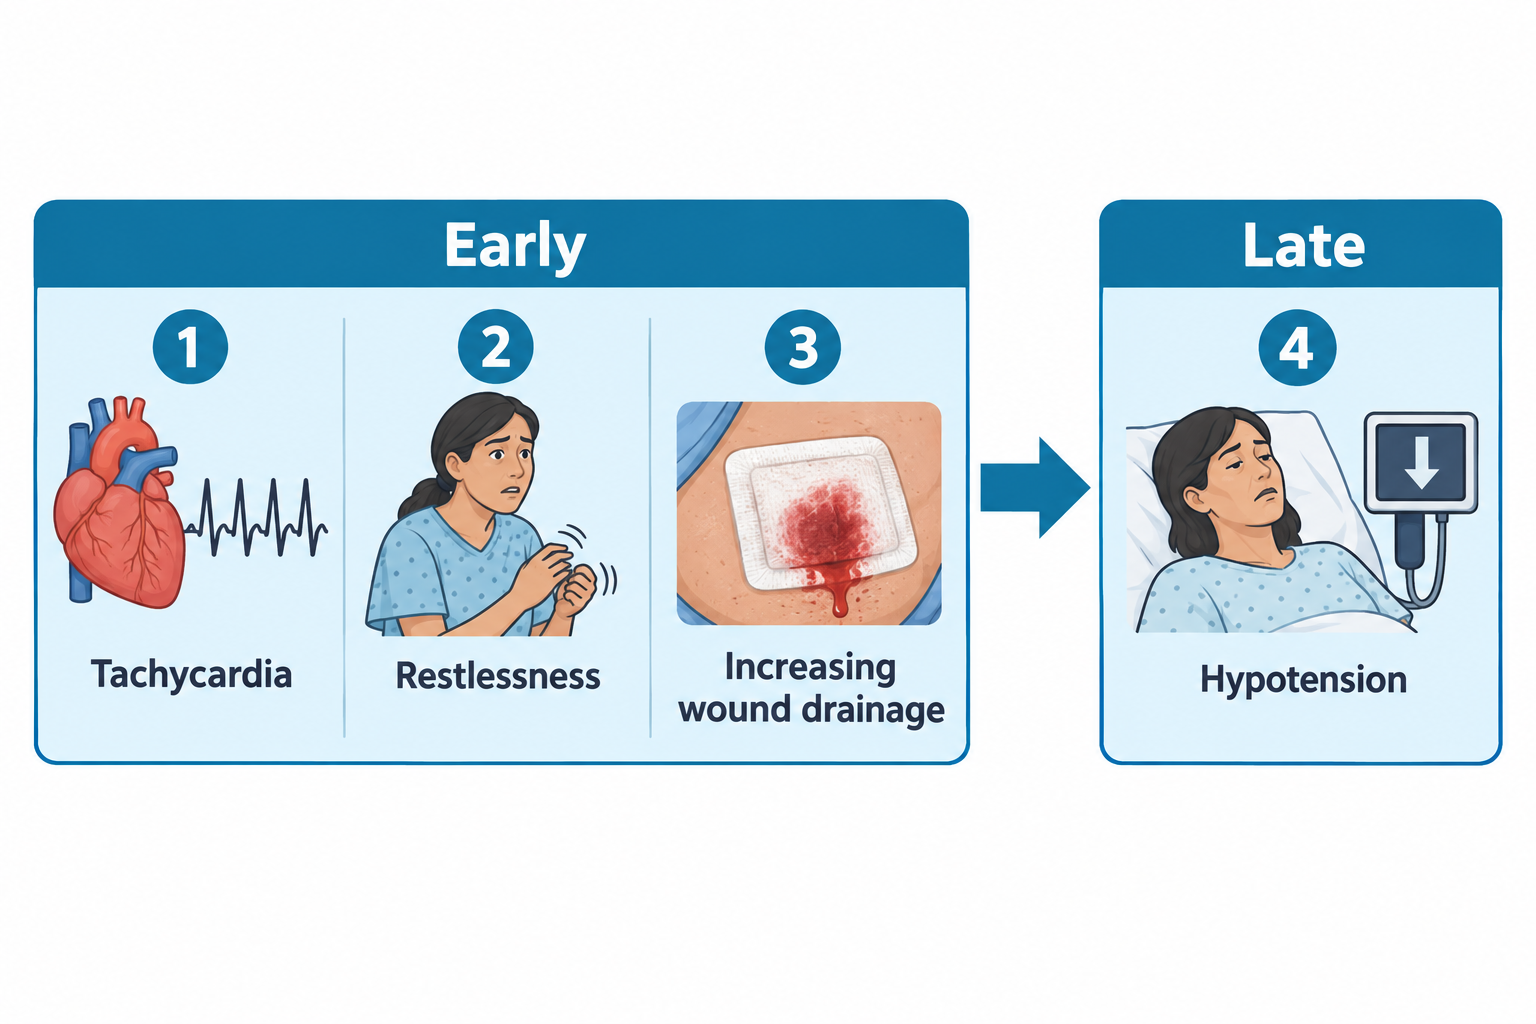
Hypotension is often a late sign of hemorrhage. Early signs include tachycardia, increasing drainage, and restlessness.

A four-step progression diagram divided into Early and Late zones connected by an arrow. Early zone shows a heart with an ECG trace labeled Tachycardia, a worried woman rubbing her hands labeled Restlessness, and a bloody wound dressing labeled Increasing wound drainage. Late zone shows a woman lying in a hospital bed looking pale and anxious next to a monitor with a downward arrow, labeled Hypotension.
Early versus late signs of postoperative hemorrhage
Achievable

2. Infection and sepsis

Risk factors

Risk increases with older age, diabetes, immunosuppression, prolonged surgery, and indwelling devices such as catheters and lines.

Early warning signs

  • Fever or hypothermia
  • Increased pain at site
  • Purulent drainage
  • Redness, warmth, swelling
  • Tachycardia
  • Altered mental status (especially in older adults)

Nursing actions

  • Inspect wound using aseptic technique.
  • Monitor WBC trends.
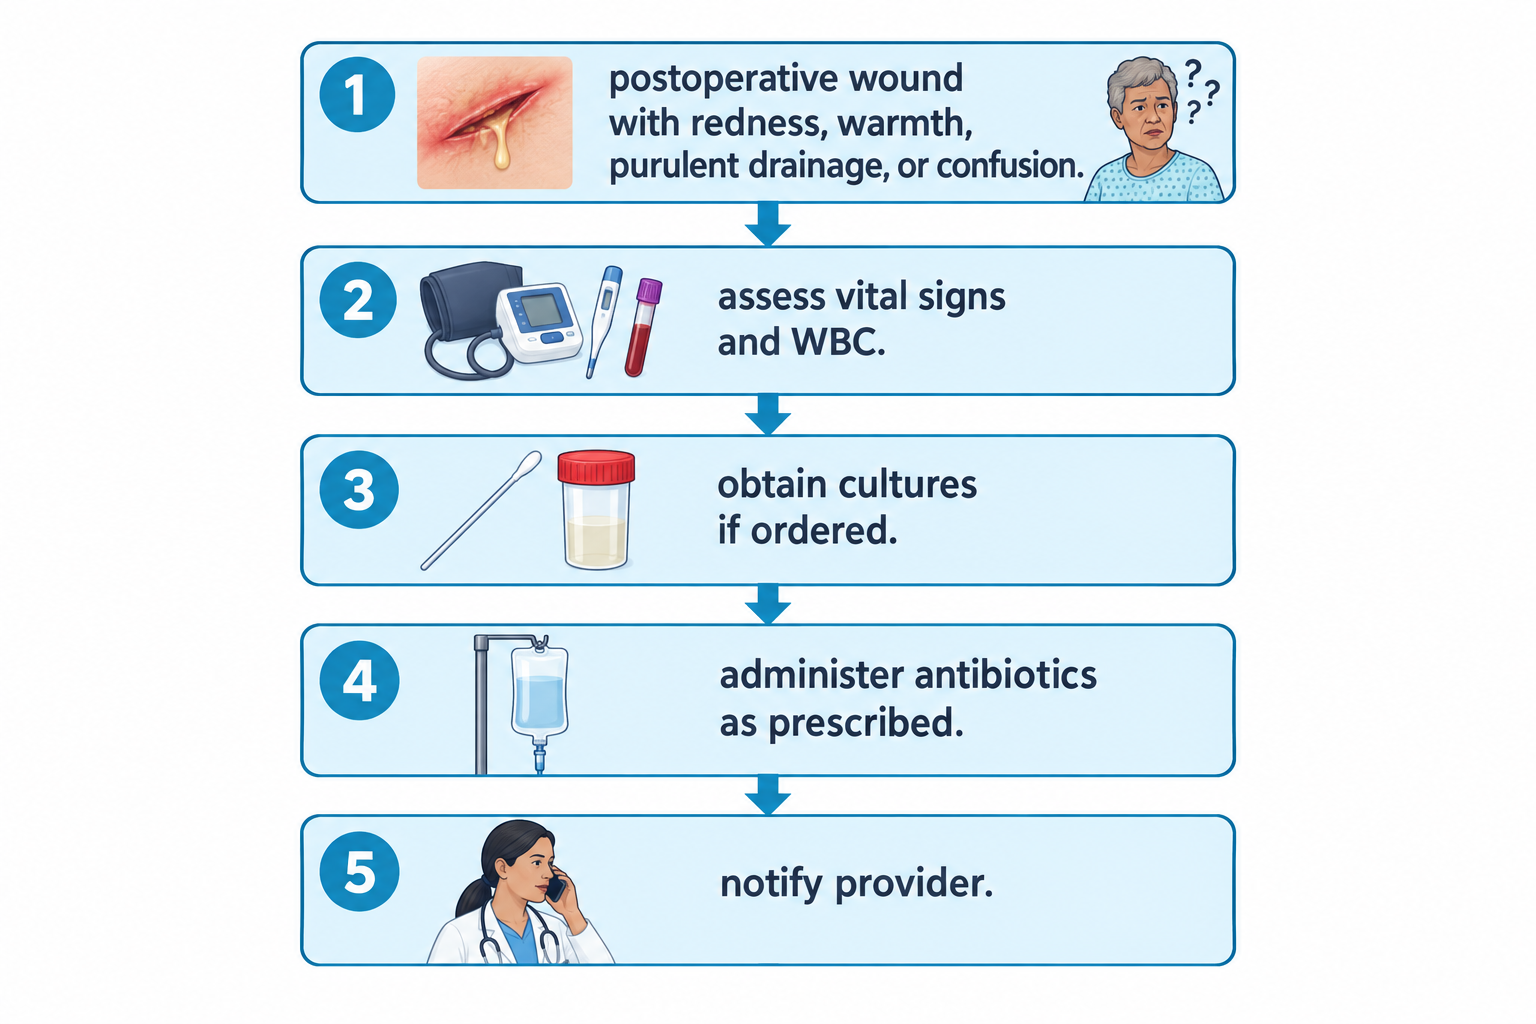
  • Obtain cultures if ordered.
  • Administer antibiotics as prescribed.
  • Escalate concerns promptly.

NGN insight: Older adult alert

In older adults, confusion may be the first sign of infection, even in the absence of fever or other classic symptoms.

A five-step flowchart: 1) An image of a postoperative wound with redness and purulent drainage beside a confused older adult with question marks, labeled 'postoperative wound with redness, warmth, purulent drainage, or confusion.' 2) A blood pressure cuff, thermometer, and blood sample tube labeled 'assess vital signs and WBC.' 3) A swab and specimen cup labeled 'obtain cultures if ordered.' 4) An IV pole with fluid bag labeled 'administer antibiotics as prescribed.' 5) A nurse on the phone labeled 'notify provider.'
Recognizing postoperative infection and sepsis
Achievable

3. Respiratory complications

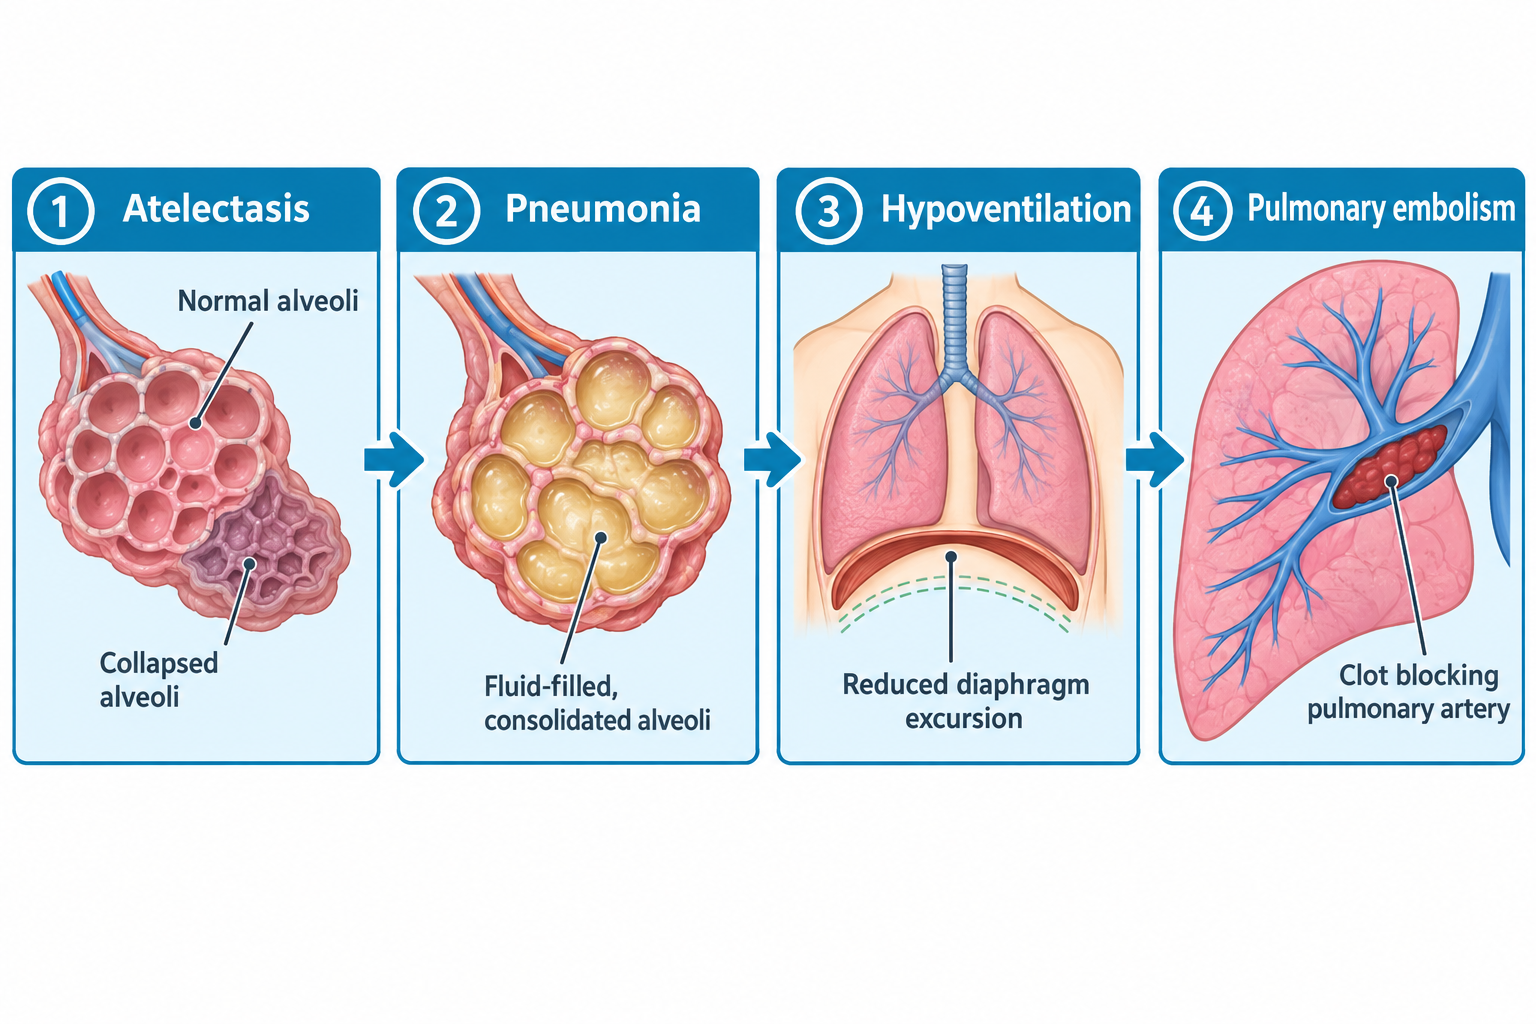
Common complications

  • Atelectasis
  • Pneumonia
  • Hypoventilation
  • Pulmonary embolism

Assessment findings

  • Decreased SpO₂
  • Shallow respirations
  • Crackles or diminished breath sounds
  • Dyspnea
  • Restlessness
  • Chest pain (PE concern)

Nursing interventions

  • Encourage incentive spirometry.
  • Reposition regularly (commonly every 2 hours).
  • Early ambulation.
  • Elevate head of bed.
  • Assess pain control, as pain and splinting may limit deep breathing and coughing.
  • During recovery from moderate sedation or anesthesia, monitor airway patency, level of consciousness, and SpO₂ until the client returns to baseline.

NGN insight: Pattern recognition

Recent anesthesia + ↓SpO₂ + shallow respirations = prioritize airway and breathing.

A four-panel comparison illustration: Panel 1 shows atelectasis with normal alveoli next to collapsed, deflated alveoli; Panel 2 shows pneumonia with alveoli filled with yellow fluid and consolidated; Panel 3 shows hypoventilation as a front view of the lungs and diaphragm with dashed lines indicating reduced diaphragm excursion; Panel 4 shows a pulmonary embolism as a dark red clot blocking a branch of the pulmonary artery within lung tissue.
Comparing atelectasis, pneumonia, hypoventilation, and pulmonary embolism
Achievable

4. Cardiovascular complications

Potential issues

  • Hypotension
  • Hypertension
  • Dysrhythmias
  • Deep vein thrombosis (DVT)
  • Shock

Assessment focus

  • Blood pressure trends
  • Heart rate and rhythm
  • Unilateral calf pain, swelling, warmth, redness, or tenderness
  • Urine output (<30 mL/hr concerning)
  • Skin temperature and color

Nursing priorities

  • Maintain fluid balance.
  • Apply sequential compression devices.
  • Monitor telemetry if indicated.
  • Report chest pain, sudden dyspnea, or unilateral leg swelling immediately to the primary health care provider.

5. Urinary and renal complications

Common problems

  • Urinary retention
  • Catheter-associated urinary tract infection (CAUTI)
  • Acute kidney injury

Assessment indicators

  • Low urine output
  • Bladder distention
  • Dark or concentrated urine
  • Dysuria (if catheter removed)
  • Rising creatinine

Nursing actions

  • Monitor strict intake and output.
  • Perform bladder scan if retention suspected.
  • Maintain catheter care and asepsis.
  • Encourage hydration if appropriate.

6. Gastrointestinal complications

Potential issues

  • Postoperative ileus
  • Nausea and vomiting
  • Constipation
  • Bowel obstruction

Assessment findings

  • Absent bowel sounds
  • Abdominal distention
  • Nausea/vomiting
  • Inability to pass flatus

Nursing management

  • Assess for return of gastrointestinal function (e.g., bowel sounds, passage of flatus, abdominal distention, nausea/vomiting) before feeding.
  • Maintain NPO status if ordered.
  • Monitor NG tube output.
  • Promote early ambulation.

Complications related to invasive devices

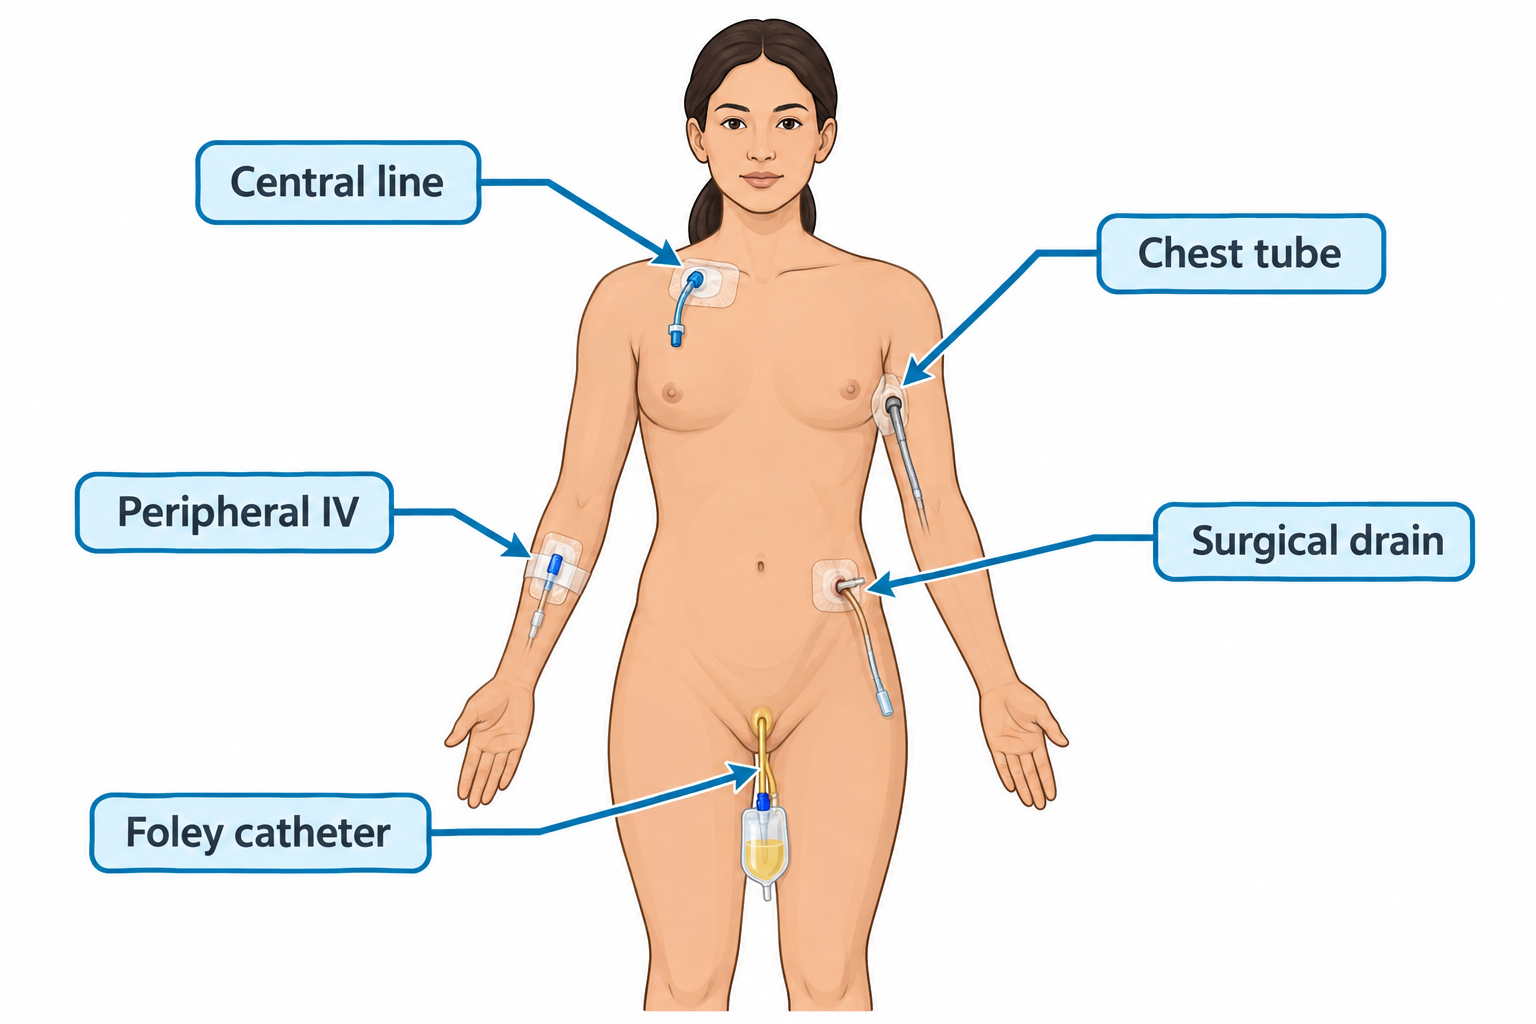
Common devices to monitor

  • Central lines
  • Peripheral IVs
  • Surgical drains
  • Foley catheters
  • Chest tubes

Key monitoring principles

  • Assess insertion sites for redness, swelling, leakage, tenderness, or signs of infection.
  • Ensure tubing is secured and unobstructed.
  • Measure and document output accurately.
  • Use aseptic technique when handling invasive devices.
  • For chest tubes, expect tidaling (rise and fall with respirations) in the water-seal chamber; continuous bubbling signals an air leak.
  • For continuous bladder irrigation (CBI), compare inflow and outflow volumes and watch for outflow that slows, stops, or turns bright red, which suggests obstruction or bleeding.

NGN tip:

Unexpected absence of drainage may be as significant as excessive drainage. Assess both the client and the device before assuming equipment malfunction.

Front view of an unclothed adult female figure with five invasive devices labeled and indicated by arrows: a central line dressing at the base of the neck near the clavicle, a peripheral IV in the forearm, a chest tube inserted at the lateral chest/axillary region with tubing running down the arm, a surgical drain exiting the lower abdomen, and a Foley catheter with attached urine drainage bag at the groin.
Monitoring common invasive devices
Achievable

Clinical vignette

A postoperative orthopedic client becomes confused and restless on day 2.

Vital signs:

  • Temp: 37.8°C (100°F)
  • HR: 104 bpm
  • SpO₂: 90% on room air
(spoiler)

Nursing action: Administer oxygen, assess breath sounds and respiratory status, and notify the primary health care provider.

Rationale: Confusion, hypoxemia, tachycardia, and recent surgery suggest postoperative respiratory compromise (e.g., atelectasis or pneumonia) while also raising concern for infection.

Less common but testable complications (brief list)

  • Malignant hyperthermia
  • Air embolism
  • Compartment syndrome
  • Anastomotic leak
  • Neurovascular compromise

(Recognize signs; detailed management often beyond NCLEX scope.)

Common pitfalls on the NCLEX:

  • If a client’s age isn’t stated, assume an adult client unless the question specifies otherwise.
  • NGN items often use multiple-response, partial-credit formats rather than single-best-answer questions, so evaluate every option rather than stopping at the first correct-looking choice.
  • Prioritize trend changes and airway, breathing, circulation (ABC) over an isolated abnormal value.
  • Remember that older adults may present atypically, such as confusion without fever.
  • Monitoring for complications is continuous, not episodic
  • Early subtle changes often precede collapse
  • NGN emphasizes clinical judgment, prioritization, and escalation
  • The nurse is the first line of defense post-procedure

Sign up for free to take 5 quiz questions on this topic

Previous
Next  | 4.3.3 Changes in vital signs and neurological status
All rights reserved ©2016 - 2026 Achievable, Inc.

Monitoring for complications of procedures

Introduction

Monitoring for complications after procedures is a core nursing responsibility and a high-yield area on the Next Generation NCLEX (NGN). The nurse is often the first to detect deterioration, subtle changes, or early warning signs following surgery or invasive procedures. Timely recognition and escalation can prevent progression to life-threatening outcomes such as hemorrhage, sepsis, shock, or respiratory failure.

This section focuses on common postoperative and invasive procedure complications, with emphasis on older adults, hospitalized clients, and lines, drains, tubes, and catheters frequently tested on the NCLEX.

Preoperative teaching - covering incentive spirometer use, pain-control expectations, and early ambulation - helps clients recognize and report warning signs after the procedure, so client education is itself part of complication prevention.

Learning objectives

By the end of this section, the learner should be able to:

  • Identify expected vs. abnormal post-procedure findings
  • Recognize early warning signs of complications
  • Prioritize nursing assessments and interventions
  • Apply NGN-style clinical reasoning to post-operative scenarios

Core principle: Trend, not snapshot

NGN questions emphasize patterns over time, not isolated values. A single abnormal vital sign may be less concerning than progressive change.

Key NGN insight:

The nurse’s role is to recognize progressive changes in vital signs, drainage, mental status, urine output, and laboratory values, not just document them. Trends often indicate deterioration before a single value becomes critically abnormal.

Major categories of post-procedure complications

1. Hemorrhage and bleeding

Common causes

Postoperative hemorrhage typically results from inadequate hemostasis, anticoagulant therapy, coagulopathy, or a dislodged suture or drain.

Key assessment findings

  • Increasing drainage above the expected amount for the procedure
  • Bright red blood soaking dressings
  • Hematoma or swelling at surgical site
  • Tachycardia, hypotension
  • Decreasing hemoglobin/hematocrit
  • Restlessness or anxiety (early hypovolemia sign)

Nursing priorities

  1. Assess and quantify blood loss.
  2. Reinforce dressing (do not remove first layer of the original postoperative dressing unless directed by the primary health care provider).
  3. Monitor vital signs closely.
  4. Maintain IV access.
  5. Notify the primary health care provider immediately.

NGN tip:

Hypotension is often a late sign of hemorrhage. Early signs include tachycardia, increasing drainage, and restlessness.

2. Infection and sepsis

Risk factors

Risk increases with older age, diabetes, immunosuppression, prolonged surgery, and indwelling devices such as catheters and lines.

Early warning signs

  • Fever or hypothermia
  • Increased pain at site
  • Purulent drainage
  • Redness, warmth, swelling
  • Tachycardia
  • Altered mental status (especially in older adults)

Nursing actions

  • Inspect wound using aseptic technique.
  • Monitor WBC trends.
  • Obtain cultures if ordered.
  • Administer antibiotics as prescribed.
  • Escalate concerns promptly.

NGN insight: Older adult alert

In older adults, confusion may be the first sign of infection, even in the absence of fever or other classic symptoms.

3. Respiratory complications

Common complications

  • Atelectasis
  • Pneumonia
  • Hypoventilation
  • Pulmonary embolism

Assessment findings

  • Decreased SpO₂
  • Shallow respirations
  • Crackles or diminished breath sounds
  • Dyspnea
  • Restlessness
  • Chest pain (PE concern)

Nursing interventions

  • Encourage incentive spirometry.
  • Reposition regularly (commonly every 2 hours).
  • Early ambulation.
  • Elevate head of bed.
  • Assess pain control, as pain and splinting may limit deep breathing and coughing.
  • During recovery from moderate sedation or anesthesia, monitor airway patency, level of consciousness, and SpO₂ until the client returns to baseline.

NGN insight: Pattern recognition

Recent anesthesia + ↓SpO₂ + shallow respirations = prioritize airway and breathing.

4. Cardiovascular complications

Potential issues

  • Hypotension
  • Hypertension
  • Dysrhythmias
  • Deep vein thrombosis (DVT)
  • Shock

Assessment focus

  • Blood pressure trends
  • Heart rate and rhythm
  • Unilateral calf pain, swelling, warmth, redness, or tenderness
  • Urine output (<30 mL/hr concerning)
  • Skin temperature and color

Nursing priorities

  • Maintain fluid balance.
  • Apply sequential compression devices.
  • Monitor telemetry if indicated.
  • Report chest pain, sudden dyspnea, or unilateral leg swelling immediately to the primary health care provider.

5. Urinary and renal complications

Common problems

  • Urinary retention
  • Catheter-associated urinary tract infection (CAUTI)
  • Acute kidney injury

Assessment indicators

  • Low urine output
  • Bladder distention
  • Dark or concentrated urine
  • Dysuria (if catheter removed)
  • Rising creatinine

Nursing actions

  • Monitor strict intake and output.
  • Perform bladder scan if retention suspected.
  • Maintain catheter care and asepsis.
  • Encourage hydration if appropriate.

6. Gastrointestinal complications

Potential issues

  • Postoperative ileus
  • Nausea and vomiting
  • Constipation
  • Bowel obstruction

Assessment findings

  • Absent bowel sounds
  • Abdominal distention
  • Nausea/vomiting
  • Inability to pass flatus

Nursing management

  • Assess for return of gastrointestinal function (e.g., bowel sounds, passage of flatus, abdominal distention, nausea/vomiting) before feeding.
  • Maintain NPO status if ordered.
  • Monitor NG tube output.
  • Promote early ambulation.

Complications related to invasive devices

Common devices to monitor

  • Central lines
  • Peripheral IVs
  • Surgical drains
  • Foley catheters
  • Chest tubes

Key monitoring principles

  • Assess insertion sites for redness, swelling, leakage, tenderness, or signs of infection.
  • Ensure tubing is secured and unobstructed.
  • Measure and document output accurately.
  • Use aseptic technique when handling invasive devices.
  • For chest tubes, expect tidaling (rise and fall with respirations) in the water-seal chamber; continuous bubbling signals an air leak.
  • For continuous bladder irrigation (CBI), compare inflow and outflow volumes and watch for outflow that slows, stops, or turns bright red, which suggests obstruction or bleeding.

NGN tip:

Unexpected absence of drainage may be as significant as excessive drainage. Assess both the client and the device before assuming equipment malfunction.

Clinical vignette

A postoperative orthopedic client becomes confused and restless on day 2.

Vital signs:

  • Temp: 37.8°C (100°F)
  • HR: 104 bpm
  • SpO₂: 90% on room air
(spoiler)

Nursing action: Administer oxygen, assess breath sounds and respiratory status, and notify the primary health care provider.

Rationale: Confusion, hypoxemia, tachycardia, and recent surgery suggest postoperative respiratory compromise (e.g., atelectasis or pneumonia) while also raising concern for infection.

Less common but testable complications (brief list)

  • Malignant hyperthermia
  • Air embolism
  • Compartment syndrome
  • Anastomotic leak
  • Neurovascular compromise

(Recognize signs; detailed management often beyond NCLEX scope.)

Common pitfalls on the NCLEX:

  • If a client’s age isn’t stated, assume an adult client unless the question specifies otherwise.
  • NGN items often use multiple-response, partial-credit formats rather than single-best-answer questions, so evaluate every option rather than stopping at the first correct-looking choice.
  • Prioritize trend changes and airway, breathing, circulation (ABC) over an isolated abnormal value.
  • Remember that older adults may present atypically, such as confusion without fever.
Key points
  • Monitoring for complications is continuous, not episodic
  • Early subtle changes often precede collapse
  • NGN emphasizes clinical judgment, prioritization, and escalation
  • The nurse is the first line of defense post-procedure

More from Reduction of risk potential

  • Diagnostic tests and lab values
  • Changes in vital signs and neurological status
  • Electrolyte imbalances and fluid status
  • Medical equipment use and safety
  • Potential complications of devices and procedures