



This browser is too old to run Achievable.

Update it, or open this page in a current version of Chrome, Safari, Firefox or Edge. On an iPhone or iPad, update iOS: every browser there runs on the version of Safari that comes with it.

Achievable logoAchievable logo
NPTE-PTA
Sign in
Sign up
Purchase
Textbook
Practice exams
Support
How it works
Resources
Exam catalog
Mountain with a flag at the peak
Textbook
Introduction
1. Cardiovascular system
2. Pulmonary system
2.1 Anatomy, ventilation, and pulmonary function tests
2.2 Auscultation and differential diagnosis of pulmonary system, lines and tubes
2.3 Understanding arterial blood gases
2.4 Interventions for pulmonary system
3. Neuromuscular system
4. Pediatrics
5. Musculoskeletal system
6. Other systems
7. Non-systems
Wrapping up
Achievable logoAchievable logo
2.3 Understanding arterial blood gases
Achievable NPTE-PTA
2. Pulmonary system

Understanding arterial blood gases

7 min read
Font
Discuss
Share
Feedback
Definitions
Arterial blood gases
Subset of tests that measure the amount of oxygen (O2​), carbon dioxide (CO2​), and pH of the blood; indicator of the function of lungs, kidneys, and acid-base balance in the body
Partial pressure of oxygen (PaO2​)
Pressure of dissolved oxygen in blood
Partial pressure of carbon dioxide (PaCO2​)
Pressure of dissolved carbon dioxide in the blood
pH
Measurement of acidity or alkalinity in blood
Bicarbonate (HCO3−​)
Chemical that assists with regulation of pH in blood

Important lab values

  • pH
    • Normal = 7.35-7.45
    • Below 7.35 = acidic
    • Above 7.45 = alkaline
Acid-base chart
Acid-base chart
Anatomy & Physiology by Lindsay M. Biga, Sierra Dawson, Amy Harwell, Robin Hopkins, Joel Kaufmann, Mike LeMaster, Philip Matern, Katie Morrison-Graham, Devon Quick & Jon Runyeon
/
Oregon State University
/
CC BY 4.0
  • Partial pressure of oxygen (PaO2​)

    • Normal = 75-100 mmHg (some references cite 80 mmHg as the lower limit - this chapter uses the 75 mmHg cutoff common in PT references)
    • Below 75 = hypoxemia
    • Above 100 = hyperoxemia (typically supplemental oxygen administration)
  • Partial pressure of carbon dioxide (PaCO2​) - related to respiratory conditions

    • Normal = 35-45 mmHg
    • Below 35 = alkaline
    • Above 45 = acidic
  • Bicarbonate (HCO3−​) - related to metabolic conditions

    • Normal = 22-26 mEq/L
    • Below 22 = acidic
    • Above 26 = alkaline

Acid-base diseases

  • Respiratory acidosis

    • Related diagnosis: COPD, pneumonia, atelectasis, anesthesia, drug overdose
    • Define: the lung does not efficiently remove carbon dioxide from the system, causing a buildup of carbon dioxide in the bloodstream
    • Lab values:
      • pH below 7.35
      • PaCO2​ above 45
    • Symptoms: hypoventilation, hypoxia, dyspnea, muscle weakness
  • Respiratory alkalosis

    • Related diagnosis: anxiety attacks, pulmonary embolism, mechanical ventilation
    • Define: the lung excessively removes carbon dioxide from the system, leading to decreased amounts of carbon dioxide in bloodstream
    • Lab values:
      • pH above 7.45
      • PaCO2​ below 35
    • Symptoms: hyperventilation, tachycardia, numbness/tingling of extremities, light-headedness
  • Metabolic acidosis

    • Related diagnosis: diabetic ketoacidosis, severe diarrhea, renal failure, sepsis or septic shock (lactic acidosis)
    • Define: accumulation of metabolic acids or excessive loss of bicarbonate, lowering blood pH
    • Lab values:
      • pH below 7.35
      • HCO3−​ below 22
    • Symptoms: headache, hyperkalemia, nausea/vomiting, Kussmaul respirations (compensatory hyperventilation)
  • Metabolic alkalosis

    • Related diagnosis: severe vomiting, excessive diuretic use, excessive antacid use, excessive gastrointestinal suctioning
    • Define: the body has removed too much acid or retained too much bicarbonate, leading to an alkaline shift in the bloodstream
    • Lab values:
      • pH above 7.45
      • HCO3−​ above 26
    • Symptoms: restlessness, tachycardia, compensatory hypoventilation, confusion
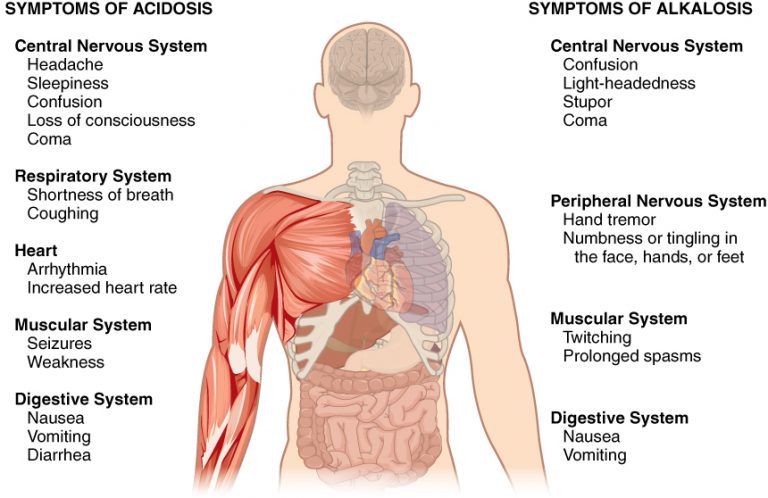
Symptoms of acidosis/alkalosis
Anatomy & Physiology by Lindsay M. Biga, Sierra Dawson, Amy Harwell, Robin Hopkins, Joel Kaufmann, Mike LeMaster, Philip Matern, Katie Morrison-Graham, Devon Quick & Jon Runyeon
/
Oregon State University
/
CC BY 4.0

The four disorders can present with overlapping symptoms, so distinguish them by management focus as well as by lab values:

Disorder Management focus
Respiratory acidosis Improve ventilation - positioning, airway clearance, breathing exercises, mechanical ventilation if severe
Respiratory alkalosis Treat the cause of hyperventilation - anxiety management, breathing retraining
Metabolic acidosis Primarily medical management of the underlying cause; the PTA monitors the patient’s response and reports findings to the PT
Metabolic alkalosis Primarily medical management of the underlying cause; the PTA monitors the patient’s response and reports findings to the PT

Compensation and ABG interpretation

Compensation is the body’s way of adjusting one system (respiratory or metabolic) to offset a disturbance in the other.

  • If the lungs are the problem, the kidneys try to help.
  • If the kidneys are the problem, the lungs try to help.

There are three types of compensation:

Type pH status Compensation present?
Uncompensated Abnormal No compensation
Partially compensated Abnormal Compensation is occurring
Fully compensated Normal (7.35-7.45) Compensation has corrected the pH

To interpret an ABG, work through the values in this order:

  1. Classify the pH as acidotic (below 7.35) or alkalotic (above 7.45). If the pH is within 7.35-7.45, use 7.40 as the midpoint: 7.35-7.39 leans acidotic and 7.41-7.45 leans alkalotic. That lean names the primary disorder in a fully compensated ABG.
  2. Find the value that explains the pH shift - that value names the primary disorder. If PaCO2​ moves opposite the pH (high with acidosis, low with alkalosis), the cause is respiratory. If HCO3−​ moves in the same direction as the pH (low with acidosis, high with alkalosis), the cause is metabolic.
  3. Check the opposing value: if it’s still in the normal range, the disorder is uncompensated; if it has shifted to help but the pH still hasn’t normalized, it’s partially compensated; if the pH has returned to the normal range, it’s fully compensated.

Partially compensated arterial blood gases

Definition:

  • pH is still outside the normal range, so the imbalance is not fully corrected.
  • The opposing system has begun to respond, but not enough to normalize pH.

Example: partially compensated respiratory acidosis

Value Result Interpretation
pH 7.30 Acidotic
PaCO2​ 55 mmHg High (respiratory acidosis)
HCO3−​ 29 mEq/L High (kidneys compensating)

Answer: Respiratory acidosis with partial metabolic compensation.

Fully compensated arterial blood gases

Definition:

  • The pH is back within normal range (7.35-7.45) due to effective compensation.
  • One component remains abnormal, indicating that a primary disorder still exists, but the body has corrected the pH.

Example: fully compensated metabolic acidosis

Value Result Interpretation
pH 7.36 Normal (low end - leans acidotic)
PaCO2​ 30 mmHg Low (lungs compensating)
HCO3−​ 18 mEq/L Low (metabolic acidosis)

Answer: Fully compensated metabolic acidosis.

PTA role: if a patient’s ABG values are abnormal, or you observe an adverse response during an intervention - new or worsening dyspnea, chest pain, dizziness, confusion, numbness/tingling, an abnormal breathing pattern, or a drop in systolic blood pressure as workload increases - stop the activity and communicate the finding to the supervising PT. The PTA collects and reports this data; adjusting the plan of care in response to it is the PT’s responsibility.

Arterial blood gas basics

  • ABGs measure O2​, CO2​, and pH to assess lung/kidney function and acid-base balance
  • Key values: PaO2​, PaCO2​ (respiratory marker), HCO3−​ (metabolic marker), pH

Normal lab value ranges

  • pH: 7.35-7.45 (below = acidic, above = alkaline)
  • PaO2​: 75-100 mmHg (below = hypoxemia, above = hyperoxemia)
  • PaCO2​: 35-45 mmHg (respiratory; below = alkaline, above = acidic)
  • HCO3−​: 22-26 mEq/L (metabolic; below = acidic, above = alkaline)

Four acid-base disorders

  • Respiratory acidosis: CO2​ retention (pH<7.35, PaCO2​>45); causes: COPD, pneumonia, overdose; symptoms: hypoventilation, hypoxia, dyspnea
  • Respiratory alkalosis: excess CO2​ loss (pH>7.45, PaCO2​<35); causes: anxiety, PE, mechanical ventilation; symptoms: hyperventilation, tachycardia, tingling
  • Metabolic acidosis: acid buildup/bicarbonate loss (pH<7.35, HCO3−​<22); causes: DKA, diarrhea, renal failure, sepsis; symptoms: Kussmaul respirations, hyperkalemia, nausea
  • Metabolic alkalosis: acid loss/bicarbonate retention (pH>7.45, HCO3−​>26); causes: vomiting, diuretics, antacids; symptoms: tachycardia, confusion, compensatory hypoventilation
  • Management focus: respiratory disorders treated via ventilation/breathing strategies; metabolic disorders managed medically with PTA monitoring/reporting

Compensation and ABG interpretation

  • Compensation: kidneys help respiratory problems, lungs help metabolic problems
  • Three states: uncompensated (pH abnormal, no compensation), partially compensated (pH abnormal, compensation occurring), fully compensated (pH normal, compensation corrected it)
  • Interpretation steps:
    • Classify pH as acidotic/alkalotic (use 7.40 midpoint if normal range)
    • Identify cause: PaCO2​ opposite pH direction = respiratory; HCO3−​ same direction as pH = metabolic
    • Check opposing value to determine uncompensated/partial/full compensation status

PTA role with ABG findings

  • Report abnormal ABGs or adverse signs (dyspnea, chest pain, dizziness, confusion, tingling, abnormal breathing, BP drop with exertion) to supervising PT
  • PTA collects/reports data only; PT adjusts plan of care

Sign up for free to take 12 quiz questions on this topic

Previous
Next  | 2.4 Interventions for pulmonary system
All rights reserved ©2016 - 2026 Achievable, Inc.

Understanding arterial blood gases

Definitions
Arterial blood gases
Subset of tests that measure the amount of oxygen (O2​), carbon dioxide (CO2​), and pH of the blood; indicator of the function of lungs, kidneys, and acid-base balance in the body
Partial pressure of oxygen (PaO2​)
Pressure of dissolved oxygen in blood
Partial pressure of carbon dioxide (PaCO2​)
Pressure of dissolved carbon dioxide in the blood
pH
Measurement of acidity or alkalinity in blood
Bicarbonate (HCO3−​)
Chemical that assists with regulation of pH in blood

Important lab values

  • pH
    • Normal = 7.35-7.45
    • Below 7.35 = acidic
    • Above 7.45 = alkaline
  • Partial pressure of oxygen (PaO2​)

    • Normal = 75-100 mmHg (some references cite 80 mmHg as the lower limit - this chapter uses the 75 mmHg cutoff common in PT references)
    • Below 75 = hypoxemia
    • Above 100 = hyperoxemia (typically supplemental oxygen administration)
  • Partial pressure of carbon dioxide (PaCO2​) - related to respiratory conditions

    • Normal = 35-45 mmHg
    • Below 35 = alkaline
    • Above 45 = acidic
  • Bicarbonate (HCO3−​) - related to metabolic conditions

    • Normal = 22-26 mEq/L
    • Below 22 = acidic
    • Above 26 = alkaline

Acid-base diseases

  • Respiratory acidosis

    • Related diagnosis: COPD, pneumonia, atelectasis, anesthesia, drug overdose
    • Define: the lung does not efficiently remove carbon dioxide from the system, causing a buildup of carbon dioxide in the bloodstream
    • Lab values:
      • pH below 7.35
      • PaCO2​ above 45
    • Symptoms: hypoventilation, hypoxia, dyspnea, muscle weakness
  • Respiratory alkalosis

    • Related diagnosis: anxiety attacks, pulmonary embolism, mechanical ventilation
    • Define: the lung excessively removes carbon dioxide from the system, leading to decreased amounts of carbon dioxide in bloodstream
    • Lab values:
      • pH above 7.45
      • PaCO2​ below 35
    • Symptoms: hyperventilation, tachycardia, numbness/tingling of extremities, light-headedness
  • Metabolic acidosis

    • Related diagnosis: diabetic ketoacidosis, severe diarrhea, renal failure, sepsis or septic shock (lactic acidosis)
    • Define: accumulation of metabolic acids or excessive loss of bicarbonate, lowering blood pH
    • Lab values:
      • pH below 7.35
      • HCO3−​ below 22
    • Symptoms: headache, hyperkalemia, nausea/vomiting, Kussmaul respirations (compensatory hyperventilation)
  • Metabolic alkalosis

    • Related diagnosis: severe vomiting, excessive diuretic use, excessive antacid use, excessive gastrointestinal suctioning
    • Define: the body has removed too much acid or retained too much bicarbonate, leading to an alkaline shift in the bloodstream
    • Lab values:
      • pH above 7.45
      • HCO3−​ above 26
    • Symptoms: restlessness, tachycardia, compensatory hypoventilation, confusion

The four disorders can present with overlapping symptoms, so distinguish them by management focus as well as by lab values:

Disorder Management focus
Respiratory acidosis Improve ventilation - positioning, airway clearance, breathing exercises, mechanical ventilation if severe
Respiratory alkalosis Treat the cause of hyperventilation - anxiety management, breathing retraining
Metabolic acidosis Primarily medical management of the underlying cause; the PTA monitors the patient’s response and reports findings to the PT
Metabolic alkalosis Primarily medical management of the underlying cause; the PTA monitors the patient’s response and reports findings to the PT

Compensation and ABG interpretation

Compensation is the body’s way of adjusting one system (respiratory or metabolic) to offset a disturbance in the other.

  • If the lungs are the problem, the kidneys try to help.
  • If the kidneys are the problem, the lungs try to help.

There are three types of compensation:

Type pH status Compensation present?
Uncompensated Abnormal No compensation
Partially compensated Abnormal Compensation is occurring
Fully compensated Normal (7.35-7.45) Compensation has corrected the pH

To interpret an ABG, work through the values in this order:

  1. Classify the pH as acidotic (below 7.35) or alkalotic (above 7.45). If the pH is within 7.35-7.45, use 7.40 as the midpoint: 7.35-7.39 leans acidotic and 7.41-7.45 leans alkalotic. That lean names the primary disorder in a fully compensated ABG.
  2. Find the value that explains the pH shift - that value names the primary disorder. If PaCO2​ moves opposite the pH (high with acidosis, low with alkalosis), the cause is respiratory. If HCO3−​ moves in the same direction as the pH (low with acidosis, high with alkalosis), the cause is metabolic.
  3. Check the opposing value: if it’s still in the normal range, the disorder is uncompensated; if it has shifted to help but the pH still hasn’t normalized, it’s partially compensated; if the pH has returned to the normal range, it’s fully compensated.

Partially compensated arterial blood gases

Definition:

  • pH is still outside the normal range, so the imbalance is not fully corrected.
  • The opposing system has begun to respond, but not enough to normalize pH.

Example: partially compensated respiratory acidosis

Value Result Interpretation
pH 7.30 Acidotic
PaCO2​ 55 mmHg High (respiratory acidosis)
HCO3−​ 29 mEq/L High (kidneys compensating)

Answer: Respiratory acidosis with partial metabolic compensation.

Fully compensated arterial blood gases

Definition:

  • The pH is back within normal range (7.35-7.45) due to effective compensation.
  • One component remains abnormal, indicating that a primary disorder still exists, but the body has corrected the pH.

Example: fully compensated metabolic acidosis

Value Result Interpretation
pH 7.36 Normal (low end - leans acidotic)
PaCO2​ 30 mmHg Low (lungs compensating)
HCO3−​ 18 mEq/L Low (metabolic acidosis)

Answer: Fully compensated metabolic acidosis.

PTA role: if a patient’s ABG values are abnormal, or you observe an adverse response during an intervention - new or worsening dyspnea, chest pain, dizziness, confusion, numbness/tingling, an abnormal breathing pattern, or a drop in systolic blood pressure as workload increases - stop the activity and communicate the finding to the supervising PT. The PTA collects and reports this data; adjusting the plan of care in response to it is the PT’s responsibility.

Key points

Arterial blood gas basics

  • ABGs measure O2​, CO2​, and pH to assess lung/kidney function and acid-base balance
  • Key values: PaO2​, PaCO2​ (respiratory marker), HCO3−​ (metabolic marker), pH

Normal lab value ranges

  • pH: 7.35-7.45 (below = acidic, above = alkaline)
  • PaO2​: 75-100 mmHg (below = hypoxemia, above = hyperoxemia)
  • PaCO2​: 35-45 mmHg (respiratory; below = alkaline, above = acidic)
  • HCO3−​: 22-26 mEq/L (metabolic; below = acidic, above = alkaline)

Four acid-base disorders

  • Respiratory acidosis: CO2​ retention (pH<7.35, PaCO2​>45); causes: COPD, pneumonia, overdose; symptoms: hypoventilation, hypoxia, dyspnea
  • Respiratory alkalosis: excess CO2​ loss (pH>7.45, PaCO2​<35); causes: anxiety, PE, mechanical ventilation; symptoms: hyperventilation, tachycardia, tingling
  • Metabolic acidosis: acid buildup/bicarbonate loss (pH<7.35, HCO3−​<22); causes: DKA, diarrhea, renal failure, sepsis; symptoms: Kussmaul respirations, hyperkalemia, nausea
  • Metabolic alkalosis: acid loss/bicarbonate retention (pH>7.45, HCO3−​>26); causes: vomiting, diuretics, antacids; symptoms: tachycardia, confusion, compensatory hypoventilation
  • Management focus: respiratory disorders treated via ventilation/breathing strategies; metabolic disorders managed medically with PTA monitoring/reporting

Compensation and ABG interpretation

  • Compensation: kidneys help respiratory problems, lungs help metabolic problems
  • Three states: uncompensated (pH abnormal, no compensation), partially compensated (pH abnormal, compensation occurring), fully compensated (pH normal, compensation corrected it)
  • Interpretation steps:
    • Classify pH as acidotic/alkalotic (use 7.40 midpoint if normal range)
    • Identify cause: PaCO2​ opposite pH direction = respiratory; HCO3−​ same direction as pH = metabolic
    • Check opposing value to determine uncompensated/partial/full compensation status

PTA role with ABG findings

  • Report abnormal ABGs or adverse signs (dyspnea, chest pain, dizziness, confusion, tingling, abnormal breathing, BP drop with exertion) to supervising PT
  • PTA collects/reports data only; PT adjusts plan of care

More from Pulmonary system

  • Anatomy, ventilation, and pulmonary function tests
  • Auscultation and differential diagnosis of pulmonary system, lines and tubes
  • Interventions for pulmonary system