


This browser is too old to run Achievable.

Update it, or open this page in a current version of Chrome, Safari, Firefox or Edge. On an iPhone or iPad, update iOS: every browser there runs on the version of Safari that comes with it.

Achievable logoAchievable logo
NPTE-PTA
Sign in
Sign up
Purchase
Textbook
Practice exams
Support
How it works
Resources
Exam catalog
Mountain with a flag at the peak
Textbook
Introduction
1. Cardiovascular system
1.1 Physiology of cardiac system
1.2 Cardiac pathologies
1.3 Cardiac rehabilitation
1.4 Electrocardiograms
1.5 Lab values and ankle brachial index
1.6 Cardiac exercise testing
2. Pulmonary system
3. Neuromuscular system
4. Pediatrics
5. Musculoskeletal system
6. Other systems
7. Non-systems
Wrapping up
Achievable logoAchievable logo
1.6 Cardiac exercise testing
Achievable NPTE-PTA
1. Cardiovascular system

Cardiac exercise testing

12 min read
Font
Discuss
Share
Feedback

This page covers the cardiac data a PTA gathers around an exercise session: test types, when testing is unsafe or must stop, how medications change the exercise response, and bedside findings like pulse, edema, and heart sounds.

Types of test

Each test below estimates cardiovascular capacity, but they differ in how close they push the patient toward maximal effort and in the setting where they’re used.

  • 6-minute walk test
    • Test goal: measure distance walked in 6 minutes with or without an assistive device; a self-paced, submaximal test. Healthy adults aged 40-80 walk a median of about 490-580 m, so a much shorter distance signals reduced functional capacity
    • Rationale: test for endurance related to cardiovascular health
    • Setting used: Phase I and Phase II of cardiac rehabilitation
    • Test advantages: Quick assessment of endurance that can be completed for lower-level patients
  • Graded exercise testing
    • Test goal: assess the maximal workload that can be applied to the cardiovascular system via treadmill testing at different grades (incline)
    • Rationale: provide the therapist with information on the highest capacity of exercise tolerance
      • Provides the maximal heart rate that can be used to then give the target heart range with activity
    • Setting: Phase II cardiac rehabilitation
    • Test advantages: Most accurate assessment tool of an individual’s exercise tolerance
  • Cycle ergometer test
    • Test goal: A submaximal graded exercise test used to estimate VO₂ max and assess cardiovascular endurance by progressively increasing cycling resistance/workload.
    • Rationale: the estimated VO₂ max is a useful indicator of cardiovascular fitness and aerobic endurance without requiring a maximal effort.
    • Setting: Phase II cardiac rehabilitation
    • Test advantage: Utilized over maximal exercise testing if the patient is unable to tolerate maximal testing parameters
Definitions
Maximal exercise test
Exercise testing that progresses to the highest workload, intensity, and duration the individual can tolerate.
Submaximal exercise test
An exercise assessment performed below the individual’s maximal effort level, terminated at a predetermined threshold (such as target heart rate, symptoms, blood pressure response, RPE, or ECG changes) to estimate cardiovascular fitness and exercise tolerance safely.
VO2 max
Maximum rate at which the body can take up and use oxygen during exercise. It is measured directly during maximal exercise testing and estimated from heart rate and workload during submaximal testing.

Normal vs. abnormal exercise response

The following table compares how heart rate, systolic blood pressure, and diastolic blood pressure normally respond to increasing exercise workload, versus signs of an abnormal response.


Vital sign Normal response Abnormal response
Heart rate Rises roughly in proportion to workload Fails to rise, or rises excessively for the workload
Systolic BP Rises with workload Fails to rise, or drops as workload increases
Diastolic BP Stays about the same or changes by roughly ±10 mmHg Rises or falls by more than that

Age-predicted max HR is 220−age; the Karvonen formula sets a target range from it: target HR=((HRmax​−HRrest​)×%intensity)+HRrest​.

Example: Karvonen target heart rate range

A 60-year-old patient has a resting heart rate of 70 bpm, and the supervising PT wants to train at 60-80% intensity. What’s the target heart rate range?

  • Estimate max HR: 220−60=160 bpm
  • Find heart rate reserve (HRR): 160−70=90 bpm
  • Lower bound: (90×0.60)+70=124 bpm
  • Upper bound: (90×0.80)+70=142 bpm

Answer: The target heart rate range is 124-142 bpm. Notice that %intensity multiplies the heart rate reserve (HR_max minus HR_rest), not HR_max directly - and HR_rest gets added back in at the end. For a patient on a beta blocker, heart rate doesn’t rise predictably with workload, so RPE replaces this target.

The Borg RPE scale runs 6-20, with moderate training typically around 11-14.

Contraindications for exercise testing

Absolute contraindications mean the test should not proceed; relative ones call for weighing risk against benefit.

Absolute:

  • Unstable angina
  • Acute myocardial infarction (within 2 days)
  • Uncontrolled symptomatic arrhythmia
  • Acute or decompensated congestive heart failure

Relative:

  • Resting systolic blood pressure >200 mmHg or diastolic >110 mmHg
  • Severe anemia (hemoglobin less than 8 g/dL) - see Lab values and ankle brachial index for other lab thresholds affecting activity
  • Advanced or complicated pregnancy

Reasons to stop exercise testing

Any sign below means stopping the test immediately and notifying the supervising PT.

  • Severe ST-segment depression of 2mm or greater
  • Cardiac arrest
  • Development of new 2nd or 3rd degree heart block
  • Patient requests to stop
  • Severe chest pain, dizziness, or dyspnea
  • Fall (drop) in systolic blood pressure of more than 10 mmHg despite increasing workload
  • Ataxia
  • Rise in systolic blood pressure >250 mmHg or diastolic >115 mmHg

PTA scope of practice: The PTA collects data and recognizes and communicates changes in a patient’s status to the supervising PT; evaluating the patient, interpreting findings, and changing the plan of care remain the PT’s responsibility. The same signs apply during any exercise session: when one appears, or a patient shows an adverse response to a medication listed below, the PTA stops the activity, activates emergency response when the sign calls for it, and reports it to the supervising PT, who decides whether and how the plan of care continues. Supervision and delegation rules are covered in PTA responsibilities, research, and ADA.

Cardiac medications

Each medication below changes how the body responds to exercise - knowing the mechanism helps you interpret vital signs correctly during a session.

  • Beta blockers (atenolol): hypertension medication
    • Mechanism of action: works on the heart muscle by blocking epinephrine; decreased heart rate
    • PT implications: do not use heart rate as an indicator for response to exercise; use the perceived exertion scale (RPE) to assist with tolerance to activity
  • Calcium channel blockers: hypertension medication
    • Mechanism of action: blocks calcium from entering vascular smooth muscle and heart muscle cells, causing vasodilation; non-dihydropyridine CCBs (diltiazem, verapamil) also slow heart rate, while dihydropyridine CCBs (amlodipine, nifedipine) act mainly on blood vessels and can cause a reflex increase in heart rate
    • PT implications: orthostatic hypotension
  • Angiotensin converting enzyme inhibitors (ACE inhibitors): hypertension medications
    • Mechanism of action: blocks the conversion of angiotensin I to angiotensin II, reducing vasoconstriction and causing peripheral vasodilation
    • PT implications: orthostatic hypotension, dizziness, palpitations, and a persistent dry cough
  • Diuretics (Lasix [furosemide], hydrochlorothiazide): hypertension medication
    • Mechanism of action: works on the kidneys to decrease the fluid retention in the body by moving sodium out of the body
    • PT implications: electrolyte imbalance (which can trigger dysrhythmias or palpitations), orthostatic hypotension and dizziness, muscle cramps, increased urination
  • Anticoagulants (e.g., warfarin [Coumadin]): decreases clotting of blood
    • Mechanism of action: works to reduce the clotting within the blood
    • PT implications: hemorrhage risk, can easily bruise
  • Antiplatelet drugs (aspirin, clopidogrel): keep platelets from clumping together to form clots, lowering the risk of heart attack and stroke
    • PT implications: bruise and bleed more easily; they do not slow heart rate, raise blood pressure, or treat orthostatic hypotension
  • Nitroglycerin: used specifically for angina pectoris
    • Mechanism of action: relaxes vascular smooth muscle (predominantly veins), releasing nitric oxide, which causes vasodilation, reduces cardiac preload, and lowers blood pressure
    • PT implications: dizziness, headache, weakness, nausea, and orthostatic hypotension. Patients with angina should have their nitroglycerin available during exercise. If chest pain occurs, stop the activity, have the patient sit, and follow the facility protocol; chest pain that isn’t relieved calls for emergency response and a report to the PT.
  • Digitalis (digoxin): medication commonly used to treat heart failure and certain atrial dysrhythmias.
    • Mechanism of action: increases the force of myocardial contraction (positive inotropic effect) and slows conduction through the AV node, which helps decrease heart rate.
    • PT implications: monitor heart rate, rhythm, blood pressure, and signs of digoxin toxicity. Patients with renal impairment are at increased risk for digoxin toxicity because digoxin is primarily excreted by the kidneys. Toxicity may lead to nausea, vomiting, visual disturbances, dysrhythmias, dizziness, and possible hospitalization.
  • Antihyperlipidemics (statins): cholesterol medication
    • Mechanism of action: blocks the production of cholesterol by the liver
    • PT implications: muscle pain, muscle weakness, fatigue, diarrhea, constipation, headache
  • Amiodarone (antiarrhythmic agent): unstable ventricular tachycardia and recurrent ventricular fibrillation medication
    • Mechanism of action: increases the duration of the action potential as well as the effective refractory period for cardiac cells
    • PT implications: monitor for bradycardia and hypotension; new cough or dyspnea may signal pulmonary toxicity; watch for worsening heart failure signs (edema, crackles, JVD)

Post-cardiac-surgery precautions

Two common postoperative precautions affect how a PTA progresses activity after cardiac surgery or device implantation:

  • Sternal precautions (after CABG or sternotomy): avoid lifting, pushing, or pulling more than about 5-10 lbs; avoid reaching behind the back or raising the elbows above shoulder height; have the patient hug a pillow against the chest for coughing or transfers. These precautions typically last 6-8 weeks, or per the surgeon’s protocol.
  • Pacemaker/ICD precautions: on the side of the implant, avoid raising the arm above shoulder height or forceful overhead/behind-the-back movement, and avoid heavy lifting or resisted upper-body exercise, for about 4-6 weeks or until the device site has healed, per the cardiology team’s protocol.

Observational cardiac topics

Beyond formal testing, a PTA also gathers bedside findings - pulse, edema, and heart sounds - that add to the clinical picture.

Pulse amplitude grading

  • 0: Absent - No pulse is palpable, even with maximum pressure. (Requires immediate medical evaluation).
  • 1+: Thready or weak - Barely perceptible; it fades in and out and can be easily obliterated with slight pressure.
  • 2+: Diminished - Easily palpable but weaker than a normal, expected pulse.
  • 3+: Normal - Easily felt, full, and requires moderate pressure to obliterate.
  • 4+: Bounding - Very strong and hyperactive; it does not disappear even with moderate to firm pressure

Some sources use a different convention where 2+ is normal and 3+ is increased (fuller than normal), so confirm which scale a facility or question is using before interpreting a grade.

Pitting edema grading (associated with right-sided heart failure):

  • Grade 1: 0-2 mm indentation and rebounds immediately
  • Grade 2: 3-4 mm indentation and rebounds within 15 seconds
  • Grade 3: 5-6 mm indentation and rebounds within 30-60 seconds
  • Grade 4: deeper than 6 mm (typically about 8 mm) indentation and rebounds 60 seconds or longer

Pitting edema leaves a temporary indentation when pressed; non-pitting edema, such as angioedema or advanced lymphedema, leaves no lasting indentation.

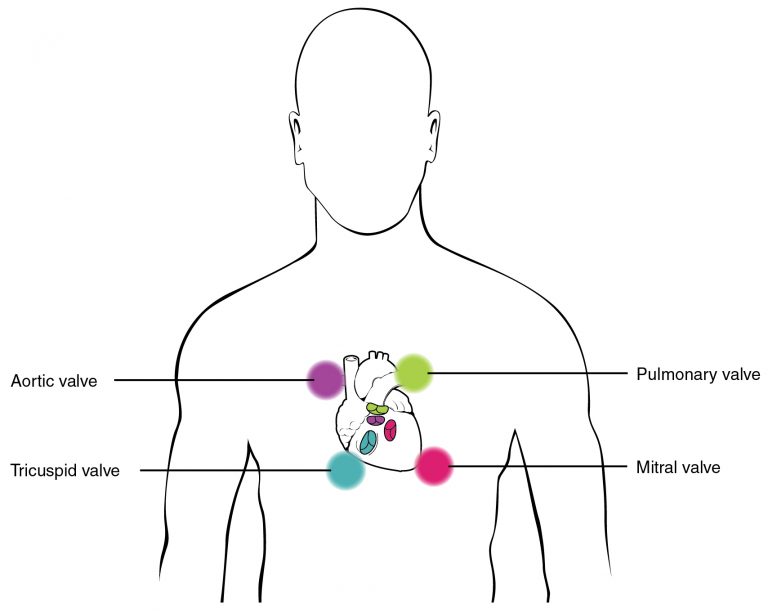
Auscultation of heart sounds

Location of valves of heart
Anatomy & Physiology by Lindsay M. Biga, Sierra Dawson, Amy Harwell, Robin Hopkins, Joel Kaufmann, Mike LeMaster, Philip Matern, Katie Morrison-Graham, Devon Quick & Jon Runyeon
/
Oregon State University
/
CC BY 4.0
  • S1:
    • Normal heart sound
    • First heart sound when atrioventricular (mitral and tricuspid) valves close
    • Heard at the 5th intercostal space at the midclavicular line
    • Signals the beginning of systole
    • Often referred to as “lub”
  • S2
    • Normal heart sound
    • Second heart sound when semilunar (aortic and pulmonary) valves close
    • Heard at the base - 2nd intercostal space at the right sternal border (aortic) and left sternal border (pulmonic)
    • Physiologic splitting of S2 into its aortic and pulmonic parts is best heard with the diaphragm at the pulmonic area (2nd left intercostal space) and widens with inspiration
    • Signals the beginning of diastole
    • Often referred to as “dub”

S3 can be a normal finding in children, but in adults both S3 and S4 are adventitious (abnormal) sounds that should be reported to the supervising therapist. Both are best heard with the bell at the apex (5th intercostal space, midclavicular line) with the patient in left side-lying (left lateral decubitus) position; a right-sided S3 or S4 is heard at the lower left sternal border instead. The table below compares their timing, mechanism, and associated conditions.

The following table compares the S3 and S4 heart sounds by timing, mechanism, and associated conditions.


Heart sound Timing Mechanism Associated conditions
S3 Early diastole, just after S2 Rapid filling of the ventricles Fluid overload, weakened left ventricle, heart failure, myocardial infarction, dilated cardiomyopathy, valvular regurgitation, constrictive pericarditis
S4 Late diastole, just before S1 Reduced ventricular compliance or increased resistance to ventricular filling Left ventricular hypertrophy, left-sided heart failure

Murmurs are loudest over the valve involved: aortic stenosis at the 2nd right intercostal space, pulmonic stenosis at the 2nd left intercostal space, tricuspid regurgitation at the lower left sternal border, and mitral regurgitation at the apex.

Pulmonary findings - breath sounds, SpO2, bronchodilators - are covered next, in Anatomy, ventilation, and pulmonary function tests.

Exercise test types

  • 6-minute walk test: submaximal, self-paced distance test (healthy adults 40-80: median ~490-580 m); Phase I/II rehab; good for lower-level patients
  • Graded exercise test (treadmill): maximal effort, varies incline/grade; Phase II; most accurate tolerance measure, yields max HR for target range
  • Cycle ergometer test: submaximal, estimates VO₂ max; Phase II; used when patient can’t tolerate maximal testing
  • Key terms: maximal vs. submaximal test, VO₂ max (direct in maximal testing, estimated in submaximal)

Normal vs. abnormal exercise response & target heart rate

  • Normal: HR and systolic BP rise with workload; diastolic BP changes ≤~10 mmHg
  • Abnormal: HR fails to rise/rises excessively; systolic BP fails to rise or drops; diastolic BP shifts >10 mmHg
  • Age-predicted max HR: 220−age
  • Karvonen formula: target HR=((HRmax​−HRrest​)×%intensity)+HRrest​ (intensity multiplies HRR, not HR_max)
  • Borg RPE scale: 6–20, moderate training ~11–14; used instead of HR target for beta-blocker patients

Contraindications & reasons to stop testing

  • Absolute contraindications: unstable angina, MI within 2 days, uncontrolled symptomatic arrhythmia, acute/decompensated CHF
  • Relative contraindications: resting SBP >200 or DBP >110, severe anemia (Hgb <8 g/dL), advanced/complicated pregnancy
  • Stop signs: ST depression ≥2mm, cardiac arrest, new 2nd/3rd degree block, patient request, severe chest pain/dizziness/dyspnea, SBP drop >10 mmHg with increasing workload, ataxia, SBP >250 or DBP >115
  • PTA role: collect data, recognize/report changes, activate emergency response if needed; PT interprets and modifies plan of care

Cardiac medications & exercise implications

  • Beta blockers (atenolol): blunt HR response → use RPE, not HR, to gauge intensity
  • Calcium channel blockers: vasodilation ± HR slowing (non-dihydropyridines) vs. reflex tachycardia (dihydropyridines); watch orthostatic hypotension
  • ACE inhibitors: vasodilation → orthostatic hypotension, dizziness, dry cough
  • Diuretics (furosemide, HCTZ): electrolyte imbalance, orthostatic hypotension, muscle cramps, increased urination
  • Anticoagulants (warfarin): bleeding/bruising risk
  • Nitroglycerin: vasodilation, preload reduction; watch dizziness, headache, orthostatic hypotension; have available for angina, stop activity for chest pain, escalate if unrelieved
  • Digoxin: ↑contractility, ↓HR via AV node; monitor for toxicity (nausea, visual changes, dysrhythmias), especially with renal impairment
  • Statins: muscle pain/weakness, GI effects, headache
  • Amiodarone: watch for bradycardia, hypotension, pulmonary toxicity (cough/dyspnea), worsening heart failure signs

Post-cardiac-surgery precautions

  • Sternal precautions (post-CABG/sternotomy): limit lifting/pushing/pulling to ~5-10 lbs, avoid overhead reach or arms behind back, use pillow splinting; lasts 6-8 weeks or per surgeon
  • Pacemaker/ICD precautions: avoid overhead/behind-back movement and resisted upper-body exercise on implant side; lasts 4-6 weeks or per cardiology protocol

Bedside observational findings

  • Pulse grading: 0 (absent) to 4+ (bounding), with 3+ typically normal (confirm facility’s scale convention)
  • Pitting edema grading: Grade 1 (0-2mm, immediate rebound) to Grade 4 (>6mm, typically ~8mm; rebound ≥60 sec); linked to right-sided heart failure
  • Heart sounds: S1 (“lub,” AV valve closure, systole onset) and S2 (“dub,” semilunar valve closure, diastole onset) are normal; physiologic S2 split best heard at the pulmonic area (2nd left ICS), widens with inspiration; murmurs: aortic stenosis R 2nd ICS, pulmonic stenosis L 2nd ICS, tricuspid regurgitation lower left sternal border, mitral regurgitation apex
  • S3/S4 are abnormal in adults (S3 normal in children): S3 = early diastole/rapid filling (fluid overload, HF, MI); S4 = late diastole/reduced compliance (LV hypertrophy, left HF); best heard with bell at apex, left side-lying

Sign up for free to take 28 quiz questions on this topic

Previous
Next  | 2.1 Anatomy, ventilation, and pulmonary function tests
All rights reserved ©2016 - 2026 Achievable, Inc.

Cardiac exercise testing

This page covers the cardiac data a PTA gathers around an exercise session: test types, when testing is unsafe or must stop, how medications change the exercise response, and bedside findings like pulse, edema, and heart sounds.

Types of test

Each test below estimates cardiovascular capacity, but they differ in how close they push the patient toward maximal effort and in the setting where they’re used.

  • 6-minute walk test
    • Test goal: measure distance walked in 6 minutes with or without an assistive device; a self-paced, submaximal test. Healthy adults aged 40-80 walk a median of about 490-580 m, so a much shorter distance signals reduced functional capacity
    • Rationale: test for endurance related to cardiovascular health
    • Setting used: Phase I and Phase II of cardiac rehabilitation
    • Test advantages: Quick assessment of endurance that can be completed for lower-level patients
  • Graded exercise testing
    • Test goal: assess the maximal workload that can be applied to the cardiovascular system via treadmill testing at different grades (incline)
    • Rationale: provide the therapist with information on the highest capacity of exercise tolerance
      • Provides the maximal heart rate that can be used to then give the target heart range with activity
    • Setting: Phase II cardiac rehabilitation
    • Test advantages: Most accurate assessment tool of an individual’s exercise tolerance
  • Cycle ergometer test
    • Test goal: A submaximal graded exercise test used to estimate VO₂ max and assess cardiovascular endurance by progressively increasing cycling resistance/workload.
    • Rationale: the estimated VO₂ max is a useful indicator of cardiovascular fitness and aerobic endurance without requiring a maximal effort.
    • Setting: Phase II cardiac rehabilitation
    • Test advantage: Utilized over maximal exercise testing if the patient is unable to tolerate maximal testing parameters
Definitions
Maximal exercise test
Exercise testing that progresses to the highest workload, intensity, and duration the individual can tolerate.
Submaximal exercise test
An exercise assessment performed below the individual’s maximal effort level, terminated at a predetermined threshold (such as target heart rate, symptoms, blood pressure response, RPE, or ECG changes) to estimate cardiovascular fitness and exercise tolerance safely.
VO2 max
Maximum rate at which the body can take up and use oxygen during exercise. It is measured directly during maximal exercise testing and estimated from heart rate and workload during submaximal testing.

Normal vs. abnormal exercise response

The following table compares how heart rate, systolic blood pressure, and diastolic blood pressure normally respond to increasing exercise workload, versus signs of an abnormal response.


Vital sign Normal response Abnormal response
Heart rate Rises roughly in proportion to workload Fails to rise, or rises excessively for the workload
Systolic BP Rises with workload Fails to rise, or drops as workload increases
Diastolic BP Stays about the same or changes by roughly ±10 mmHg Rises or falls by more than that

Age-predicted max HR is 220−age; the Karvonen formula sets a target range from it: target HR=((HRmax​−HRrest​)×%intensity)+HRrest​.

Example: Karvonen target heart rate range

A 60-year-old patient has a resting heart rate of 70 bpm, and the supervising PT wants to train at 60-80% intensity. What’s the target heart rate range?

  • Estimate max HR: 220−60=160 bpm
  • Find heart rate reserve (HRR): 160−70=90 bpm
  • Lower bound: (90×0.60)+70=124 bpm
  • Upper bound: (90×0.80)+70=142 bpm

Answer: The target heart rate range is 124-142 bpm. Notice that %intensity multiplies the heart rate reserve (HR_max minus HR_rest), not HR_max directly - and HR_rest gets added back in at the end. For a patient on a beta blocker, heart rate doesn’t rise predictably with workload, so RPE replaces this target.

The Borg RPE scale runs 6-20, with moderate training typically around 11-14.

Contraindications for exercise testing

Absolute contraindications mean the test should not proceed; relative ones call for weighing risk against benefit.

Absolute:

  • Unstable angina
  • Acute myocardial infarction (within 2 days)
  • Uncontrolled symptomatic arrhythmia
  • Acute or decompensated congestive heart failure

Relative:

  • Resting systolic blood pressure >200 mmHg or diastolic >110 mmHg
  • Severe anemia (hemoglobin less than 8 g/dL) - see Lab values and ankle brachial index for other lab thresholds affecting activity
  • Advanced or complicated pregnancy

Reasons to stop exercise testing

Any sign below means stopping the test immediately and notifying the supervising PT.

  • Severe ST-segment depression of 2mm or greater
  • Cardiac arrest
  • Development of new 2nd or 3rd degree heart block
  • Patient requests to stop
  • Severe chest pain, dizziness, or dyspnea
  • Fall (drop) in systolic blood pressure of more than 10 mmHg despite increasing workload
  • Ataxia
  • Rise in systolic blood pressure >250 mmHg or diastolic >115 mmHg

PTA scope of practice: The PTA collects data and recognizes and communicates changes in a patient’s status to the supervising PT; evaluating the patient, interpreting findings, and changing the plan of care remain the PT’s responsibility. The same signs apply during any exercise session: when one appears, or a patient shows an adverse response to a medication listed below, the PTA stops the activity, activates emergency response when the sign calls for it, and reports it to the supervising PT, who decides whether and how the plan of care continues. Supervision and delegation rules are covered in PTA responsibilities, research, and ADA.

Cardiac medications

Each medication below changes how the body responds to exercise - knowing the mechanism helps you interpret vital signs correctly during a session.

  • Beta blockers (atenolol): hypertension medication
    • Mechanism of action: works on the heart muscle by blocking epinephrine; decreased heart rate
    • PT implications: do not use heart rate as an indicator for response to exercise; use the perceived exertion scale (RPE) to assist with tolerance to activity
  • Calcium channel blockers: hypertension medication
    • Mechanism of action: blocks calcium from entering vascular smooth muscle and heart muscle cells, causing vasodilation; non-dihydropyridine CCBs (diltiazem, verapamil) also slow heart rate, while dihydropyridine CCBs (amlodipine, nifedipine) act mainly on blood vessels and can cause a reflex increase in heart rate
    • PT implications: orthostatic hypotension
  • Angiotensin converting enzyme inhibitors (ACE inhibitors): hypertension medications
    • Mechanism of action: blocks the conversion of angiotensin I to angiotensin II, reducing vasoconstriction and causing peripheral vasodilation
    • PT implications: orthostatic hypotension, dizziness, palpitations, and a persistent dry cough
  • Diuretics (Lasix [furosemide], hydrochlorothiazide): hypertension medication
    • Mechanism of action: works on the kidneys to decrease the fluid retention in the body by moving sodium out of the body
    • PT implications: electrolyte imbalance (which can trigger dysrhythmias or palpitations), orthostatic hypotension and dizziness, muscle cramps, increased urination
  • Anticoagulants (e.g., warfarin [Coumadin]): decreases clotting of blood
    • Mechanism of action: works to reduce the clotting within the blood
    • PT implications: hemorrhage risk, can easily bruise
  • Antiplatelet drugs (aspirin, clopidogrel): keep platelets from clumping together to form clots, lowering the risk of heart attack and stroke
    • PT implications: bruise and bleed more easily; they do not slow heart rate, raise blood pressure, or treat orthostatic hypotension
  • Nitroglycerin: used specifically for angina pectoris
    • Mechanism of action: relaxes vascular smooth muscle (predominantly veins), releasing nitric oxide, which causes vasodilation, reduces cardiac preload, and lowers blood pressure
    • PT implications: dizziness, headache, weakness, nausea, and orthostatic hypotension. Patients with angina should have their nitroglycerin available during exercise. If chest pain occurs, stop the activity, have the patient sit, and follow the facility protocol; chest pain that isn’t relieved calls for emergency response and a report to the PT.
  • Digitalis (digoxin): medication commonly used to treat heart failure and certain atrial dysrhythmias.
    • Mechanism of action: increases the force of myocardial contraction (positive inotropic effect) and slows conduction through the AV node, which helps decrease heart rate.
    • PT implications: monitor heart rate, rhythm, blood pressure, and signs of digoxin toxicity. Patients with renal impairment are at increased risk for digoxin toxicity because digoxin is primarily excreted by the kidneys. Toxicity may lead to nausea, vomiting, visual disturbances, dysrhythmias, dizziness, and possible hospitalization.
  • Antihyperlipidemics (statins): cholesterol medication
    • Mechanism of action: blocks the production of cholesterol by the liver
    • PT implications: muscle pain, muscle weakness, fatigue, diarrhea, constipation, headache
  • Amiodarone (antiarrhythmic agent): unstable ventricular tachycardia and recurrent ventricular fibrillation medication
    • Mechanism of action: increases the duration of the action potential as well as the effective refractory period for cardiac cells
    • PT implications: monitor for bradycardia and hypotension; new cough or dyspnea may signal pulmonary toxicity; watch for worsening heart failure signs (edema, crackles, JVD)

Post-cardiac-surgery precautions

Two common postoperative precautions affect how a PTA progresses activity after cardiac surgery or device implantation:

  • Sternal precautions (after CABG or sternotomy): avoid lifting, pushing, or pulling more than about 5-10 lbs; avoid reaching behind the back or raising the elbows above shoulder height; have the patient hug a pillow against the chest for coughing or transfers. These precautions typically last 6-8 weeks, or per the surgeon’s protocol.
  • Pacemaker/ICD precautions: on the side of the implant, avoid raising the arm above shoulder height or forceful overhead/behind-the-back movement, and avoid heavy lifting or resisted upper-body exercise, for about 4-6 weeks or until the device site has healed, per the cardiology team’s protocol.

Observational cardiac topics

Beyond formal testing, a PTA also gathers bedside findings - pulse, edema, and heart sounds - that add to the clinical picture.

Pulse amplitude grading

  • 0: Absent - No pulse is palpable, even with maximum pressure. (Requires immediate medical evaluation).
  • 1+: Thready or weak - Barely perceptible; it fades in and out and can be easily obliterated with slight pressure.
  • 2+: Diminished - Easily palpable but weaker than a normal, expected pulse.
  • 3+: Normal - Easily felt, full, and requires moderate pressure to obliterate.
  • 4+: Bounding - Very strong and hyperactive; it does not disappear even with moderate to firm pressure

Some sources use a different convention where 2+ is normal and 3+ is increased (fuller than normal), so confirm which scale a facility or question is using before interpreting a grade.

Pitting edema grading (associated with right-sided heart failure):

  • Grade 1: 0-2 mm indentation and rebounds immediately
  • Grade 2: 3-4 mm indentation and rebounds within 15 seconds
  • Grade 3: 5-6 mm indentation and rebounds within 30-60 seconds
  • Grade 4: deeper than 6 mm (typically about 8 mm) indentation and rebounds 60 seconds or longer

Pitting edema leaves a temporary indentation when pressed; non-pitting edema, such as angioedema or advanced lymphedema, leaves no lasting indentation.

Auscultation of heart sounds

  • S1:
    • Normal heart sound
    • First heart sound when atrioventricular (mitral and tricuspid) valves close
    • Heard at the 5th intercostal space at the midclavicular line
    • Signals the beginning of systole
    • Often referred to as “lub”
  • S2
    • Normal heart sound
    • Second heart sound when semilunar (aortic and pulmonary) valves close
    • Heard at the base - 2nd intercostal space at the right sternal border (aortic) and left sternal border (pulmonic)
    • Physiologic splitting of S2 into its aortic and pulmonic parts is best heard with the diaphragm at the pulmonic area (2nd left intercostal space) and widens with inspiration
    • Signals the beginning of diastole
    • Often referred to as “dub”

S3 can be a normal finding in children, but in adults both S3 and S4 are adventitious (abnormal) sounds that should be reported to the supervising therapist. Both are best heard with the bell at the apex (5th intercostal space, midclavicular line) with the patient in left side-lying (left lateral decubitus) position; a right-sided S3 or S4 is heard at the lower left sternal border instead. The table below compares their timing, mechanism, and associated conditions.

The following table compares the S3 and S4 heart sounds by timing, mechanism, and associated conditions.


Heart sound Timing Mechanism Associated conditions
S3 Early diastole, just after S2 Rapid filling of the ventricles Fluid overload, weakened left ventricle, heart failure, myocardial infarction, dilated cardiomyopathy, valvular regurgitation, constrictive pericarditis
S4 Late diastole, just before S1 Reduced ventricular compliance or increased resistance to ventricular filling Left ventricular hypertrophy, left-sided heart failure

Murmurs are loudest over the valve involved: aortic stenosis at the 2nd right intercostal space, pulmonic stenosis at the 2nd left intercostal space, tricuspid regurgitation at the lower left sternal border, and mitral regurgitation at the apex.

Pulmonary findings - breath sounds, SpO2, bronchodilators - are covered next, in Anatomy, ventilation, and pulmonary function tests.

Key points

Exercise test types

  • 6-minute walk test: submaximal, self-paced distance test (healthy adults 40-80: median ~490-580 m); Phase I/II rehab; good for lower-level patients
  • Graded exercise test (treadmill): maximal effort, varies incline/grade; Phase II; most accurate tolerance measure, yields max HR for target range
  • Cycle ergometer test: submaximal, estimates VO₂ max; Phase II; used when patient can’t tolerate maximal testing
  • Key terms: maximal vs. submaximal test, VO₂ max (direct in maximal testing, estimated in submaximal)

Normal vs. abnormal exercise response & target heart rate

  • Normal: HR and systolic BP rise with workload; diastolic BP changes ≤~10 mmHg
  • Abnormal: HR fails to rise/rises excessively; systolic BP fails to rise or drops; diastolic BP shifts >10 mmHg
  • Age-predicted max HR: 220−age
  • Karvonen formula: target HR=((HRmax​−HRrest​)×%intensity)+HRrest​ (intensity multiplies HRR, not HR_max)
  • Borg RPE scale: 6–20, moderate training ~11–14; used instead of HR target for beta-blocker patients

Contraindications & reasons to stop testing

  • Absolute contraindications: unstable angina, MI within 2 days, uncontrolled symptomatic arrhythmia, acute/decompensated CHF
  • Relative contraindications: resting SBP >200 or DBP >110, severe anemia (Hgb <8 g/dL), advanced/complicated pregnancy
  • Stop signs: ST depression ≥2mm, cardiac arrest, new 2nd/3rd degree block, patient request, severe chest pain/dizziness/dyspnea, SBP drop >10 mmHg with increasing workload, ataxia, SBP >250 or DBP >115
  • PTA role: collect data, recognize/report changes, activate emergency response if needed; PT interprets and modifies plan of care

Cardiac medications & exercise implications

  • Beta blockers (atenolol): blunt HR response → use RPE, not HR, to gauge intensity
  • Calcium channel blockers: vasodilation ± HR slowing (non-dihydropyridines) vs. reflex tachycardia (dihydropyridines); watch orthostatic hypotension
  • ACE inhibitors: vasodilation → orthostatic hypotension, dizziness, dry cough
  • Diuretics (furosemide, HCTZ): electrolyte imbalance, orthostatic hypotension, muscle cramps, increased urination
  • Anticoagulants (warfarin): bleeding/bruising risk
  • Nitroglycerin: vasodilation, preload reduction; watch dizziness, headache, orthostatic hypotension; have available for angina, stop activity for chest pain, escalate if unrelieved
  • Digoxin: ↑contractility, ↓HR via AV node; monitor for toxicity (nausea, visual changes, dysrhythmias), especially with renal impairment
  • Statins: muscle pain/weakness, GI effects, headache
  • Amiodarone: watch for bradycardia, hypotension, pulmonary toxicity (cough/dyspnea), worsening heart failure signs

Post-cardiac-surgery precautions

  • Sternal precautions (post-CABG/sternotomy): limit lifting/pushing/pulling to ~5-10 lbs, avoid overhead reach or arms behind back, use pillow splinting; lasts 6-8 weeks or per surgeon
  • Pacemaker/ICD precautions: avoid overhead/behind-back movement and resisted upper-body exercise on implant side; lasts 4-6 weeks or per cardiology protocol

Bedside observational findings

  • Pulse grading: 0 (absent) to 4+ (bounding), with 3+ typically normal (confirm facility’s scale convention)
  • Pitting edema grading: Grade 1 (0-2mm, immediate rebound) to Grade 4 (>6mm, typically ~8mm; rebound ≥60 sec); linked to right-sided heart failure
  • Heart sounds: S1 (“lub,” AV valve closure, systole onset) and S2 (“dub,” semilunar valve closure, diastole onset) are normal; physiologic S2 split best heard at the pulmonic area (2nd left ICS), widens with inspiration; murmurs: aortic stenosis R 2nd ICS, pulmonic stenosis L 2nd ICS, tricuspid regurgitation lower left sternal border, mitral regurgitation apex
  • S3/S4 are abnormal in adults (S3 normal in children): S3 = early diastole/rapid filling (fluid overload, HF, MI); S4 = late diastole/reduced compliance (LV hypertrophy, left HF); best heard with bell at apex, left side-lying

More from Cardiovascular system

  • Physiology of cardiac system
  • Cardiac pathologies
  • Cardiac rehabilitation
  • Electrocardiograms
  • Lab values and ankle brachial index