


This browser is too old to run Achievable.

Update it, or open this page in a current version of Chrome, Safari, Firefox or Edge. On an iPhone or iPad, update iOS: every browser there runs on the version of Safari that comes with it.

Achievable logoAchievable logo
NPTE-PTA
Sign in
Sign up
Purchase
Textbook
Practice exams
Support
How it works
Resources
Exam catalog
Mountain with a flag at the peak
Textbook
Introduction
1. Cardiovascular system
1.1 Physiology of cardiac system
1.2 Cardiac pathologies
1.3 Cardiac rehabilitation
1.4 Electrocardiograms
1.5 Lab values and ankle brachial index
1.6 Cardiac exercise testing
2. Pulmonary system
3. Neuromuscular system
4. Pediatrics
5. Musculoskeletal system
6. Other systems
7. Non-systems
Wrapping up
Achievable logoAchievable logo
1.4 Electrocardiograms
Achievable NPTE-PTA
1. Cardiovascular system

Electrocardiograms

10 min read
Font
Discuss
Share
Feedback

How to read electrocardiograms

Sinus rhythm
Sinus rhythm
Anatomy & Physiology by Lindsay M. Biga, Sierra Dawson, Amy Harwell, Robin Hopkins, Joel Kaufmann, Mike LeMaster, Philip Matern, Katie Morrison-Graham, Devon Quick & Jon Runyeon
/
Oregon State University
/
CC BY 4.0
Definitions
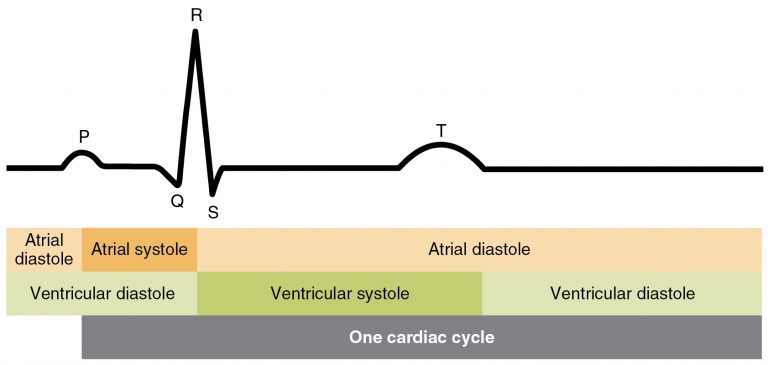
P wave
Atrial depolarization (precedes atrial contraction).
PR interval
The time required for the electrical impulse to travel from the sinoatrial (SA) node through the atria and AV node to the ventricles. Normal duration is 0.12-0.20 seconds (3-5 small boxes).
QRS complex
Ventricular depolarization (precedes ventricular contraction). Normal duration is under 0.12 seconds (fewer than 3 small boxes).
T wave
Ventricular repolarization/relaxation.

Important considerations for reading electrocardiograms

  1. Is the rhythm regular and consistent?
  2. Is the rate fast, slow, or normal?
  3. Are P waves present and look the same?
  4. Is the PR interval normal and consistent?
  5. Are the QRS complexes normal and immediately follow the P wave?
  6. Is the T wave present and normal in appearance?

Multi-lead strips: when viewing a multi-lead strip, use lead II or whichever lead shows the pattern most clearly.

Inverted waveforms: when a lead that is normally upright shows its P waves, QRS complexes, and T waves all inverted (lead I when the arm electrodes are swapped, for example), the cause is usually improper lead placement, not a heart problem. Have the electrodes checked and focus on the pattern listed above in 1-6. Some leads, such as aVR, are normally inverted, while a newly inverted T wave on its own can be a sign of ischemia and should be reported to the supervising PT.

Calculation of heart rate with EKG

Calculations as follows for a 6-second strip method:

The 6-second method works for both regular and irregular rhythms (such as atrial fibrillation), because it averages beats across the strip. It’s the go-to method when the rhythm is irregular.

Count the number of QRS complexes in 6 seconds and multiply by 10

Example:

7 QRS peaks noted in 6 seconds x 10 = 70 bpm (heart rate). This is in the normal range of 60-100.

Common EKGs

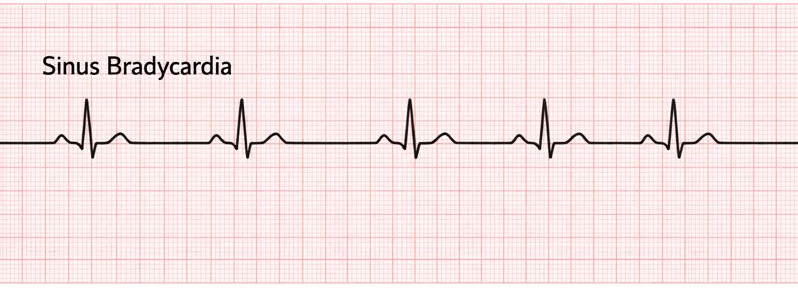
Sinus bradycardia (slow heart rate, below 60 beats per minute at rest)

Sinus bradycardia
Sinus bradycardia
Achievable

PT implications

  • Common to see this rhythm in well-conditioned athletes, in those taking beta-blockers, and in the elderly population
  • If present and the patient has no symptoms, it is generally OK to start or continue activity:
    • Will need to use the perceived exertion scale (RPE) to assess tolerance to activity, since beta-blockers blunt the normal heart rate response to exertion
    • Monitor for symptoms of dizziness, lightheadedness, and pallor
    • If these symptoms develop, or heart rate fails to rise (or drops) with increasing activity, stop the activity, recheck vitals, and notify the supervising PT

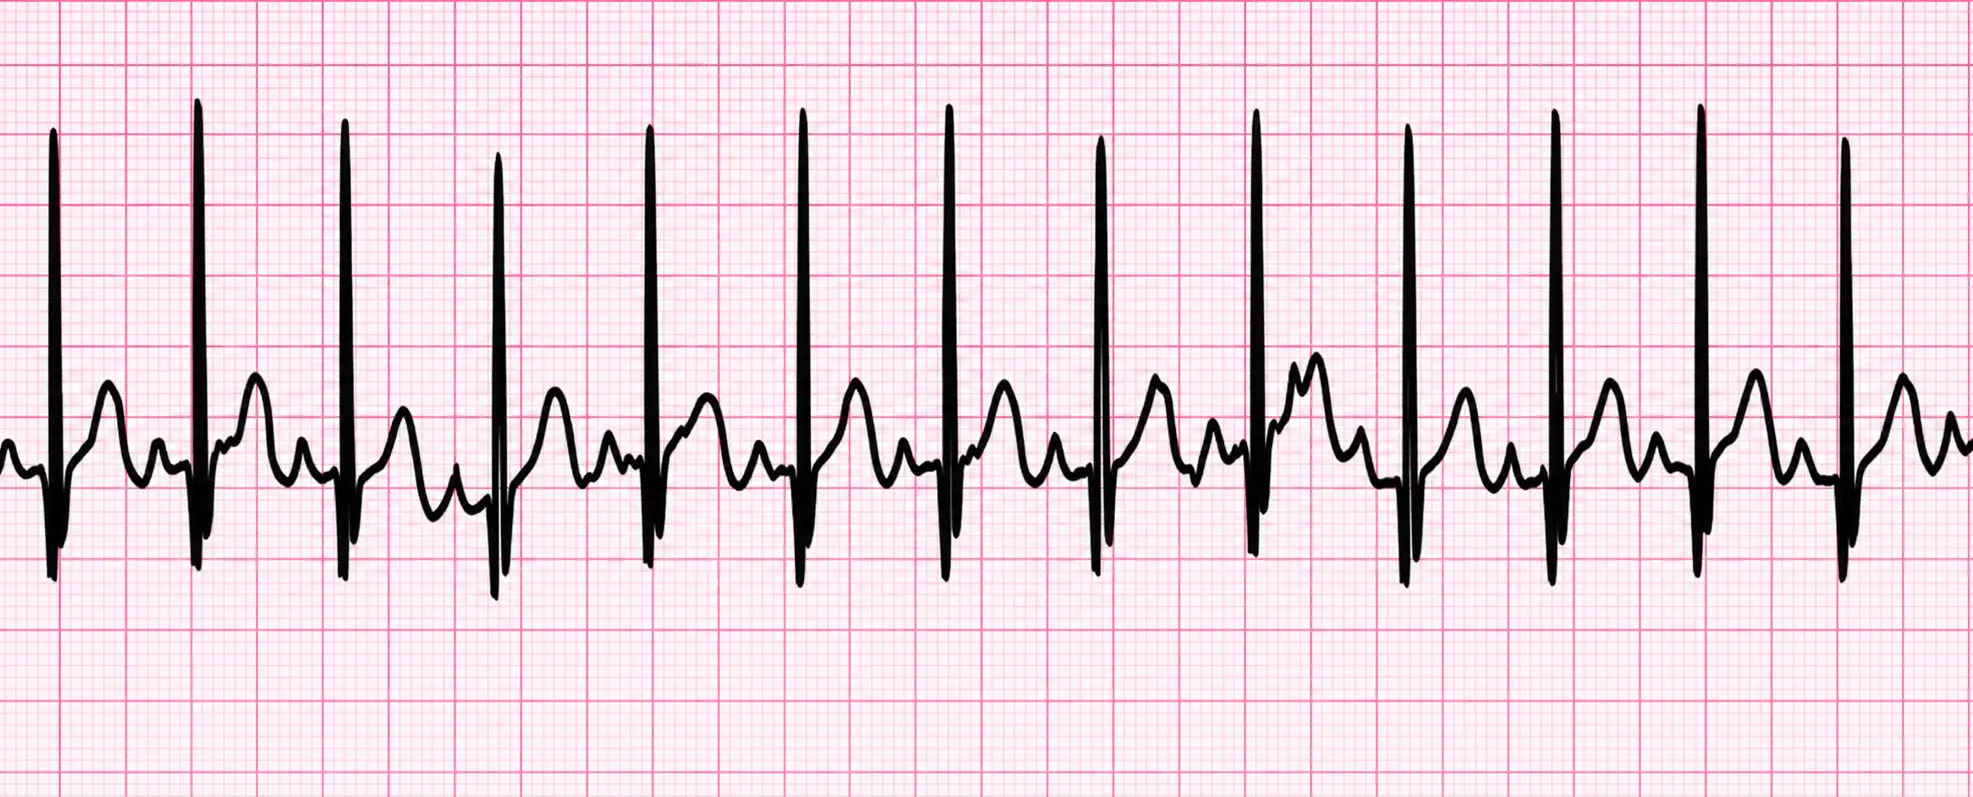
Sinus tachycardia (fast heart rate, > 100 beats per minute at rest)

ECG strip showing sinus tachycardia
Sinus tachycardia
Achievable

PT implications

  • Common to observe this rhythm during exercise
  • If present before exercise notify supervising PT
  • Pay attention if the individual develops a headache, dizziness, or lightheadedness with tachycardia
    • If these symptoms develop, stop the activity, recheck all vital signs, and notify the supervising PT

A-fibrillation (A-fib)

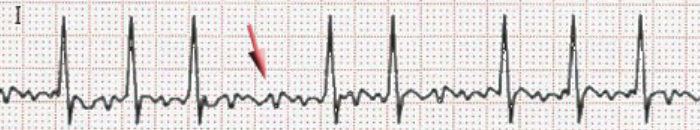
An irregularly irregular rhythm in which the atria quiver erratically; the ventricular rate may be normal or rapid. On the EKG, discrete P waves are absent and are replaced by chaotic fibrillatory (f) waves.

Atrial fibrillation
Atrial fibrillation
J. Heuser
/
Wikimedia Commons
/
CC BY-SA 3.0

PT implications

If not previously recognized, stop activity and notify

If identified previously:

  • Use ECG or auscultation rather than the radial pulse alone, since the rate may be irregular; monitor heart rate, blood pressure, and oxygen saturation closely.
  • Use rate of perceived exertion (RPE) rather than heart rate alone, and start with low to moderate intensity, avoiding high-intensity or sudden exertion early in rehab.
  • Stop signs: dizziness, fatigue, palpitations, chest pain, or dyspnea.

A-flutter

A regular, tachycardic contraction of the atrium; constant atrial contraction produces a sawtooth pattern of flutter (F) waves in place of P waves.

Atrial flutter
Atrial flutter
James Heilman, This file was derived from: Atrial flutter34.JPG
/
Wikimedia Commons
/
CC BY-SA 3.0

PT implications

If not previously recognized, stop activity and notify

If identified previously, follow the same vital sign monitoring and exercise progression guidance as atrial fibrillation (above), with these flutter-specific notes:

  • A-flutter typically presents with a regular but rapid atrial rate (240-400 bpm); ventricular response may be regular or irregular depending on AV block.
  • Patients may suddenly shift into more dangerous rhythms (e.g., atrial fibrillation or rapid ventricular response), so use ECG or telemetry when possible, especially in acute care settings.

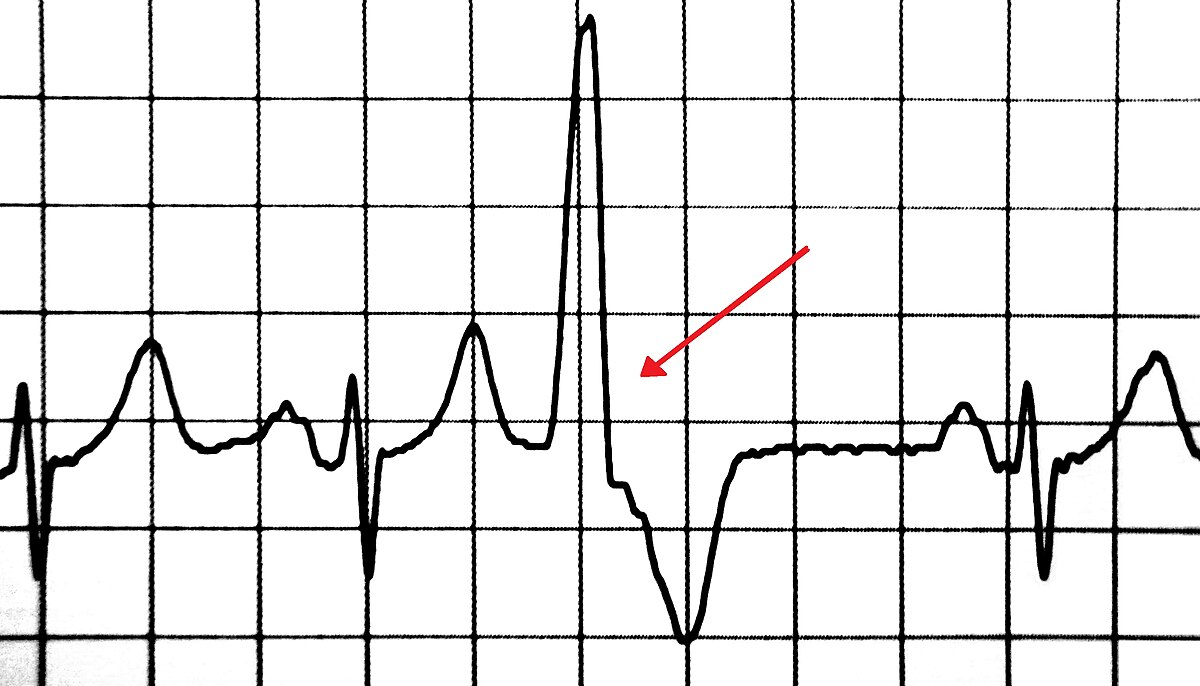
Premature ventricular contraction (PVC)

An early, wide, bizarre QRS complex from an ectopic ventricular focus, occurring before the next expected sinus beat and typically followed by a compensatory pause.

Premature ventricular contraction (PVC)
James Heilman
/
Wikimedia Commons
/
CC BY-SA 3.0

PT implications

  • Singular PVC at rest and exercise (no restriction): initiate or continue with activity, as this can be an anomaly
    • Can be caused by stress, caffeine, or idiopathic causes
  • Couplet (2) (precaution): stop and rest for 5 minutes; resume exercise only if resolved
  • Three or more PVCs in a row at rest or with exercise (contraindication): do not initiate activity and discontinue exercise, as this could lead to fatal heart rhythms
  • Bigeminy - a PVC every other heartbeat (contraindication): do not initiate activity and discontinue exercise, as this could lead to fatal heart rhythms
    • Monitor for symptoms: heart fluttering, heart pounding, missed heartbeats

Ventricular tachycardia

A rapid heart rhythm originating from the ventricles. The ventricles contract at a fast rate and may not fill effectively, which can significantly reduce cardiac output and impair blood flow to the body.

Ventricular tachycardia
Glenlarson
/
Wikimedia Commons
/
Public domain

PT implications

  • Medical emergency: stop activity immediately, activate emergency response, and check responsiveness and pulse.
  • If the patient is unresponsive and has no pulse or is not breathing normally (only gasping), begin CPR and apply the AED.

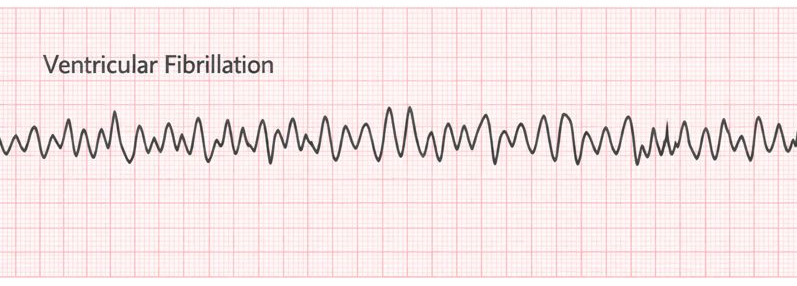
Ventricular fibrillation

Ventricular fibrillation is a life-threatening dysrhythmia characterized by rapid, chaotic electrical activity causing ineffective quivering of the ventricles. Because there is no coordinated ventricular contraction, the heart is unable to produce effective cardiac output or blood flow to the body.

Ventricular fibrillation
Achievable

PT implications

  • Medical emergency: activate emergency response, begin CPR, and apply the AED as soon as it’s available.

AV heart blocks

AV (atrioventricular) blocks are delays or interruptions in conduction from the atria to the ventricles, seen as changes to the PR interval or a mismatch between P waves and QRS complexes.

  • First-degree: PR interval is prolonged (over 0.20 seconds) but constant, and every P wave is followed by a QRS complex. Usually benign; continue activity and monitor.
  • Second-degree, type I (Wenckebach): the PR interval progressively lengthens until a QRS complex is dropped. Usually well tolerated; monitor symptoms and notify the supervising PT if new.
  • Second-degree, type II: PR interval stays constant but QRS complexes are intermittently dropped without warning. Higher risk of progressing to complete block; stop activity and notify the supervising PT.
  • Third-degree (complete): no relationship between P waves and QRS complexes; the ventricles beat independently at a slow rate. Medical emergency: stop activity and notify the supervising PT immediately.

EKG waveform basics

  • P wave = atrial depolarization; QRS complex = ventricular depolarization; T wave = ventricular repolarization
  • PR interval normal: 0.12-0.20 sec (3-5 small boxes); QRS normal: under 0.12 sec (<3 small boxes)
  • Reading checklist: rhythm regularity, rate, P wave presence/shape, PR interval consistency, QRS timing/shape, T wave appearance

Lead interpretation & rate calculation

  • Use lead II (or clearest lead) for multi-lead strips
  • Globally inverted waveforms usually indicate lead misplacement, not cardiac issue (aVR normally inverted); an isolated new inverted T wave may signal ischemia—report it
  • Heart rate via 6-second strip: count QRS complexes in 6 sec ×10; works for both regular and irregular rhythms (e.g., a-fib)

Sinus rate abnormalities (bradycardia/tachycardia)

  • Bradycardia (<60 bpm): common with beta-blockers/elderly; use RPE (not HR) to gauge exertion since beta-blockers blunt HR response; stop if dizziness/pallor or HR fails to rise
  • Tachycardia (>100 bpm): common during exercise; if present pre-exercise, notify PT; stop for headache/dizziness and recheck vitals

Atrial dysrhythmias (A-fib, A-flutter)

  • A-fib: irregularly irregular rhythm, no discrete P waves (chaotic f waves)
  • A-flutter: regular, rapid atrial rate (240-400 bpm), sawtooth F waves replacing P waves
  • Both: if newly identified, stop and notify; if known, monitor via ECG/auscultation (not radial pulse alone), use RPE, start low/moderate intensity, watch for dizziness/chest pain/dyspnea

Ventricular ectopy & tachyarrhythmias

  • PVC: early wide bizarre QRS with compensatory pause
    • Single PVC: no restriction
    • Couplet: precaution—stop, rest 5 min, resume only if resolved
    • 3+ in a row or bigeminy: contraindication—stop/do not initiate (risk of fatal rhythms)
  • Ventricular tachycardia & ventricular fibrillation: medical emergencies—stop activity, activate emergency response; V-tach: begin CPR/AED if unresponsive and pulseless or not breathing normally; V-fib: begin CPR and apply AED as soon as available

AV heart blocks

  • First-degree: prolonged but constant PR interval, every P wave followed by QRS—benign, continue/monitor
  • Second-degree Type I (Wenckebach): progressively lengthening PR until a dropped QRS—usually tolerated, monitor
  • Second-degree Type II: constant PR with unpredictable dropped QRS—higher risk, stop and notify PT
  • Third-degree (complete): no P-QRS relationship, independent slow ventricular rate—medical emergency, stop immediately and notify PT

Sign up for free to take 14 quiz questions on this topic

Previous
Next  | 1.5 Lab values and ankle brachial index
All rights reserved ©2016 - 2026 Achievable, Inc.

Electrocardiograms

How to read electrocardiograms

Definitions
P wave
Atrial depolarization (precedes atrial contraction).
PR interval
The time required for the electrical impulse to travel from the sinoatrial (SA) node through the atria and AV node to the ventricles. Normal duration is 0.12-0.20 seconds (3-5 small boxes).
QRS complex
Ventricular depolarization (precedes ventricular contraction). Normal duration is under 0.12 seconds (fewer than 3 small boxes).
T wave
Ventricular repolarization/relaxation.

Important considerations for reading electrocardiograms

  1. Is the rhythm regular and consistent?
  2. Is the rate fast, slow, or normal?
  3. Are P waves present and look the same?
  4. Is the PR interval normal and consistent?
  5. Are the QRS complexes normal and immediately follow the P wave?
  6. Is the T wave present and normal in appearance?

Multi-lead strips: when viewing a multi-lead strip, use lead II or whichever lead shows the pattern most clearly.

Inverted waveforms: when a lead that is normally upright shows its P waves, QRS complexes, and T waves all inverted (lead I when the arm electrodes are swapped, for example), the cause is usually improper lead placement, not a heart problem. Have the electrodes checked and focus on the pattern listed above in 1-6. Some leads, such as aVR, are normally inverted, while a newly inverted T wave on its own can be a sign of ischemia and should be reported to the supervising PT.

Calculation of heart rate with EKG

Calculations as follows for a 6-second strip method:

The 6-second method works for both regular and irregular rhythms (such as atrial fibrillation), because it averages beats across the strip. It’s the go-to method when the rhythm is irregular.

Count the number of QRS complexes in 6 seconds and multiply by 10

Example:

7 QRS peaks noted in 6 seconds x 10 = 70 bpm (heart rate). This is in the normal range of 60-100.

Common EKGs

Sinus bradycardia (slow heart rate, below 60 beats per minute at rest)

PT implications

  • Common to see this rhythm in well-conditioned athletes, in those taking beta-blockers, and in the elderly population
  • If present and the patient has no symptoms, it is generally OK to start or continue activity:
    • Will need to use the perceived exertion scale (RPE) to assess tolerance to activity, since beta-blockers blunt the normal heart rate response to exertion
    • Monitor for symptoms of dizziness, lightheadedness, and pallor
    • If these symptoms develop, or heart rate fails to rise (or drops) with increasing activity, stop the activity, recheck vitals, and notify the supervising PT

Sinus tachycardia (fast heart rate, > 100 beats per minute at rest)

PT implications

  • Common to observe this rhythm during exercise
  • If present before exercise notify supervising PT
  • Pay attention if the individual develops a headache, dizziness, or lightheadedness with tachycardia
    • If these symptoms develop, stop the activity, recheck all vital signs, and notify the supervising PT

A-fibrillation (A-fib)

An irregularly irregular rhythm in which the atria quiver erratically; the ventricular rate may be normal or rapid. On the EKG, discrete P waves are absent and are replaced by chaotic fibrillatory (f) waves.

PT implications

If not previously recognized, stop activity and notify

If identified previously:

  • Use ECG or auscultation rather than the radial pulse alone, since the rate may be irregular; monitor heart rate, blood pressure, and oxygen saturation closely.
  • Use rate of perceived exertion (RPE) rather than heart rate alone, and start with low to moderate intensity, avoiding high-intensity or sudden exertion early in rehab.
  • Stop signs: dizziness, fatigue, palpitations, chest pain, or dyspnea.

A-flutter

A regular, tachycardic contraction of the atrium; constant atrial contraction produces a sawtooth pattern of flutter (F) waves in place of P waves.

PT implications

If not previously recognized, stop activity and notify

If identified previously, follow the same vital sign monitoring and exercise progression guidance as atrial fibrillation (above), with these flutter-specific notes:

  • A-flutter typically presents with a regular but rapid atrial rate (240-400 bpm); ventricular response may be regular or irregular depending on AV block.
  • Patients may suddenly shift into more dangerous rhythms (e.g., atrial fibrillation or rapid ventricular response), so use ECG or telemetry when possible, especially in acute care settings.

Premature ventricular contraction (PVC)

An early, wide, bizarre QRS complex from an ectopic ventricular focus, occurring before the next expected sinus beat and typically followed by a compensatory pause.

PT implications

  • Singular PVC at rest and exercise (no restriction): initiate or continue with activity, as this can be an anomaly
    • Can be caused by stress, caffeine, or idiopathic causes
  • Couplet (2) (precaution): stop and rest for 5 minutes; resume exercise only if resolved
  • Three or more PVCs in a row at rest or with exercise (contraindication): do not initiate activity and discontinue exercise, as this could lead to fatal heart rhythms
  • Bigeminy - a PVC every other heartbeat (contraindication): do not initiate activity and discontinue exercise, as this could lead to fatal heart rhythms
    • Monitor for symptoms: heart fluttering, heart pounding, missed heartbeats

Ventricular tachycardia

A rapid heart rhythm originating from the ventricles. The ventricles contract at a fast rate and may not fill effectively, which can significantly reduce cardiac output and impair blood flow to the body.

PT implications

  • Medical emergency: stop activity immediately, activate emergency response, and check responsiveness and pulse.
  • If the patient is unresponsive and has no pulse or is not breathing normally (only gasping), begin CPR and apply the AED.

Ventricular fibrillation

Ventricular fibrillation is a life-threatening dysrhythmia characterized by rapid, chaotic electrical activity causing ineffective quivering of the ventricles. Because there is no coordinated ventricular contraction, the heart is unable to produce effective cardiac output or blood flow to the body.

PT implications

  • Medical emergency: activate emergency response, begin CPR, and apply the AED as soon as it’s available.

AV heart blocks

AV (atrioventricular) blocks are delays or interruptions in conduction from the atria to the ventricles, seen as changes to the PR interval or a mismatch between P waves and QRS complexes.

  • First-degree: PR interval is prolonged (over 0.20 seconds) but constant, and every P wave is followed by a QRS complex. Usually benign; continue activity and monitor.
  • Second-degree, type I (Wenckebach): the PR interval progressively lengthens until a QRS complex is dropped. Usually well tolerated; monitor symptoms and notify the supervising PT if new.
  • Second-degree, type II: PR interval stays constant but QRS complexes are intermittently dropped without warning. Higher risk of progressing to complete block; stop activity and notify the supervising PT.
  • Third-degree (complete): no relationship between P waves and QRS complexes; the ventricles beat independently at a slow rate. Medical emergency: stop activity and notify the supervising PT immediately.
Key points

EKG waveform basics

  • P wave = atrial depolarization; QRS complex = ventricular depolarization; T wave = ventricular repolarization
  • PR interval normal: 0.12-0.20 sec (3-5 small boxes); QRS normal: under 0.12 sec (<3 small boxes)
  • Reading checklist: rhythm regularity, rate, P wave presence/shape, PR interval consistency, QRS timing/shape, T wave appearance

Lead interpretation & rate calculation

  • Use lead II (or clearest lead) for multi-lead strips
  • Globally inverted waveforms usually indicate lead misplacement, not cardiac issue (aVR normally inverted); an isolated new inverted T wave may signal ischemia—report it
  • Heart rate via 6-second strip: count QRS complexes in 6 sec ×10; works for both regular and irregular rhythms (e.g., a-fib)

Sinus rate abnormalities (bradycardia/tachycardia)

  • Bradycardia (<60 bpm): common with beta-blockers/elderly; use RPE (not HR) to gauge exertion since beta-blockers blunt HR response; stop if dizziness/pallor or HR fails to rise
  • Tachycardia (>100 bpm): common during exercise; if present pre-exercise, notify PT; stop for headache/dizziness and recheck vitals

Atrial dysrhythmias (A-fib, A-flutter)

  • A-fib: irregularly irregular rhythm, no discrete P waves (chaotic f waves)
  • A-flutter: regular, rapid atrial rate (240-400 bpm), sawtooth F waves replacing P waves
  • Both: if newly identified, stop and notify; if known, monitor via ECG/auscultation (not radial pulse alone), use RPE, start low/moderate intensity, watch for dizziness/chest pain/dyspnea

Ventricular ectopy & tachyarrhythmias

  • PVC: early wide bizarre QRS with compensatory pause
    • Single PVC: no restriction
    • Couplet: precaution—stop, rest 5 min, resume only if resolved
    • 3+ in a row or bigeminy: contraindication—stop/do not initiate (risk of fatal rhythms)
  • Ventricular tachycardia & ventricular fibrillation: medical emergencies—stop activity, activate emergency response; V-tach: begin CPR/AED if unresponsive and pulseless or not breathing normally; V-fib: begin CPR and apply AED as soon as available

AV heart blocks

  • First-degree: prolonged but constant PR interval, every P wave followed by QRS—benign, continue/monitor
  • Second-degree Type I (Wenckebach): progressively lengthening PR until a dropped QRS—usually tolerated, monitor
  • Second-degree Type II: constant PR with unpredictable dropped QRS—higher risk, stop and notify PT
  • Third-degree (complete): no P-QRS relationship, independent slow ventricular rate—medical emergency, stop immediately and notify PT

More from Cardiovascular system

  • Physiology of cardiac system
  • Cardiac pathologies
  • Cardiac rehabilitation
  • Lab values and ankle brachial index
  • Cardiac exercise testing