




Scoliosis, autism, and birth injuries
These acquired pediatric conditions affect the spine, development, and the infant at birth; as with the hip and knee conditions, the PTA carries out the plan of care established by the supervising PT.
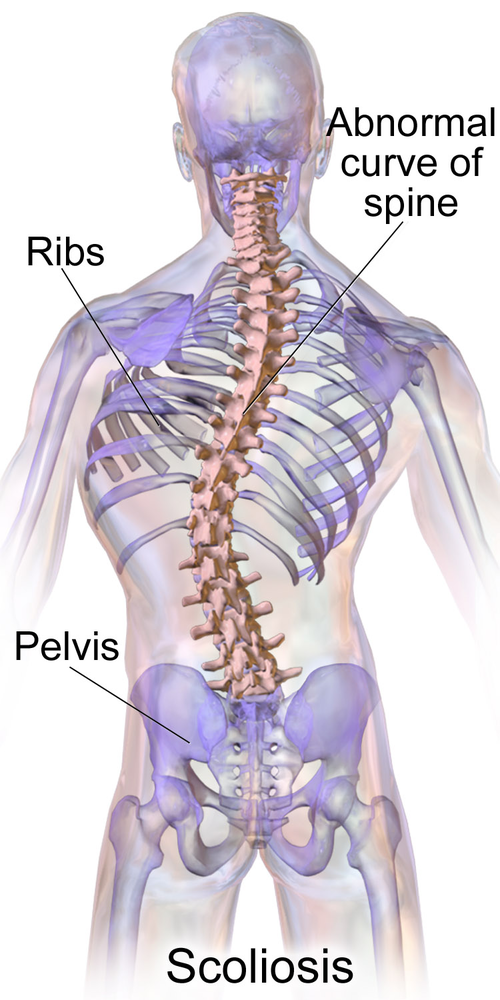
Scoliosis
Most idiopathic cases are diagnosed during adolescence. Diagnosis is confirmed through physical examination and X-ray imaging. The severity of scoliosis is defined by the degree of curve - this also guides which interventions may be performed.
Cobb angle (severity of scoliosis)
- Mild scoliosis: Cobb angle less than 20 degrees
- No intervention or conservative management
- Moderate scoliosis: Cobb angle between 20 and 40 degrees
- Bracing and physical therapy may be indicated
- Severe scoliosis: Cobb angle greater than 40 degrees
- Surgical intervention to correct the curve; large curves, generally greater than 50 degrees, can begin to compromise the respiratory system
Symptoms
- Uneven shoulders
- One shoulder blade that appears more prominent than the other
- Uneven waist
- One hip is higher than the other
- One side of the rib cage jutting forward
Physical therapy interventions for scoliosis
- Address muscle imbalances that may be present due to curvature, per the plan of care
- Apply and reinforce use of prescribed shoe inserts to correct leg length discrepancy
- Reinforce use of prescribed durable medical equipment and report changes in fit or tolerance to the supervising PT
Autism spectrum disorder
Etiology is unknown, but there is a strong genetic predisposition, along with some prenatal or perinatal environmental factors that may contribute. Diagnosis is made through observation, use of outcome measures, an interview with the parents and child, and diagnostic criteria. A reliable diagnosis can be made at age 2.
Symptoms
- Sensory integration dysfunction
- Hyposensitivity (sensory seeking) or hypersensitivity (sensory avoidant)
- Difficulty with verbal and non-verbal communication
- Impaired coordination
- Balance deficits
- Occasional strength and range of motion deficits
- Developmental delay
Physical therapy interventions for autism spectrum disorder
- Address developmental delay
- Improve strength
- Improve balance and coordination
- Sensory integration activities
- Be aware that new people and situations can cause either withdrawal behavior or increased aggression
Brachial plexus injuries
Common causes of brachial plexus injuries include breech birth (causing the use of assisted birth techniques such as forceps or vacuum), increased birth weight, multiple birth (twins or more), or gestational diabetes. Diagnosis is performed via physical examination (movement of the upper extremity and/or testing of primitive reflexes), x-ray, and MRI if needed.
Severity of brachial plexus injuries
- Traction
- Stretching of the nerve with spontaneous recovery
- Rupture
- Nerve is torn but remains attached to the spinal cord; may require surgical intervention
- Avulsion
- Nerve is completely torn from the spinal cord; permanent disability may result after surgical intervention
Common brachial plexus injuries
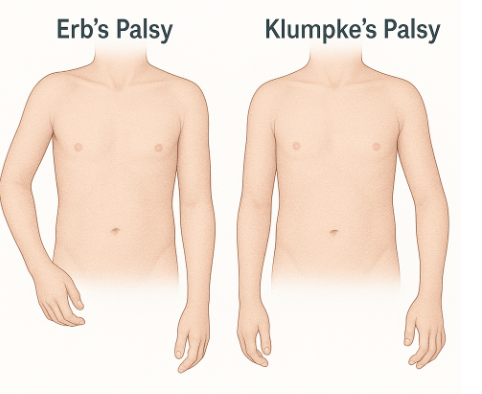
- Erb’s palsy
- Involves C5-C6 nerve roots - upper arm paralysis involving deltoid, supraspinatus, infraspinatus, biceps brachii, brachialis, and brachioradialis
- Immobility of the shoulder girdle leading to subluxation of the shoulder
- Only use of hand muscles
- Involves C5-C6 nerve roots - upper arm paralysis involving deltoid, supraspinatus, infraspinatus, biceps brachii, brachialis, and brachioradialis
- Klumpke’s palsy
- Involves C8-T1 nerve roots - lower arm paralysis involving intrinsic muscles of the hand, finger flexors, and finger extensors
- Contractures of the hand may result
- Functional use of the shoulder and elbow; deficits in the use of the wrist and hand
- Involves C8-T1 nerve roots - lower arm paralysis involving intrinsic muscles of the hand, finger flexors, and finger extensors
- Global palsy
- Involves C5-T1 - total arm paralysis
Physical therapy interventions for brachial plexus injuries
- Partial immobilization for 1-2 weeks of the injured extremity
- Constraint-induced therapy of the non-injured arm
- Range of motion to avoid contractures
- Age-appropriate movements to decrease the likelihood of developmental delay
- Parent education on positioning and handling of the infant
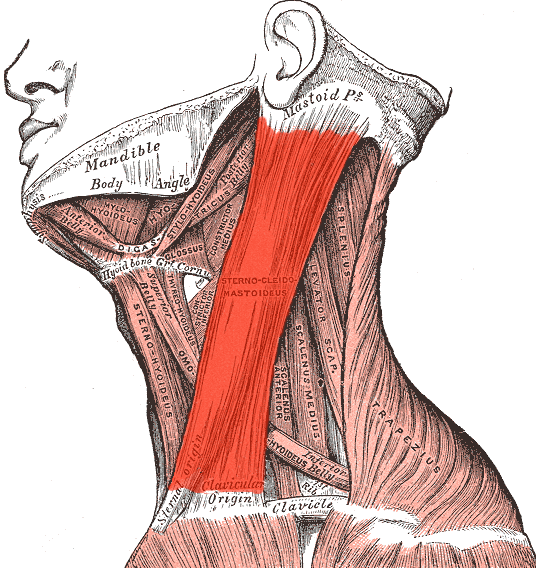
Torticollis
Torticollis can be caused by difficulties at birth, large infant weight, breech birth, or improper positioning after birth. Diagnosis is confirmed via physical examination.
Symptoms
- Persistent head tilt to one side
- Difficulty turning the head to the opposite side
- A lump or knot may be felt in the tight neck muscle
- Facial asymmetry may develop over time
- Flat head on the side opposite the muscle tightness may present (plagiocephaly)
Physical therapy interventions for torticollis
- Stretching of the contracted sternocleidomastoid muscle
- Stretching involves lateral flexion away from the contracted side and opposite head rotations
- Positioning to allow for prolonged stretching
- Addressing any developmental delay issues